Related Experiment Video
Updated: Mar 5, 2026
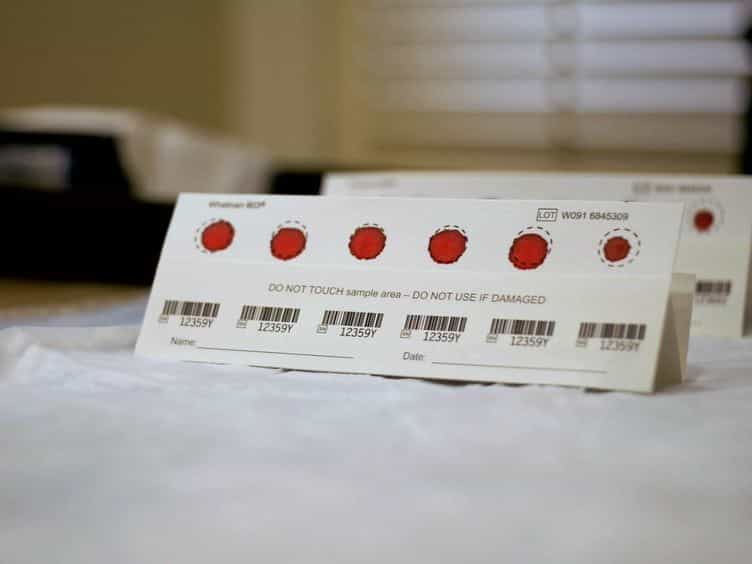

Dried Blood Spot Collection of Health Biomarkers to Maximize Participation in Population Studies
Published on: January 28, 2014
Deployed skills training for whole blood collection by a special operations expeditionary surgical team
Linda C Benavides1, Iain M Smith, Jerome M Benavides
1From the Martin Army Medical Center (L.C.B., J.M.B.), Fort Benning, Georgia; Academic Department of Military Surgery & Trauma (I.M.S.), Royal Centre for Defence Medicine, Birmingham, United Kingdom; 16 Medical Regiment, 16 Air Assault Brigade (D.M.B.), Colchester, United Kingdom; Academic Department of Military Anaesthesia and Critical Care (H.A.D.), Royal Center for Defence Medicine, United Kingdom; Carl R. Darnall Army Medical Center, Department of General Surgery (J. B. L.), Fort Hood, Texas.

Background:
Noncompressible hemorrhage is the leading cause of potentially preventable battlefield death. Combining casualty retrieval from the battlefield and damage control resuscitation (DCR) within the "golden hour" increases survival. However, transfusion requirements may exceed the current blood component stocks held by forward surgical teams. Warm fresh whole blood (WFWB) is an alternative. We report WFWB transfusion training developed by and delivered to a US Golden Hour Offset Surgical Treatment Team and the resulting improvement in confidence with WFWB transfusion.
Methods:
A bespoke instructional package was derived from existing operational clinical guidelines. All Golden Hour Offset Surgical Treatment Team personnel completed initial training, reinforced through ongoing casualty simulations. A record of blood types and donor eligibility was established to facilitate rapid identification of potential WFWB donors. Self-reported confidence in seven aspects of the WFWB transfusion process was assessed before and after training using a five-point Likert scale. Personnel were analyzed by groups consisting of those whose operational role includes WFWB transfusion ("transfusers"), clinical personnel without such responsibilities ("nontransfusers") and nonclinical personnel (other). Comparisons within and between groups were made using appropriate nonparametric tests.
Results:
Data were collected from 39 (89%) of 44 training participants: 24 (62%) transfusers, 12 (31%) nontransfusing clinicians, and 3 (8%) other personnel. Transfusers and nontransfusers reported increased comfort with all practical elements of WFWB transfusion. The confidence of other personnel also increased, but (likely due to small numbers) was not statistically significant.
Conclusion:
WFWB transfusion is an integral part of modern deployed military remote DCR. Our in-theater training program rapidly and reproducibly enhanced the comfort in WFWB transfusion in providers from a range of backgrounds and skill-mixes. This model has the potential to improve both safety and effectiveness of WFWB remote DCR in the far-forward deployed setting.
Level Of Evidence:
Therapeutic/care management study, level IV.

