Related Experiment Video
Updated: Mar 5, 2026
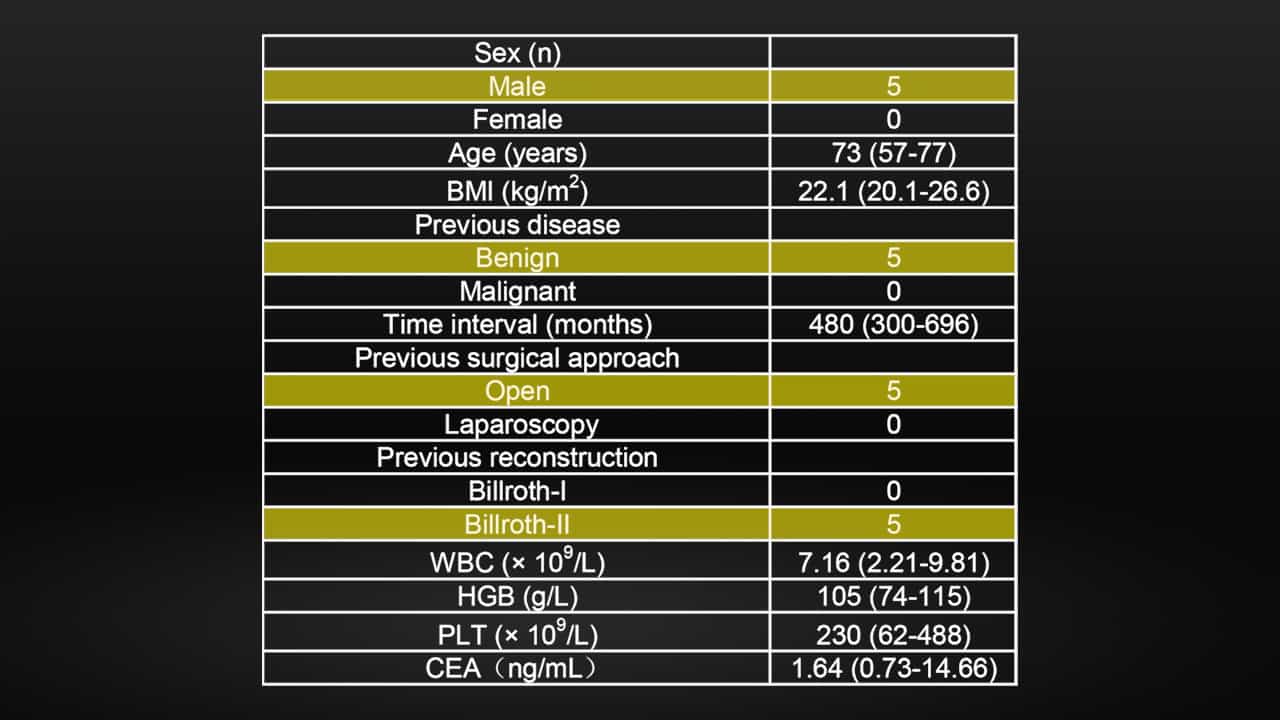

Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
[Application of multimodal analgesia in radical gastrectomy for gastric cancer patients: a prospective nonrandomized
Wei Zhang1, Ka Li1, Weihan Zhang1
1Department of Gastrointestinal Surgery, Institute of Gastric Cancer, West China Hospital, Sichuan University, Chengdu 610014, China.

Objective:
To compare the postoperative analgesia efficacy, rehabilitation parameters and complication between multimodal analgesia and traditional analgesia after radical gastrectomy for gastric cancer patients.
Methods:
Patients with gastric cancer who underwent surgery in our hospital from October 2016 to December 2016 were enrolled in this prospective study. According to the non-randomized method, patients were assigned to multimodal analgesia group(n=32) and traditional analgesia group(n=33) in gastric cancer treatment team A and B in Department of Gastrointestinal Surgery, West China Hospital, Sichuan University. The treatment measures of group A were as follows: (1) The ratio of 1/1 diluted ropivacaine (100 mg, 10 ml) was infiltrated around the incision before abdomen closure, with incision sutured layer by layer. (2) Parecoxib sodium (40 mg) was injected intravenously every 12 hours after operation for 5 days. (3) Oxycodone-acetaminophen tablet was given orally on the first day or the second day after operation, 50 mg twice a day. (4) Patient-controlled analgesia was not used after operation. Patients in group B received direct suture of incision and patient-controlled analgesia. The pain score, postoperative rehabilitation and 30-day postoperative complications were collected and analyzed.
Results:
Multimodal analgesia group had lower pain scores at 1 d (4.8±0.9), 2 d (4.3±1.0), 3 d (2.9±0.8), 4 d (2.4±0.7) and 5 d (1.7±0.7) after surgery, as compared to traditional analgesia group (5.9±0.9, P=0.000), (5.1±0.7, P=0.001), (3.9±0.8, P=0.000), (3.0±0.6, P=0.000), (2.6±0.7, P=0.000), with significant difference. Postoperative hospital stay [(8.2±1.6) days vs. (10.6±2.2) days, P=0.000], time to ambulation [(47.5±13.8) days vs. (66.2±16.8) days, P=0.000], time to first flatus [(76.4±25.2) days vs. (120.0±29.9) days, P=0.000], time to first defecate [(117.3±42.2) days vs. (159.7±30.7) days, P=0.000] and time to first fluid diet [(83.8±21.6) days vs. (141.9±33.9) days, P=0.000] in the multimodal analgesia group were significantly shorter than those in the traditional analgesia group. There was no significant difference between the two groups with respect to 30-day postoperative complication rate(9.4% vs. 9.1%, P=1.000).
Conclusions:
Multimodal analgesia can significantly reduce the postoperative pain and is beneficial to rehabilitation, meanwhile it does not increase the risk of postoperative complications. Multimodal analgesia is safe and effective for gastric cancer patients undergoing radical gastrectomy.
More Related Videos
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
 07:14
A Quantitative Sensory Testing Paradigm to Obtain Measures of Pain Processing in Patients Undergoing Breast Cancer Surgery
Published on: January 18, 2018
Related Concept Videos
 01:25
Analgesia and Pain Management
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease