Related Experiment Video
Updated: Mar 5, 2026
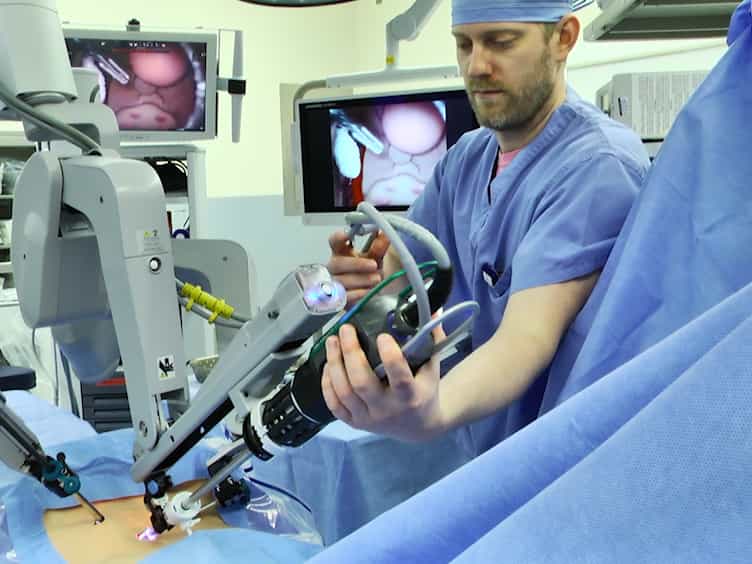

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
A before-after study of multidisciplinary Out-of-Hours handover: combining management and frontline efforts to create
Christopher Pennell1,2, Lorna Flynn3, Belinda Boulton4
1Nuffield Department of Surgical Sciences, Quality, Reliability, Safety and Teamwork Unit (QRSTU) and Patient Safety Academy (PSA), University of Oxford, John Radcliffe Hospital, Oxford OX3 9DU, UK.

Objective:
The importance of implementation strategy in systems improvement is increasingly recognized and both 'bottom-up' and 'top-down' approaches have significant barriers. A trial of a combined approach involving frontline and managerial staff therefore seems merited. We attempted to improve handover using a Human Factors-based approach integrated with a combined 'top and bottom' implementation strategy.
Design:
A before-after study was conducted across 9 months.
Setting:
The study was set in a 236 bed district general hospital.
Participants:
Participants included any member of staff involved in Out of Hours handover.
Intervention:
Existing processes were analysed using Human Factors methods. Changes made were based on this analysis and developed via facilitation between management and frontline staff. These included creating a single multidisciplinary handover, changing the venue, standardizing the meeting structure, developing an standard operating procedure for identifying unwell patients for handover and creating a clinical coordinator role.
Main Outcome Measures:
Meeting attendance, duration, start time efficiency, the type of patients handed over and the transfer of important information were measured pre- and post-intervention.
Results:
We found improvement in handover start time (P = 0.002, r = 0) and multidisciplinary participation (P = 0.002, r = -0.534). Handover of unwell patients improved, but not significantly. Communication of plan (P < 0.001, r = 0.14) and pending tasks (P < 0.001, r = 0.30) improved, but diagnosis (P = 0.233, r = -0.05), history (P = 0.482, r = -0.03) and comorbidities (P = 0.19, r = -0.05) did not.
Conclusions:
The changes produced greater multidisciplinary participation, a broader focus and improved communication of plans and tasks outstanding. The 'top and bottom' implementation approach appeared valuable. Management involvement was essential for significant changes, while frontline staff involvement facilitated the design of context-specific practical solutions with staff buy-in.

Related Concept Videos
 01:25
Types of Reports I: Hands-off Report
Following are the key components and categories of hand-off reports:
Purpose and Process:
 01:29
SBAR I: Understanding the Concept
Standardized methods of communication have been developed to ensure that information is...
 01:31
Discharge Summary Forms
Here's a detailed look at the key components and guidelines for preparing a discharge summary:
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:15
Methods of Documentation VI: Case Management Model
For example, a patient with a chronic...
 01:18
Interdisciplinary Care: The Health Care Team-II
Physical Therapist
A physical therapist (PT) aims to restore function or prevent additional impairment in a patient following an injury or disease. Massage, heat, cold, water, sonar waves, exercises, and electrical stimulation are some treatments used by PTs to treat...