Related Experiment Video
Updated: Mar 5, 2026


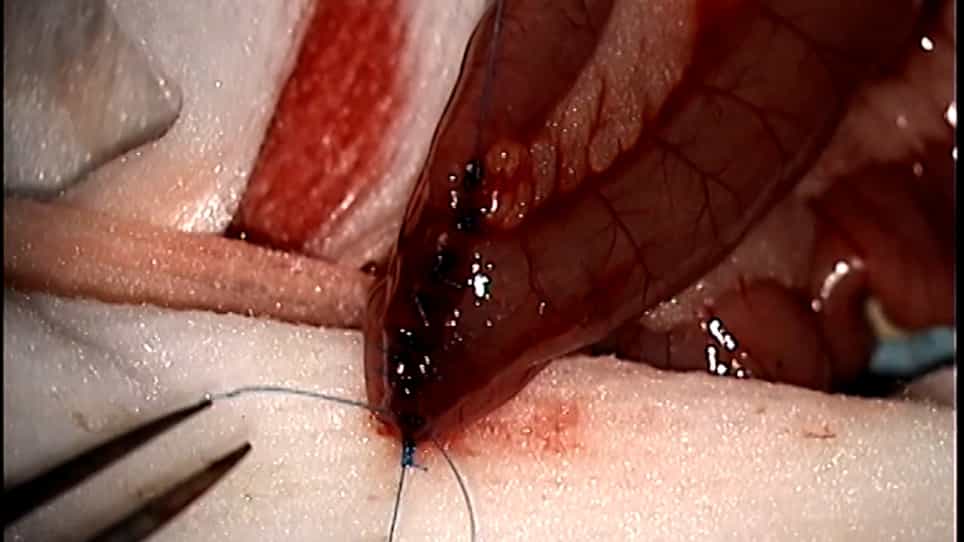
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Massive Biliary Dilation after Roux-en-Y Gastric Bypass: Is it Ampullary Achalasia?
Jeffrey L Ponsky1, Noble Jones2, John H Rodriguez3
1Department of General Surgery, Digestive Disease and Surgery Institute, Cleveland Clinic, Cleveland, OH; Lerner College of Medicine of Case Western Reserve University, Cleveland, OH.

Background:
This series of patients with a history of Roux-en-Y gastric bypass (RYGB) and cholecystectomy presented with symptoms consistent with obstructive biliary disease and massive biliary dilation of ≥15 mm, suggesting a structural cause. Findings from laparoscopic-assisted transgastric (TG) ERCP were a normal-appearing ampulla without structural lesions or stones, suggesting a functional cause instead.
Study Design:
Patients who underwent TGERCP from January 2008 to October 2016 and had a surgical history of RYGB and cholecystectomy were identified from an institutional database. Inclusion criteria was biliary dilation ≥15 mm, age 18 years or older, and no explanatory obstructive pathology.
Results:
Nine female patients met the inclusion criteria. At time of TGERCP, their mean age was 53.9 years, mean BMI was 32.5 kg/m2, mean bile duct diameter was 18.1 mm, and all patients experienced abdominal pain. Six patients (66.7%) presented with abnormal liver enzymes, 5 (55.6%) with nausea and/or vomiting, and 4 (44.4%) with earlier episode(s) of acute pancreatitis. Each patient had a normal-appearing papilla of Vater without stones or strictures at the time of TGERCP, with 8 (88.9%) patients experiencing cessation of abdominal pain after biliary sphincterotomy.
Conclusions:
This cohort of patients with a history of RYGB and cholecystectomy presented with massively dilated biliary trees lacking an obstructive disease process and experienced immediate symptom improvement after sphincterotomy. Their surgical history predisposed them to vagal nerve injury, leading to denervation of the sphincter of Oddi, and resulting in tonic contraction of the ampulla, that is, ampullary achalasia.