Related Experiment Video
Updated: Mar 5, 2026
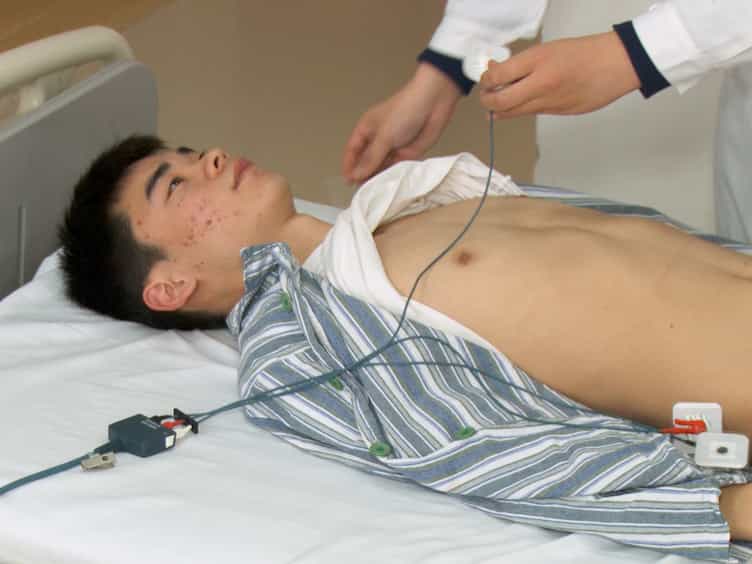

Measuring the Carotid to Femoral Pulse Wave Velocity Cf-PWV to Evaluate Arterial Stiffness
Published on: May 3, 2018
Influence of carotid atherosclerotic plaques on pulse wave assessment with arterial tonometry
Andrea Grillo1, Giulia Simon, Paolo Salvi
1aDepartment of Medicine and Surgery, University of Milano-Bicocca bDepartment of Cardiovascular, Neural and Metabolic Sciences, S. Luca Hospital, IRCCS Istituto Auxologico Italiano, Milan cDepartment of Medical, Surgical and Health Sciences, University of Trieste, Trieste, Italy *Andrea Grillo and Giulia Simon contributed equally to the article.

Insights
Carotid artery stenosis from atherosclerotic plaques does not bias measurements of pulse wave velocity (PWV) or central pulse waveform analysis using tonometry. These cardiovascular risk assessment tools remain reliable even with localized plaque presence.
Area of Science:
- Cardiovascular Medicine
- Vascular Biology
- Diagnostic Imaging
Background:
- Aortic stiffness and central pressure are crucial for cardiovascular risk assessment.
- Carotid artery stenosis is a common manifestation of atherosclerosis.
- Accurate measurement of pulse wave velocity (PWV) and central pulse waveform variables is essential for risk stratification.
Purpose of the Study:
- To determine if carotid artery stenosis due to atherosclerotic plaques introduces bias in PWV measurements.
- To assess the impact of carotid stenosis on central pulse waveform analysis via tonometry.
- To validate the reliability of carotid tonometry in patients with varying degrees of carotid atherosclerosis.
Main Methods:
- Eighty-four patients were categorized into three groups based on carotid ultrasound findings: no significant stenosis, bilateral plaques, or monolateral stenosis.
- Pulse wave velocity (PWV) and central pulse waveform variables (central blood pressure, augmentation index, forward/backward waves) were measured using carotid tonometry.
- A repeatability study was conducted on 28 young healthy individuals.
Main Results:
- High correlation was observed between bilateral measurements across all patient groups.
- No significant differences in measurements were attributable to the lateralization of carotid stenosis.
- Right-left differences for central blood pressure, augmentation index, PWV, and wave components showed high correlation coefficients, indicating measurement consistency.
Conclusions:
- Carotid tonometry measurements of PWV are not biased by the presence of local atherosclerotic plaques.
- Analysis of central pulse waveform variables using carotid tonometry is reliable in the presence of carotid stenosis.
- These findings support the continued use of carotid tonometry for cardiovascular risk assessment in patients with atherosclerosis.
Objective:
Aortic stiffness and central pressure measurements have become increasingly important for the overall estimation of cardiovascular risk. The aim of this study is to verify whether the presence of stenosis in the carotid arteries due to atherosclerotic plaques may induce a bias in the measurement of carotid-femoral pulse wave velocity (PWV) and in the analysis of central pulse waveform variables assessed by carotid tonometry.
Methods:
Eighty-four patients (age: 67.1 ± 12.4 years) undergoing screening for carotid atherosclerosis were enrolled, divided into three groups according to carotid ultrasound findings (NASCET criteria): 28 patients without significant stenosis, 30 patients with bilateral plaques, and 26 patients with right or left monolateral stenosis. PWV and other variables derived from the central pulse waveform analysis (central blood pressure, augmentation index and forward and backward waves) were measured at both right and left carotid arteries by a validated PulsePen tonometer. A repeatability study was performed in 28 young healthy patients (age: 25.4 ± 2.9 years).
Results:
A high degree of correlation was found between bilateral measurements in all groups, and particularly in groups with monolateral carotid stenosis, with no significant difference attributable to lateralized stenosis. Right-left differences in asymmetric groups were 0.35 ± 5.12 mmHg (R = 0.960) for central blood pressure, -2.12 ± 7.39% (R = 0.743) for augmentation index, 0.64 ± 1.56 m/s (R = 0.947) for PWV, 0.08 ± 8.48 mmHg for forward wave (R = 0.742) and 0.35 ± 2.35 mmHg for backward wave (R = 0.907).
Conclusion:
Measurement of PWV and of variables derived from the central pulse waveform analysis by carotid tonometry is not biased by the presence of local atherosclerotic plaques.

Related Concept Videos
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:16
Pulse
The pulse serves as a clinical...
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:19
Assessing Blood pressure using a doppler ultrasound
Pre-Procedural Guidelines for Doppler Ultrasound Blood Pressure Assessment:
Preparation of Equipment:
 01:17
Pulse amplitude and quality
A weak or absent pulse may indicate reduced cardiac output or poor left ventricular contraction, which can be signs of cardiovascular dysfunction or...