Related Experiment Video
Updated: Mar 5, 2026


Toxicity Study of Zinc Oxide Nanoparticles in Cell Culture and in Drosophila melanogaster
Published on: September 19, 2019
Clinical characteristics of zinc phosphide poisoning in Thailand
Satariya Trakulsrichai1, Natcha Kosanyawat2, Pongsakorn Atiksawedparit2
1Department of Emergency Medicine; Ramathibodi Poison Center.

Objective:
The objectives of this study were to describe the clinical characteristics and outcomes of poisoning by zinc phosphide, a common rodenticide in Thailand, and to evaluate whether these outcomes can be prognosticated by the clinical presentation.
Materials And Methods:
A 3-year retrospective cohort study was performed using data from the Ramathibodi Poison Center Toxic Exposure Surveillance System.
Results:
In total, 455 poisonings were identified. Most were males (60.5%) and from the central region of Thailand (71.0%). The mean age was 39.91±19.15 years. The most common route of exposure was oral (99.3%). Most patients showed normal vital signs, oxygen saturation, and consciousness at the first presentation. The three most common clinical presentations were gastrointestinal (GI; 68.8%), cardiovascular (22.0%), and respiratory (13.8%) signs and symptoms. Most patients had normal blood chemistry laboratory results and chest X-ray findings at presentation. The median hospital stay was 2 days, and the mortality rate was 7%. Approximately 70% of patients underwent GI decontamination, including gastric lavage and a single dose of activated charcoal. In all, 31 patients were intubated and required ventilator support. Inotropic drugs were given to 4.2% of patients. Four moribund patients also received hyperinsulinemia-euglycemia therapy and intravenous hydrocortisone; however, all died. Patients who survived and died showed significant differences in age, duration from taking zinc phosphide to hospital presentation, abnormal vital signs at presentation (tachycardia, low blood pressure, and tachypnea), acidosis, hypernatremia, hyperkalemia, in-hospital acute kidney injury, in-hospital hypoglycemia, endotracheal tube intubation, and inotropic requirement during hospitalization (P<0.05).
Conclusion:
Zinc phosphide poisoning causes fatalities. Most patients have mild symptoms, and GI symptoms are the most common. Patients who present with abnormal vital signs or electrolytes might have more severe poisoning and should be closely monitored and aggressively treated. All patients should be observed in the hospital for 2 days and followed up for cardiovascular and respiratory symptoms, electrolyte balances, kidney function, and blood glucose.


Related Concept Videos
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is...
 01:26
Pharmaceutical Poisoning: Treatment Strategies
 01:26
Pharmaceutical Poisoning: Potential Scenarios
 01:30
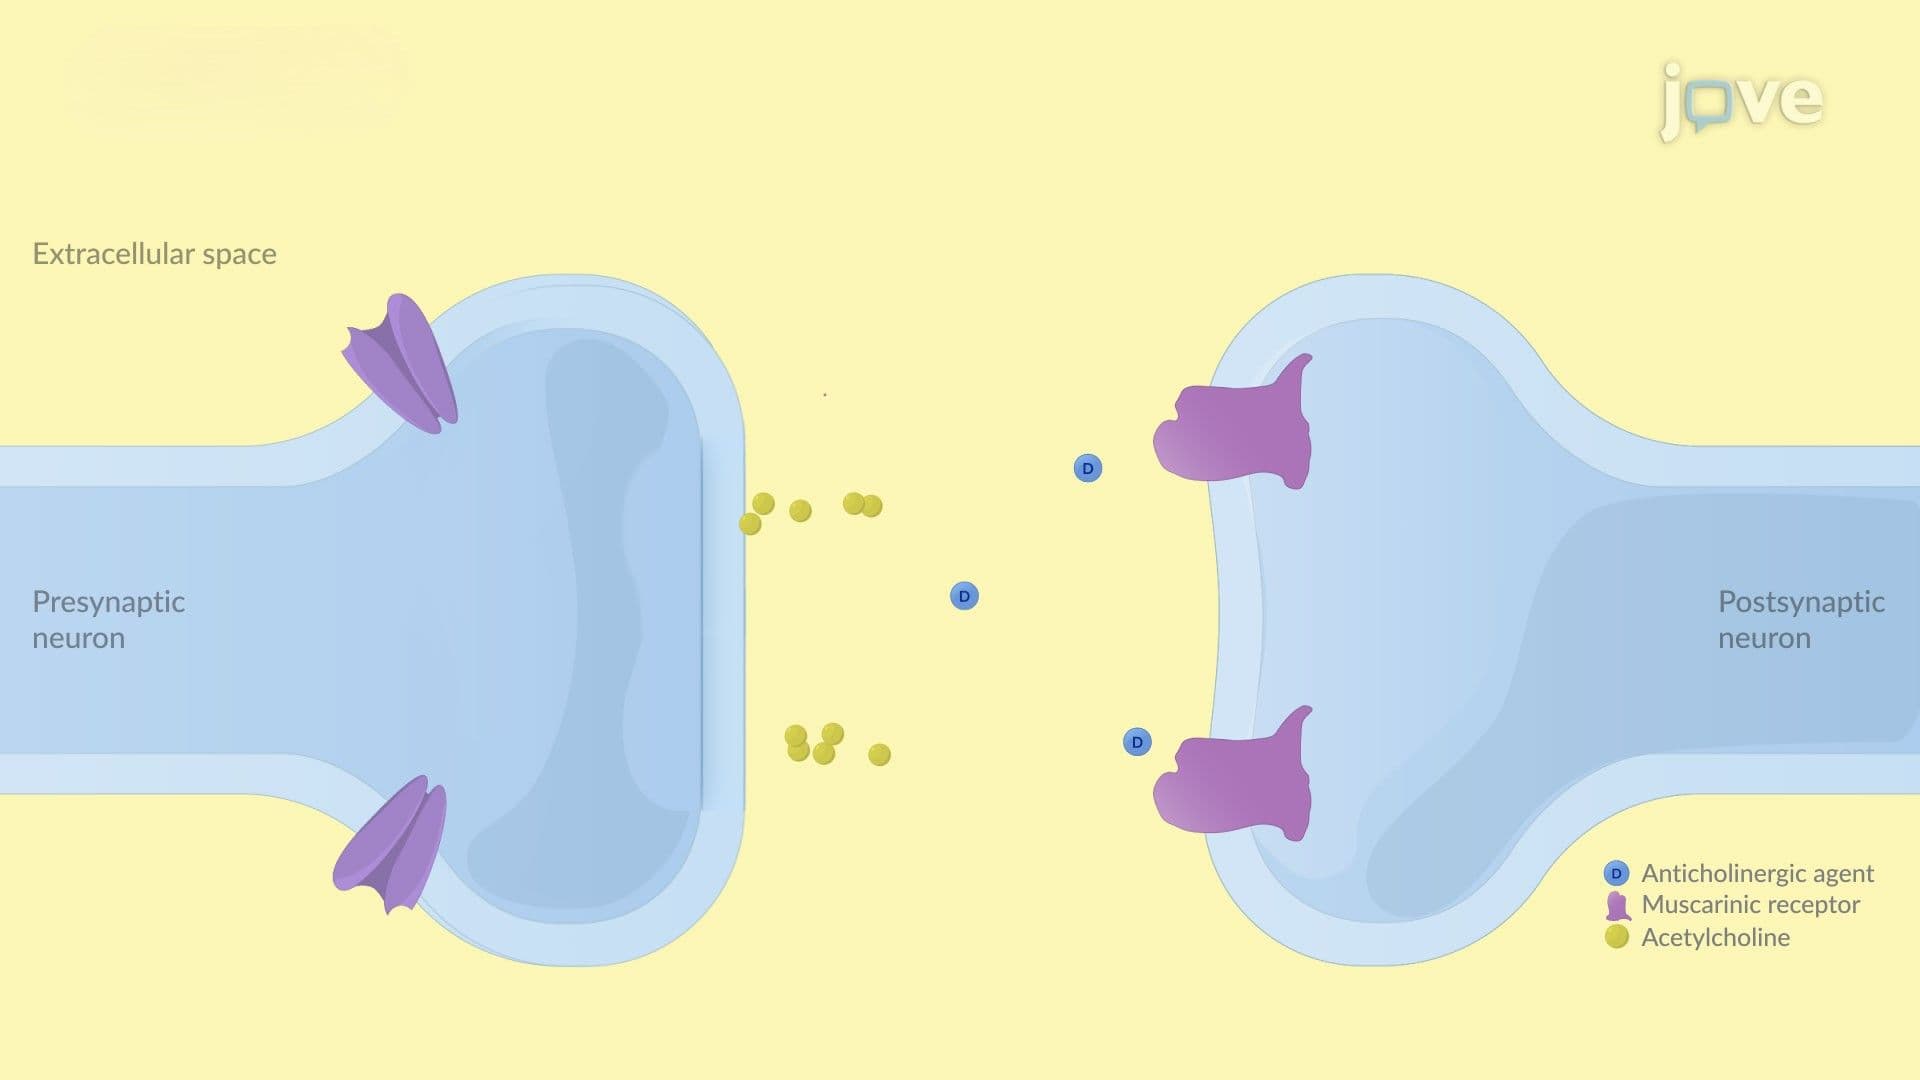
Toxidromes: Clinical Features
 01:14
Prevention of Further Absorption of Poison
 01:17
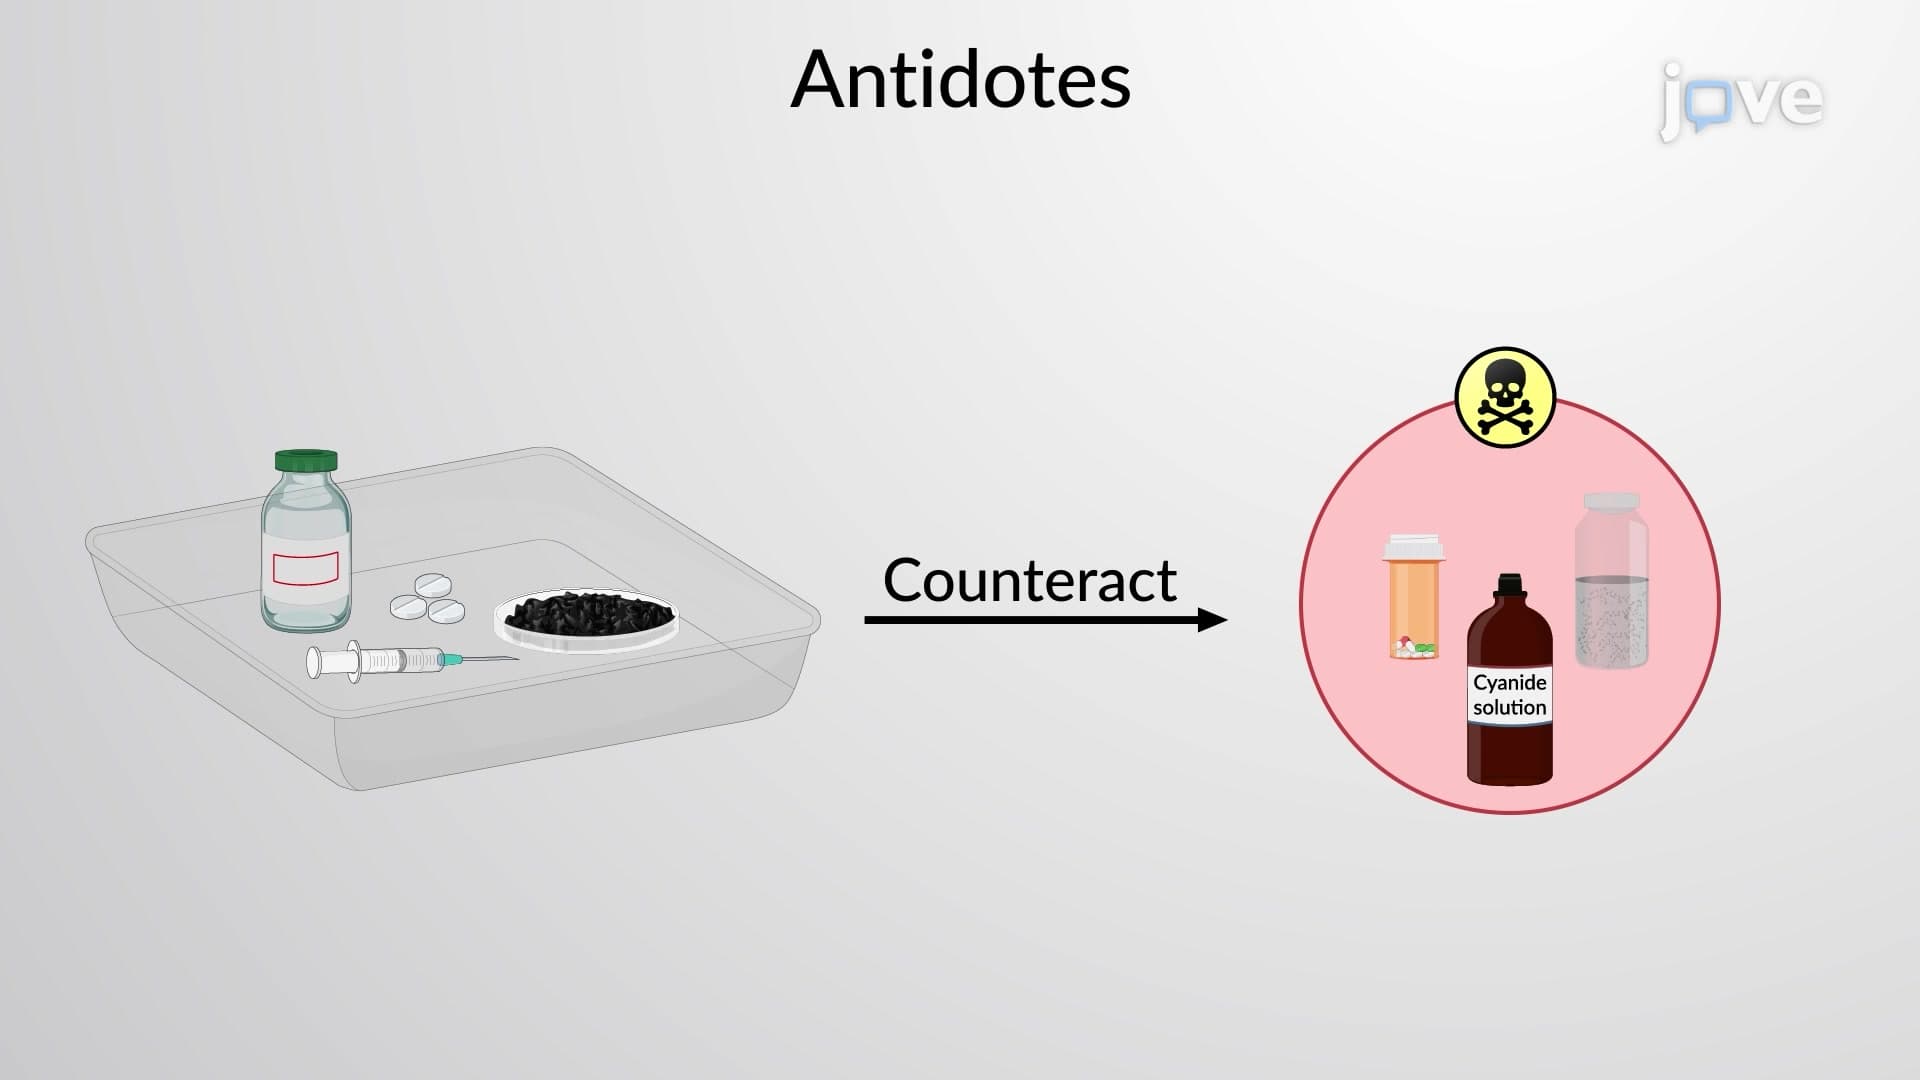
Antidotes
Specific antidotes operate by inhibiting the enzymes that control biochemical pathways, reducing the production of harmful metabolites.
An example of an antidote is atropine, which counteracts the detrimental effects of cholinesterase inhibitors. It achieves this by deactivating muscarinic receptors,...