Related Experiment Video
Updated: Jul 29, 2026

The WinCF Model - An Inexpensive and Tractable Microcosm of a Mucus Plugged Bronchiole to Study the Microbiology of Lung Infections
Published on: May 8, 2017
Concordance between upper and lower airway microbiota in infants with cystic fibrosis
Sabine M P J Prevaes1, Wouter A A de Steenhuijsen Piters1,2, Karin M de Winter-de Groot1,2
1Dept of Paediatrics, Wilhelmina Children's Hospital, University Medical Centre Utrecht, Utrecht, The Netherlands.

Insights
The lungs of infants with cystic fibrosis (CF) may have a unique microbiome, distinct from the upper respiratory tract. This finding impacts how we understand and treat lower respiratory tract infections in infants with CF.
Area of Science:
- Microbiology
- Pediatric Pulmonology
- Genomics
Background:
- Nasopharyngeal and oropharyngeal samples are standard for guiding lower respiratory tract infection therapy in non-expectorating infants with cystic fibrosis (CF).
- Understanding the lower airway microbiome is crucial for effective CF management.
Purpose of the Study:
- To investigate the concordance between bacterial communities in nasopharyngeal, oropharyngeal, and bronchoalveolar lavage (BAL) samples from infants with CF.
- To determine if upper airway microbiota accurately reflect the lower airway microbiome in infants with CF.
Main Methods:
- Analysis of 25 sample sets (nasopharyngeal, oropharyngeal, BAL) from 17 infants with CF (aged ~5 and ~12 months).
- Utilized conventional culturing and 16S-rRNA sequencing for bacterial community profiling.
- Employed clustering analyses to compare microbial profiles across different sample types.
Main Results:
- Bronchoalveolar lavage (BAL) microbiota generally comprised a mix of oral and nasopharyngeal bacteria, including commensals (e.g., Streptococcus, Neisseria) and potential pathogens (e.g., Staphylococcus aureus, Haemophilus influenzae).
- Significant variation in concordance was observed between upper respiratory tract niches and corresponding BAL microbiota within individuals.
- The degree of concordance between upper and lower respiratory tract microbiomes differed significantly among infants.
Conclusions:
- The lower respiratory tract microbiome in infants with CF appears distinct from, though seeded by, the upper respiratory tract microbiome.
- Inconsistent concordance suggests that upper airway sampling may not fully represent the lung's microbial environment in infants with CF.
- This highlights the potential for a unique lung microbiome in CF infants, influencing therapeutic strategies.
Abstract:
Nasopharyngeal and oropharyngeal samples are commonly used to direct therapy for lower respiratory tract infections in non-expectorating infants with cystic fibrosis (CF).We aimed to investigate the concordance between the bacterial community compositions of 25 sets of nasopharyngeal, oropharyngeal and bronchoalveolar lavage (BAL) samples from 17 infants with CF aged ∼5 months (n=13) and ∼12 months (n=12) using conventional culturing and 16S-rRNA sequencing.Clustering analyses demonstrated that BAL microbiota profiles were in general characterised by a mixture of oral and nasopharyngeal bacteria, including commensals like Streptococcus, Neisseria, Veillonella and Rothia spp. and potential pathogens like Staphylococcus aureus, Haemophilus influenzae and Moraxella spp. Within each individual, however, the degree of concordance differed between microbiota of both upper respiratory tract niches and the corresponding BAL.The inconsistent intra-individual concordance between microbiota of the upper and lower respiratory niches suggests that the lungs of infants with CF may have their own microbiome that seems seeded by, but is not identical to, the upper respiratory tract microbiome.


Related Concept Videos
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...
 01:22
Introduction to the Human Microbiota
 01:30
Development of Human Microbiota
 01:28
Development of the Oral Microbiota
 01:29
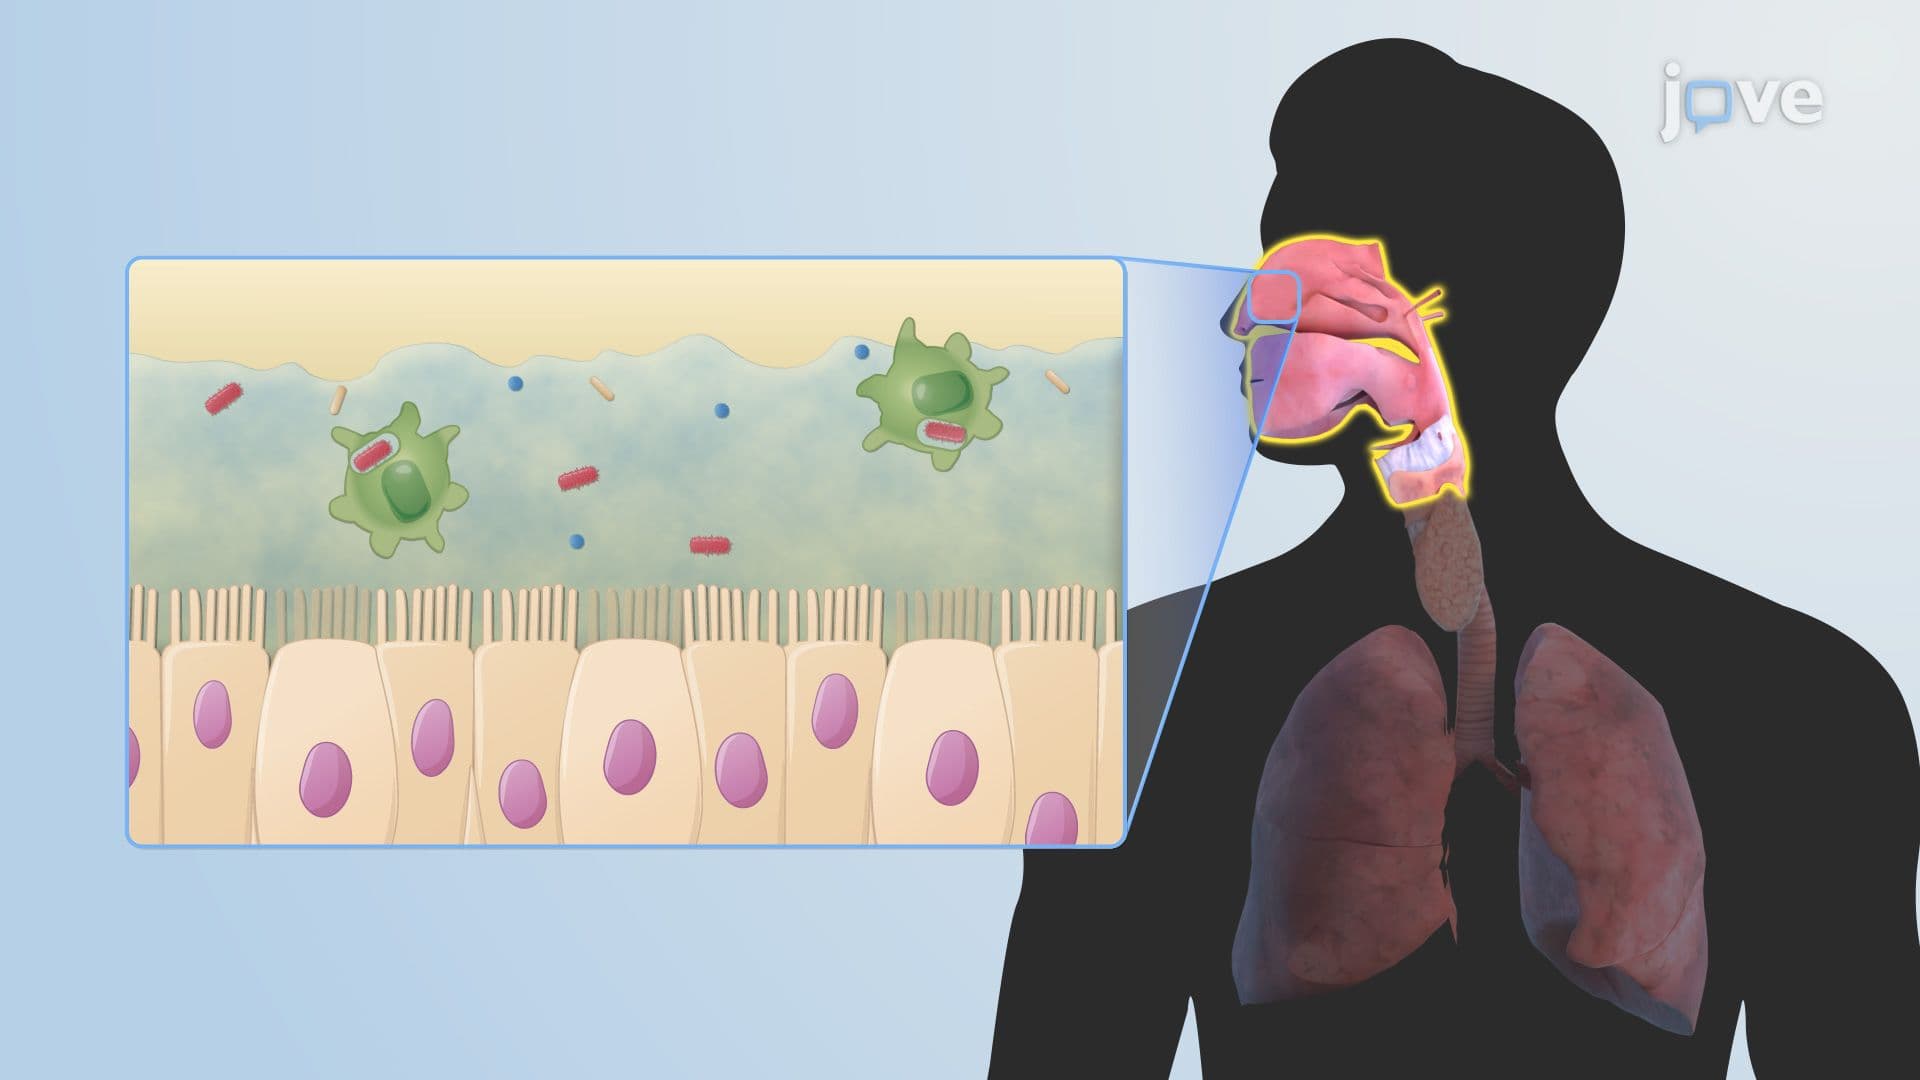
Microbiota of the Respiratory Tract
 01:21
Microbiota Modulation by Antibiotics