Related Experiment Video
Updated: Aug 11, 2026
Transcutaneous Assessment of Renal Function in Conscious Rodents
Published on: March 26, 2016
Sodium glucose transporter-2 inhibition has no renoprotective effects on non-diabetic chronic kidney disease
Qiuyue Ma1, Stefanie Steiger1, Hans-Joachim Anders2
1Medizinische Klinik und Poliklinik IV, Klinikum der Universität München, Munich, Germany.

Abstract:
Sodium glucose transporter (SGLT)-2 inhibition has renoprotective effects in diabetic kidney disease. Whether similar effects can be achieved also in non-diabetic kidney disease is speculative. Chronic kidney disease was induced in C57BL/6N mice by feeding an oxalate-rich diet for 14 days, known to induce nephrocalcinosis-related tubular atrophy and interstitial fibrosis without directly affecting the glomerular compartment. Empagliflozin treatment started from day 0 of oxalate feeding had no effect on the decline of glomerular filtration rate, crystal deposition, blood urea nitrogen or serum creatinine levels on day 7 and 14. Tissue morphometry of tubular injury and kidney mRNA levels of kidney injury molecule-1 or tissue inhibitor of metalloproteinase-2 were comparable between empagliflozin- and vehicle-treated mice with oxalate nephropathy on day 7 and 14. Similarly, empagliflozin did not affect markers of interstitial fibrosis, including silver, alpha smooth muscle actin (αSMA) and collagen 1 staining, and mRNA levels of fibronectin-1, collagen 1α1, fibroblast-specific protein-1, and transforming growth factor (TGF)-β2 on day 7 and 14. Thus, the specific renoprotective mechanisms-of-action of SGLT2 inhibition in diabetic kidney disease do not apply to chronic oxalosis, a non-diabetic form of chronic kidney disease.
Insights
Sodium glucose transporter (SGLT)-2 inhibitors do not protect against non-diabetic kidney disease caused by oxalate nephropathy in mice. Their renoprotective effects seen in diabetic kidney disease do not translate to this condition.
Area of Science:
- Nephrology
- Pharmacology
- Toxicology
Background:
- Sodium glucose transporter (SGLT)-2 inhibition demonstrates renoprotective effects in diabetic kidney disease.
- The efficacy of SGLT2 inhibition in non-diabetic kidney diseases remains largely speculative.
- Oxalate nephropathy is a non-diabetic kidney disease model characterized by tubular injury and fibrosis.
Purpose of the Study:
- To investigate the renoprotective effects of SGLT2 inhibition in a non-diabetic kidney disease model.
- To determine if empagliflozin confers benefits in oxalate-induced nephropathy.
- To explore the applicability of SGLT2 inhibitor mechanisms beyond diabetic kidney disease.
Main Methods:
- Chronic kidney disease was induced in C57BL/6N mice using an oxalate-rich diet for 14 days.
- Empagliflozin treatment was administered from day 0 of oxalate feeding.
- Kidney function (GFR, BUN, creatinine), crystal deposition, tubular injury, and fibrosis markers were assessed on days 7 and 14.
Main Results:
- Empagliflozin did not improve glomerular filtration rate, reduce crystal deposition, or alter blood urea nitrogen and serum creatinine levels.
- Tissue analysis showed no significant differences in tubular injury markers (Kidney Injury Molecule-1, tissue inhibitor of metalloproteinase-2) between treated and control groups.
- Empagliflozin did not attenuate markers of interstitial fibrosis, including alpha-smooth muscle actin and collagen 1, nor related gene expression.
Conclusions:
- The renoprotective mechanisms of SGLT2 inhibition observed in diabetic kidney disease are not applicable to chronic oxalosis.
- Empagliflozin does not offer protection against oxalate-induced kidney injury and fibrosis in this non-diabetic model.
- Further research is needed to understand the specific pathways involved in SGLT2 inhibitor efficacy in different kidney disease contexts.

Related Concept Videos
 01:55
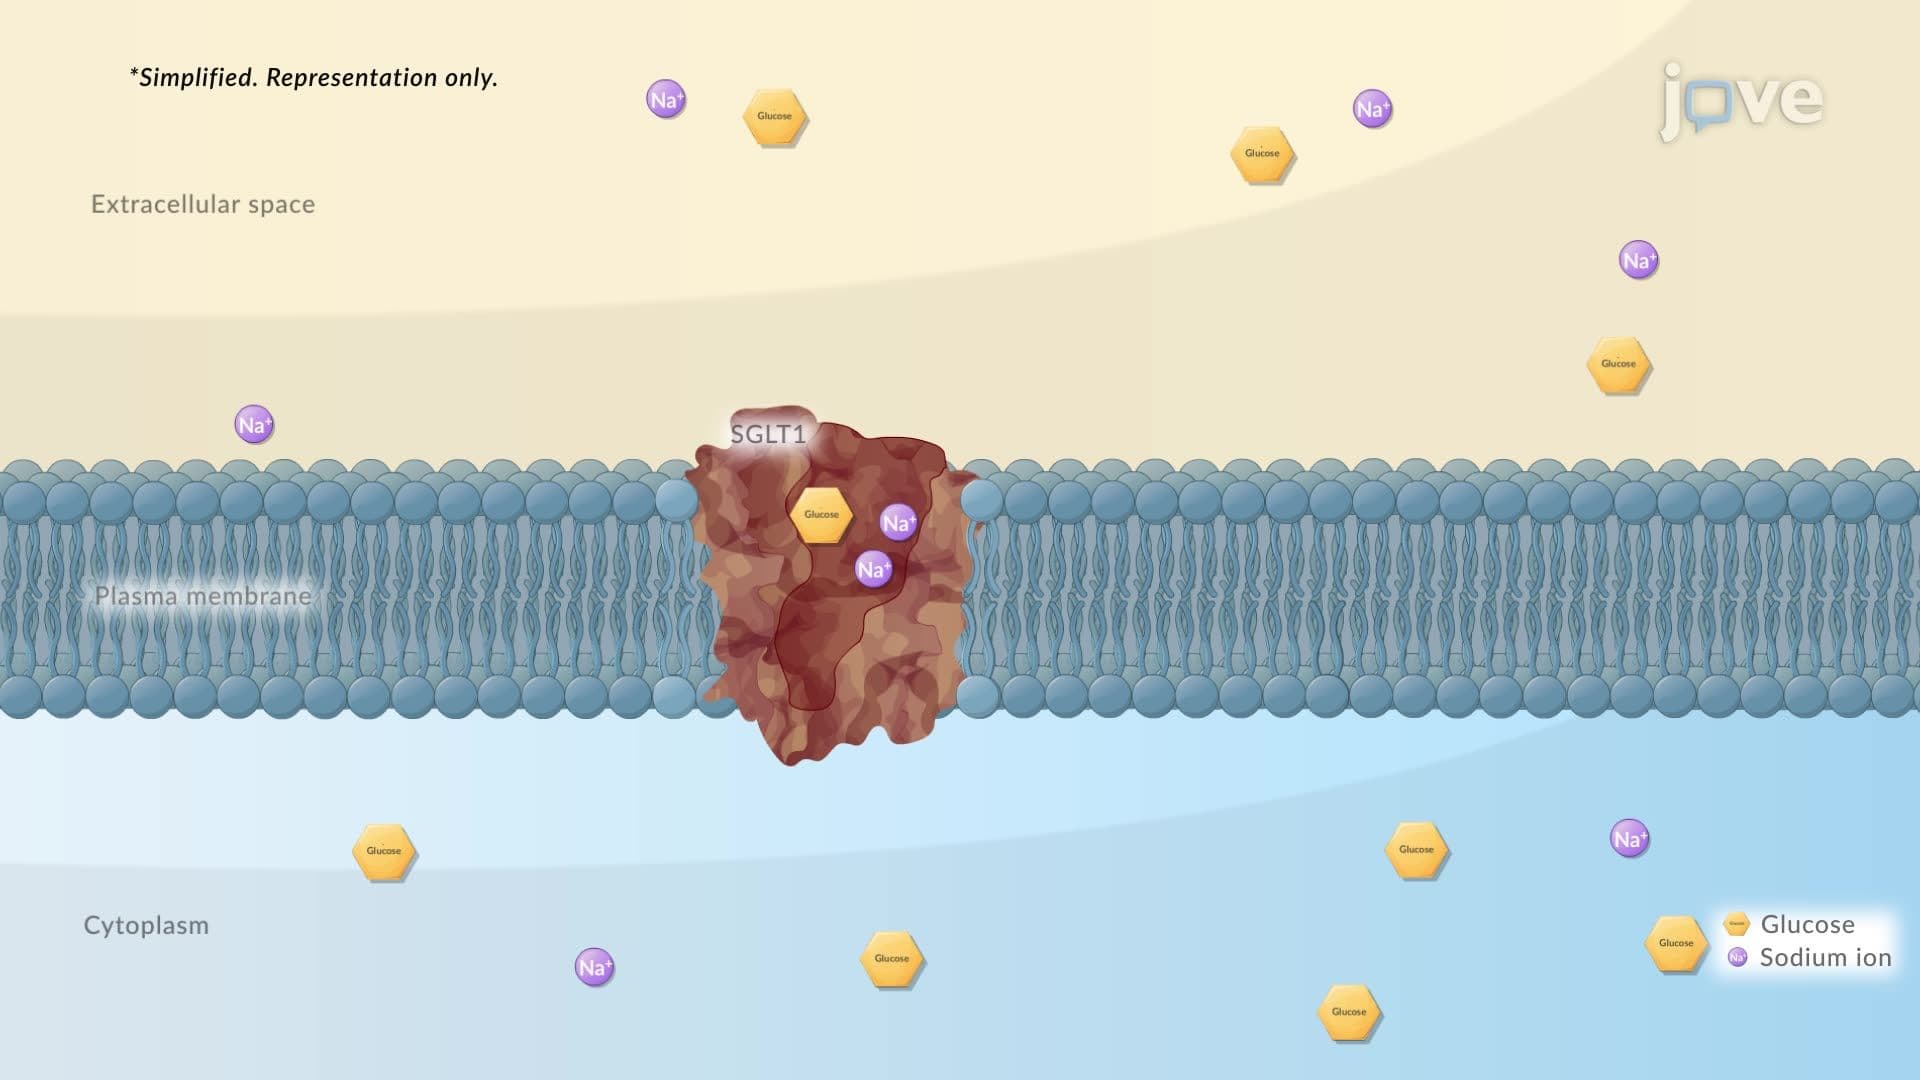
Secondary Active Transport
 01:32
Secondary Active Transport
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 01:16
Antihypertensive Drugs: Action of Diuretics
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:28
Diabetic Nephropathy