
The presence of diastolic and systolic dysfunction in patients with impaired relaxation filling pattern
Balaji Pratap1, Kamala Ramya Kallur1, Edgar Argulian1
1Mt Sinai St. Luke's Hospital, New York, NY, USA.

Insights
Patients with preserved ejection fraction but impaired relaxation show varied systolic and diastolic dysfunction. A comprehensive assessment beyond isolated diastolic dysfunction is crucial for characterizing these heart conditions.
Area of Science:
- Cardiology
- Echocardiography
- Heart Failure
Background:
- Impaired relaxation filling pattern with preserved ejection fraction is common.
- This pattern is often attributed to early diastolic dysfunction.
- The study aimed to identify systolic and diastolic dysfunction markers in these patients.
Purpose of the Study:
- To determine the distribution of systolic and diastolic dysfunction markers.
- To analyze echocardiographic parameters in patients with impaired relaxation and preserved ejection fraction.
- To investigate factors associated with reduced global longitudinal strain.
Main Methods:
- Retrospective observational study of 106 patients.
- Diastolic dysfunction assessed using the American Society of Echocardiography "50% rule".
- Systolic dysfunction evaluated by global longitudinal strain and circumferential strain, with patients grouped by longitudinal strain tertiles.
Main Results:
- Lower strain group showed higher rates of definite diastolic dysfunction (23% vs 7%) and lower rates of normal diastolic function (54% vs 80%).
- Patients with lower longitudinal strain also had lower circumferential strain (-21.2% vs -25.7%).
- Left atrial enlargement, increased left ventricular mass index, and altered E-wave deceleration time were independently associated with lower global longitudinal strain.
Conclusions:
- Patients with impaired relaxation and preserved ejection fraction exhibit diverse left ventricular systolic and diastolic abnormalities.
- Relying solely on diastolic dysfunction assessment may not fully capture the complexity of this patient group.
- Comprehensive evaluation of both systolic and diastolic function is necessary.
Background:
Impaired relaxation filling pattern in the presence of preserved left ventricular ejection fraction is a common finding which is ascribed to early diastolic dysfunction. We thought to determine the distribution of various markers of systolic and diastolic dysfunction in these patients.
Methods:
A total of 106 patients were included in this retrospective observational study. Diastolic dysfunction was defined using the American Society of Echocardiography recommendations ("50% rule"). The systolic dysfunction was evaluated by global longitudinal strain and circumferential strain. For further analysis, the patients were divided into the lower strain (lower tertile) and higher strain (upper tertiles) groups based on longitudinal strain.
Results:
There were marked differences between the groups in essential echocardiographic parameters. Patients in the lower strain group were more likely to have definite diastolic dysfunction (23% vs 7%, P<.01) and less likely to have normal diastolic function (54% vs 80%, P<.01). They also showed lower circumferential strain (-21.2% vs -25.7%, P<.01). In multivariate analysis, left atrial enlargement (odds ratio (OR) 4.6, 95% confidence interval (CI) 1.2-17.1), left ventricular mass index (OR 1.03, 95% CI 1.0-1.1), left ventricular end-diastolic volume (OR 1.1, 95% CI 1.0-1.1), and E-wave deceleration time (OR 0.99, 95% CI 0.98-1.0) were independently associated with lower global longitudinal strain.
Conclusions:
Patients with impaired relaxation filling pattern in the presence of preserved left ventricular ejection fraction have a wide spectrum of left ventricular systolic and diastolic performance abnormalities. Isolated assessment of diastolic dysfunction may not fully characterize this group of patients.


Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:25
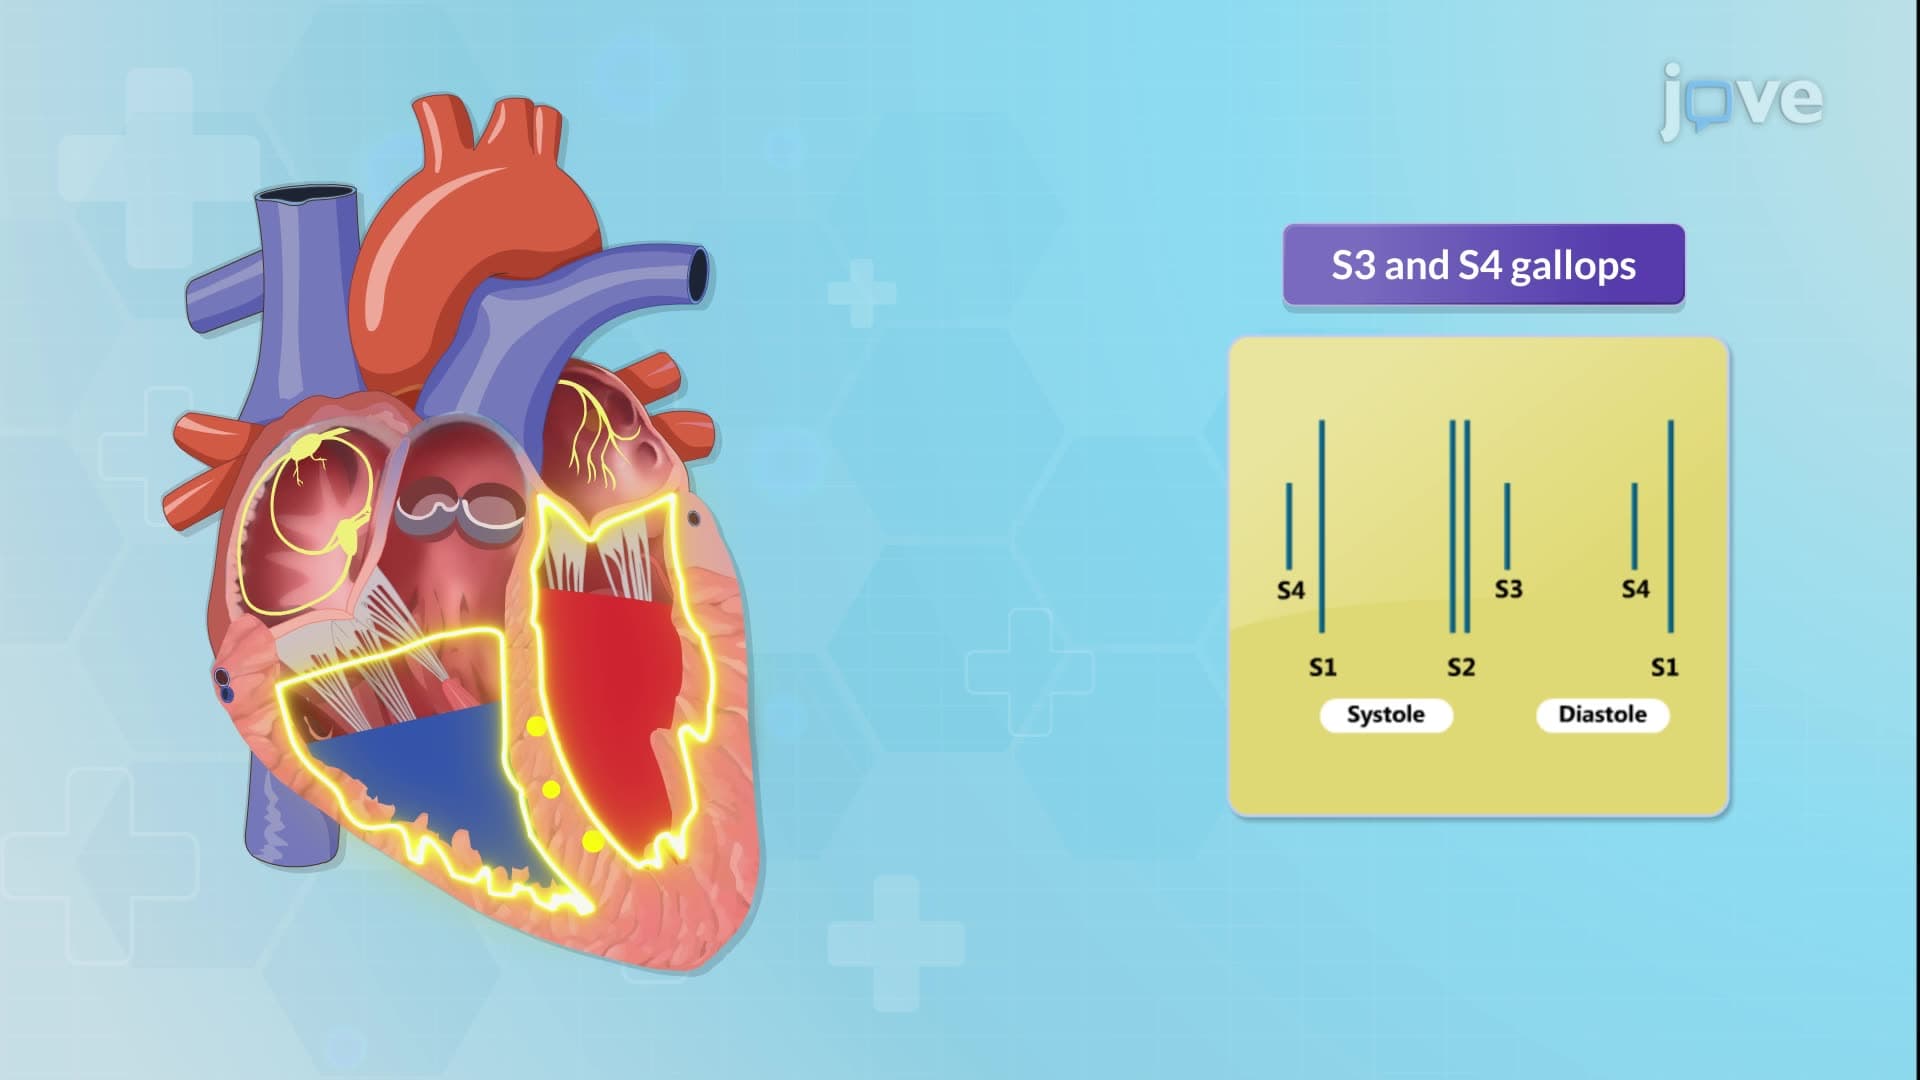
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:20
Mitral Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:29
Heart Failure II: Pathophysiology
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy