Related Experiment Video
Updated: Aug 10, 2026
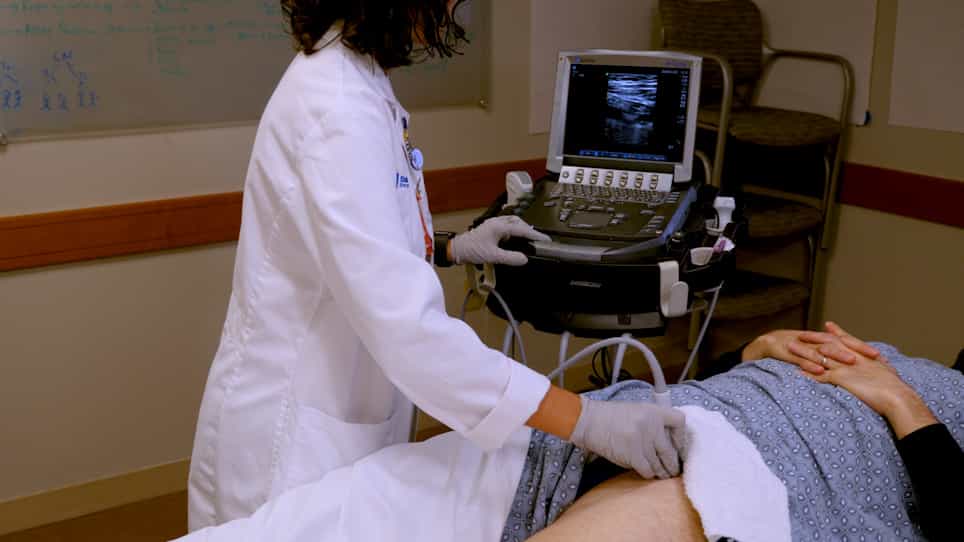
Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
A decision model to estimate a risk threshold for venous thromboembolism prophylaxis in hospitalized medical patients
P Le1, K A Martinez1, M A Pappas1
1Center for Value-based Care Research, Medicine Institute, Cleveland Clinic, Cleveland, OH, USA.

Abstract:
Essentials Low risk patients don't require venous thromboembolism (VTE) prophylaxis; low risk is unquantified. We used a Markov model to estimate the risk threshold for VTE prophylaxis in medical inpatients. Prophylaxis was cost-effective for an average medical patient with a VTE risk of ≥ 1.0%. VTE prophylaxis can be personalized based on patient risk and age/life expectancy.
Summary:
Background Venous thromboembolism (VTE) is a common preventable condition in medical inpatients. Thromboprophylaxis is recommended for inpatients who are not at low risk of VTE, but no specific risk threshold for prophylaxis has been defined. Objective To determine a threshold for prophylaxis based on risk of VTE. Patients/Methods We constructed a decision model with a decision-tree following patients for 3 months after hospitalization, and a lifetime Markov model with 3-month cycles. The model tracked symptomatic deep vein thromboses and pulmonary emboli, bleeding events and heparin-induced thrombocytopenia. Long-term complications included recurrent VTE, post-thrombotic syndrome and pulmonary hypertension. For the base case, we considered medical inpatients aged 66 years, having a life expectancy of 13.5 years, VTE risk of 1.4% and bleeding risk of 2.7%. Patients received enoxaparin 40 mg day-1 for prophylaxis. Results Assuming a willingness-to-pay (WTP) threshold of $100 000/ quality-adjusted life year (QALY), prophylaxis was indicated for an average medical inpatient with a VTE risk of ≥ 1.0% up to 3 months after hospitalization. For the average patient, prophylaxis was not indicated when the bleeding risk was > 8.1%, the patient's age was > 73.4 years or the cost of enoxaparin exceeded $60/dose. If VTE risk was < 0.26% or bleeding risk was > 19%, the risks of prophylaxis outweighed benefits. The prophylaxis threshold was relatively insensitive to low-molecular-weight heparin cost and bleeding risk, but very sensitive to patient age and life expectancy. Conclusions The decision to offer prophylaxis should be personalized based on patient VTE risk, age and life expectancy. At a WTP of $100 000/QALY, prophylaxis is not warranted for most patients with a 3-month VTE risk below 1.0%.
Related Concept Videos
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:30
Venous Thrombosis I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care