Related Experiment Video
Updated: Jul 27, 2026
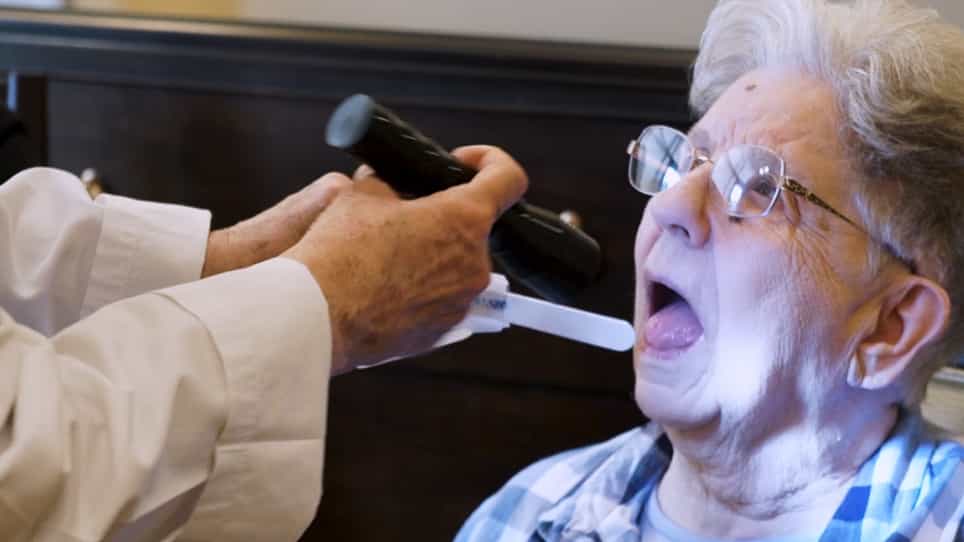
Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Congruence of Patient Self-Rating of Health with Family Physician Ratings
Nancy C Elder1, Ryan Imhoff2, Jennifer Chubinski2
1From the College of Medicine, University of Cincinnati, Cincinnati, OH (RI, PS, VR); the Department of Family and Community Medicine, University of Cincinnati, Cincinnati (NE, HP, MBVM, ACL, SR); Interact for Health, Cincinnati (JC); the Department of Anthropology, University of Cincinnati, Cincinnati, (CJJ); and the American Academy of Family Physicians, Leawood, KS (MC). Nancy.Elder@uc.edu.

Background:
A single self-rated health (SRH) question is associated with health outcomes, but agreement between SRH and physician-rated patient health (PRPH) has been poorly studied. We studied patient and physician reasoning for health ratings and the role played by patient lifestyle and objective health measures in the congruence between SRH and PRPH.
Methods:
Surveys of established family medicine patients and their physicians, and medical record review at 4 offices. Patients and physicians rated patient health on a 5-point scale and gave reasons for the rating and suggestions for improving health. Patients' and physicians' reasons for ratings and improvement suggestions were coded into taxonomies developed from the data. Bivariate relationships between the variables and the difference between SRH and PRPH were examined and all single predictors of the difference were entered into a multivariable regression model.
Results:
Surveys were completed by 506 patients and 33 physicians. SRH and PRPH ratings matched exactly for 38% of the patient-physician dyads. Variables associated with SRH being lower than PRPH were higher patient body mass index (P = .01), seeing the physician previously (P = .04), older age, (P < .001), and a higher comorbidity score (P = .001). Only 25.7% of the dyad reasons for health status rating and 24.1% of needed improvements matched, and these matches were unrelated to SRH/PRPH agreement. Physicians focused on disease in their reasoning for most patients, whereas patients with excellent or very good SRH focused on feeling well.
Conclusions:
Patients' and physicians' beliefs about patient health frequently lack agreement, confirming the need for shared decision making with patients.
More Related Videos

Related Concept Videos
 03:00
Self-Evaluation: Self-Enhancement and Self-Verification
 01:11
Purpose of Health Records I
Here's a breakdown of how health records serve these purposes:
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:17
Assessment of the Gastrointestinal System I: Subjective Data
Health History
The initial step in assessing the GI system is obtaining a comprehensive health history. This includes inquiring about the patient's history or presence of problems related to...
 01:29
Assessment of the Gastrointestinal System II: Health Perception Pattern
Health Perception Patterns
Health perception patterns offer valuable insights into a patient's lifestyle habits and how they may impact their GI health. These patterns include:
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...