Intermittent noninvasive ventilation after extubation in patients with chronic respiratory disorders: a multicenter randomized controlled trial (VHYPER)
Related Experiment Video
Updated: Oct 13, 2026
Non-Intubated Video-Assisted Thoracoscopic Surgery
Published on: May 26, 2023
Frédéric Vargas1,2, Marc Clavel3, Pascale Sanchez-Verlan4
1Service de Réanimation Médicale, Hôpital Pellegrin-Tripode, Centre Hospitalier Universitaire (CHU) de Bordeaux, 1 Place Amélie Raba-Léon, 33076, Bordeaux, France. frederic.vargas@chu-bordeaux.fr.

Purpose:
Early noninvasive ventilation (NIV) after extubation decreases the risk of respiratory failure and lowers 90-day mortality in patients with hypercapnia. Patients with chronic respiratory disease are at risk of extubation failure. Therefore, it could be useful to determine the role of NIV with a discontinuous approach, not limited to patients with hypercapnia. We assessed the efficacy of early NIV in decreasing respiratory failure after extubation in patients with chronic respiratory disorders.
Methods:
A prospective randomized controlled multicenter study was conducted. We enrolled 144 mechanically ventilated patients with chronic respiratory disorders who tolerated a spontaneous breathing trial. Patients were randomly allocated after extubation to receive either NIV (NIV group, n = 72), performed with a discontinuous approach, for the first 48 h, or conventional oxygen treatment (usual care group, n = 72). The primary endpoint was decreased respiratory failure within 48 h after extubation. Analysis was by intention to treat. This trial was registered with ClinicalTrials.gov (NCT01047852).
Results:
Respiratory failure after extubation was less frequent in the NIV group: 6 (8.5%) versus 20 (27.8%); p = 0.0016. Six patients (8.5%) in the NIV group versus 13 (18.1%) in the usual care group were reintubated; p = 0.09. Intensive care unit (ICU) mortality and 90-day mortality did not differ significantly between the two groups (p = 0.28 and p = 0.33, respectively). Median postrandomization ICU length of stay was lower in the usual care group: 3 days (IQR 2-6) versus 4 days (IQR 2-7; p = 0.008). Patients with hypercapnia during a spontaneous breathing trial were at risk of developing postextubation respiratory failure [adjusted odds ratio (95% CI) = 4.56 (1.59-14.00); p = 0.006] and being intubated [adjusted odds ratio (95% CI) = 3.60 (1.07-13.31); p = 0.04].
Conclusions:
Early NIV performed following a sequential protocol for the first 48 h after extubation decreased the risk of respiratory failure in patients with chronic respiratory disorders. Reintubation and mortality did not differ between NIV and conventional oxygen therapy.


Related Concept Videos
 01:15
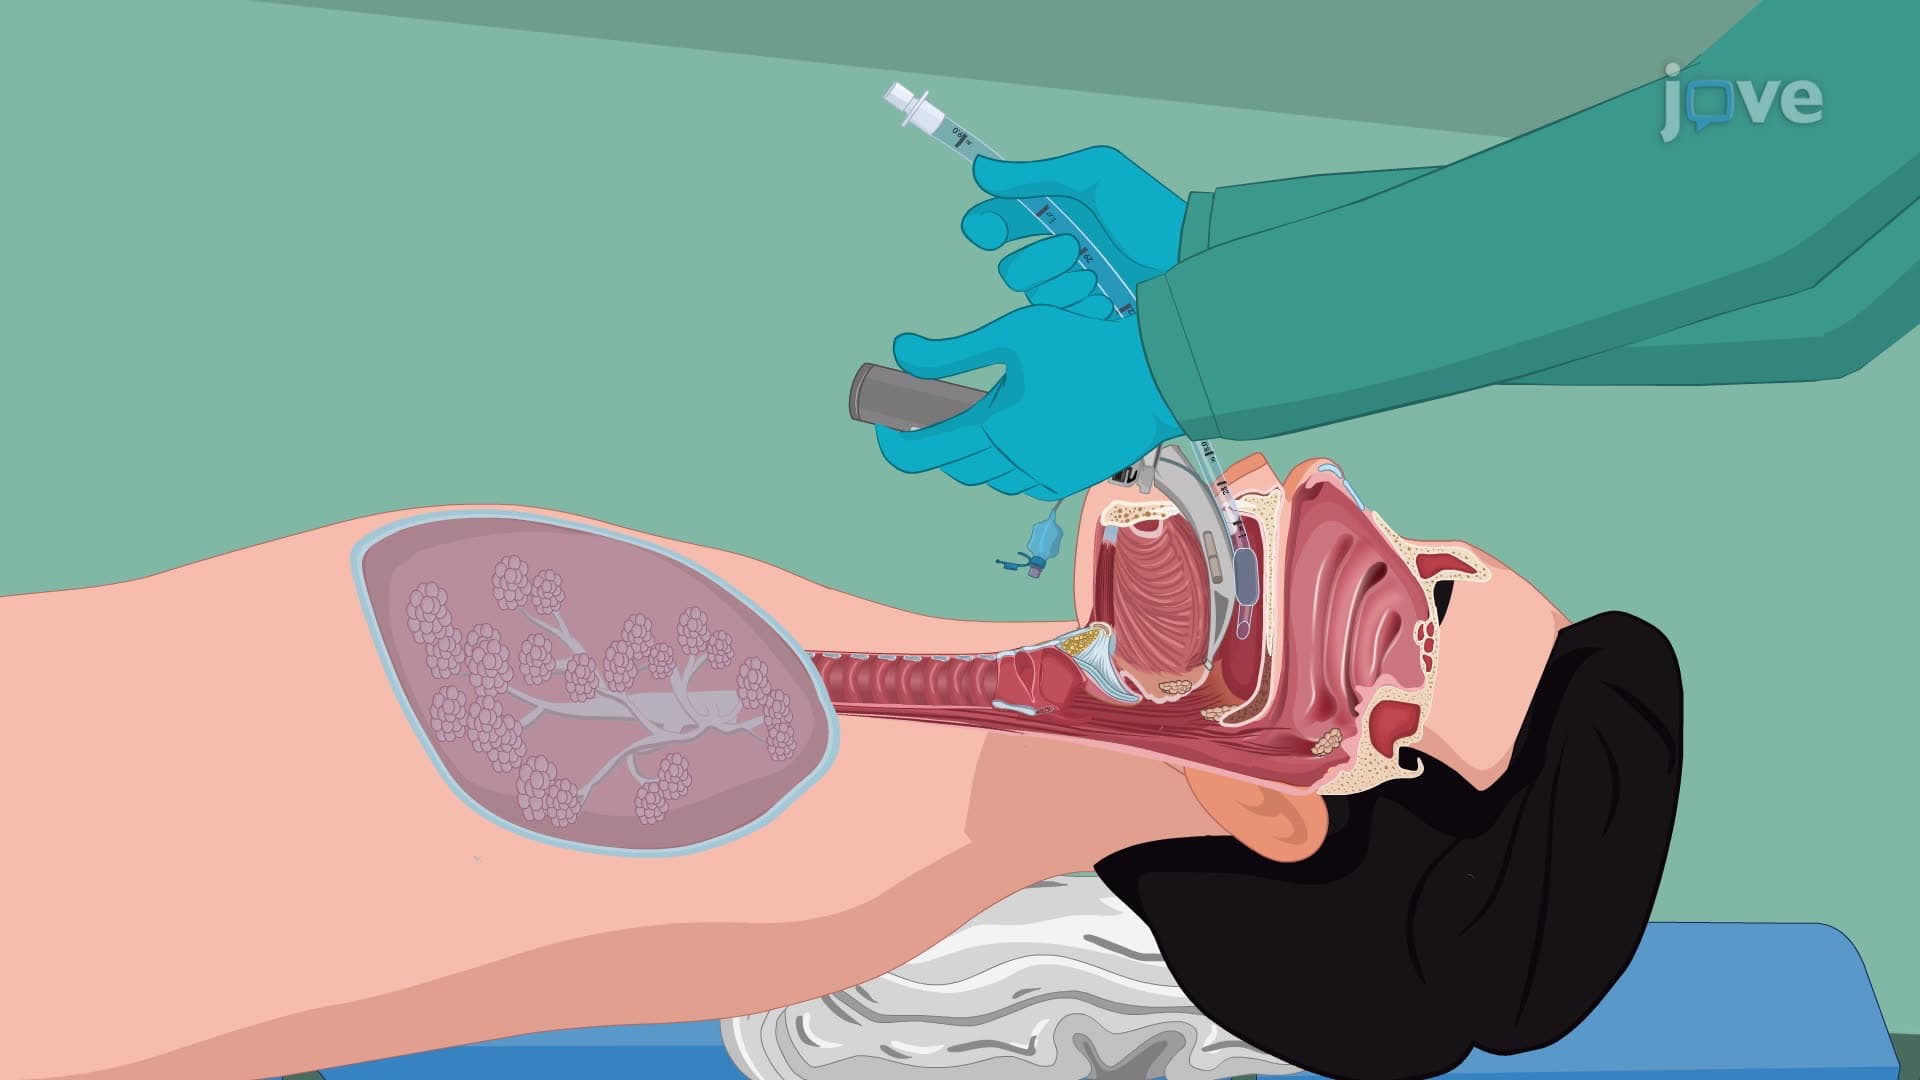
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:24
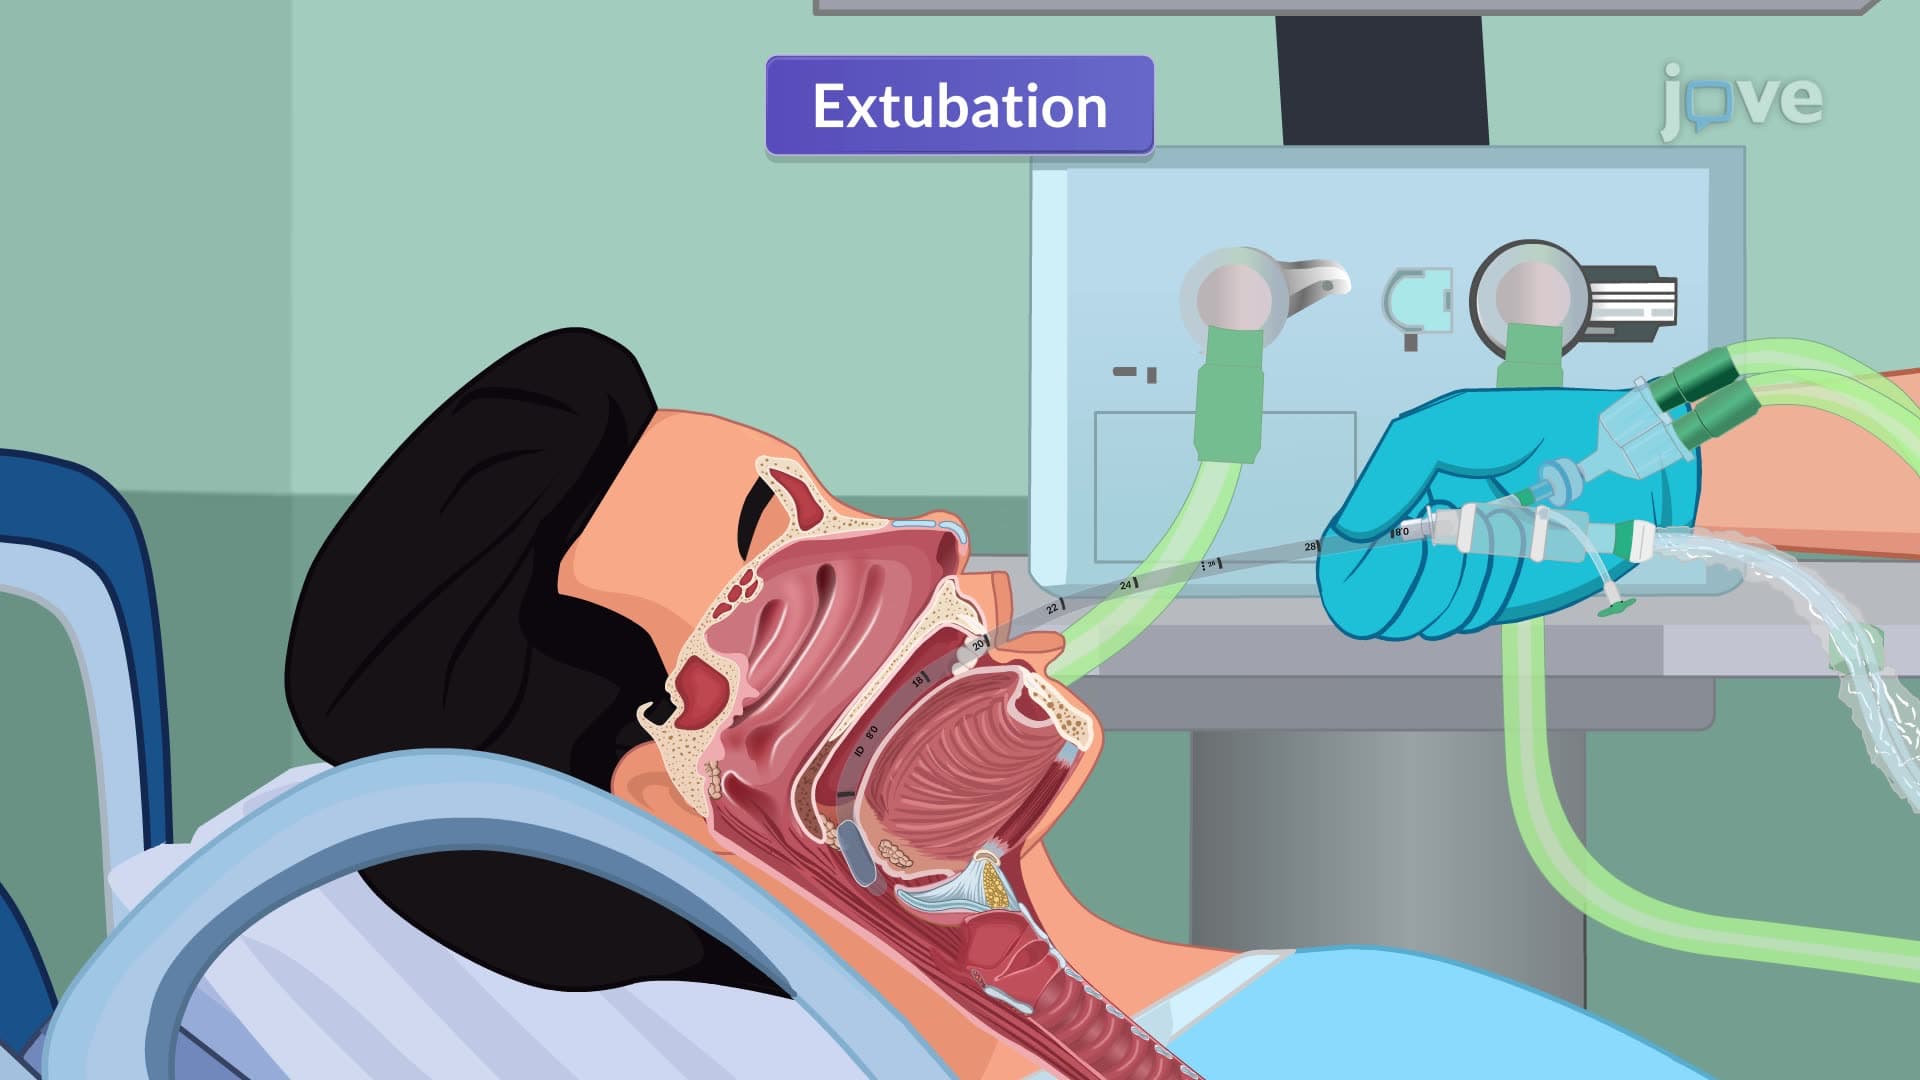
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:14
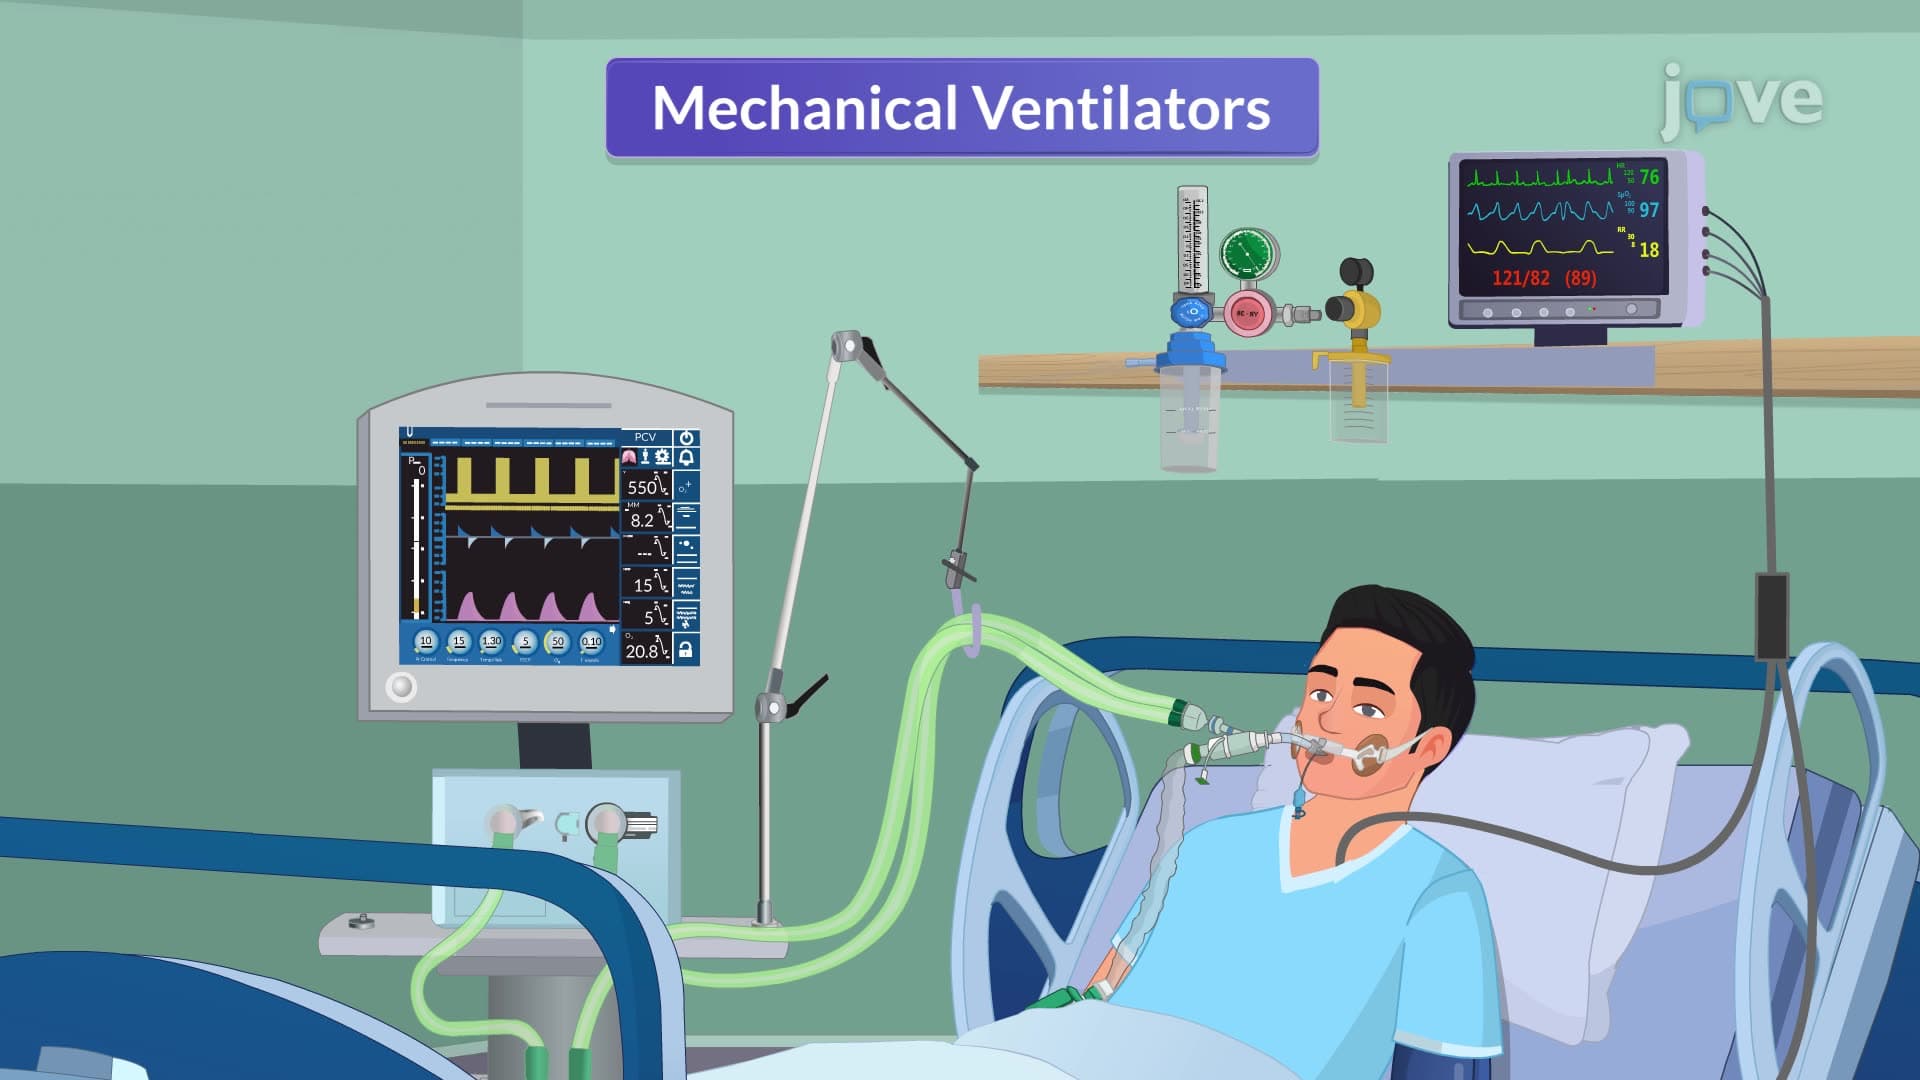
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...