Related Experiment Video
Updated: Jul 25, 2026

A Bedside, Single Burr Hole Approach to Multimodality Monitoring in Severe Brain Injury
Published on: March 26, 2019
Increased Intracranial Pressure during Hemodialysis in a Patient with Anoxic Brain Injury
Anton Lund1, Mette B Damholt2, Ditte G Strange1
1Department of Neuroanaesthesiology, Rigshospitalet, University of Copenhagen, Copenhagen, Denmark.

Abstract:
Dialysis disequilibrium syndrome (DDS) is a serious neurological complication of hemodialysis, and patients with acute brain injury are at increased risk. We report a case of DDS leading to intracranial hypertension in a patient with anoxic brain injury and discuss the subsequent dialysis strategy. A 13-year-old girl was admitted after prolonged resuscitation from cardiac arrest. Computed tomography (CT) revealed an inferior vena cava aneurysm and multiple pulmonary emboli as the likely cause. An intracranial pressure (ICP) monitor was inserted, and, on day 3, continuous renal replacement therapy (CRRT) was initiated due to acute kidney injury, during which the patient developed severe intracranial hypertension. CT of the brain showed diffuse cerebral edema. CRRT was discontinued, sedation was increased, and hypertonic saline was administered, upon which ICP normalized. Due to persistent hyperkalemia and overhydration, ultrafiltration and intermittent hemodialysis were performed separately on day 4 with a small dialyzer, low blood and dialysate flow, and high dialysate sodium content. During subsequent treatments, isolated ultrafiltration was well tolerated, whereas hemodialysis was associated with increased ICP necessitating frequent pauses or early cessation of dialysis. In patients at risk of DDS, hemodialysis should be performed with utmost care and continuous monitoring of ICP should be considered.
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:14
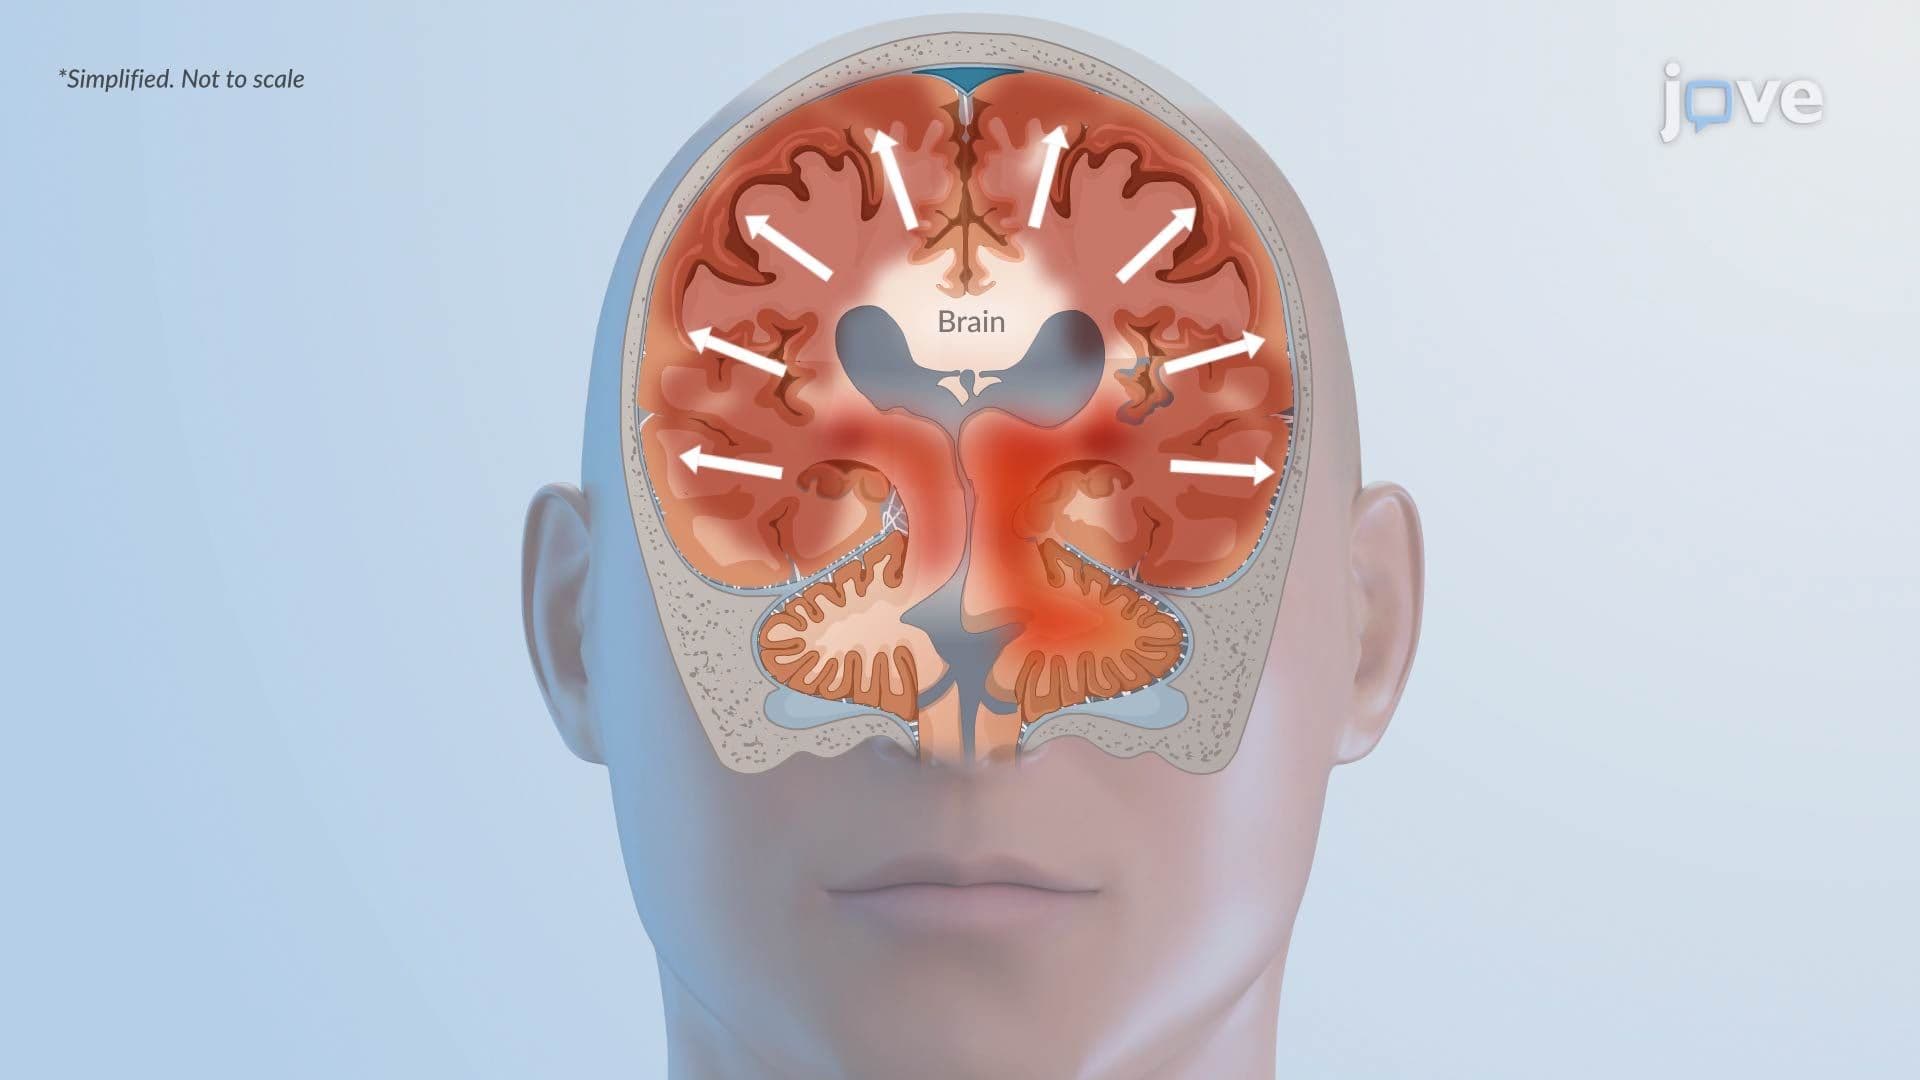
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:19
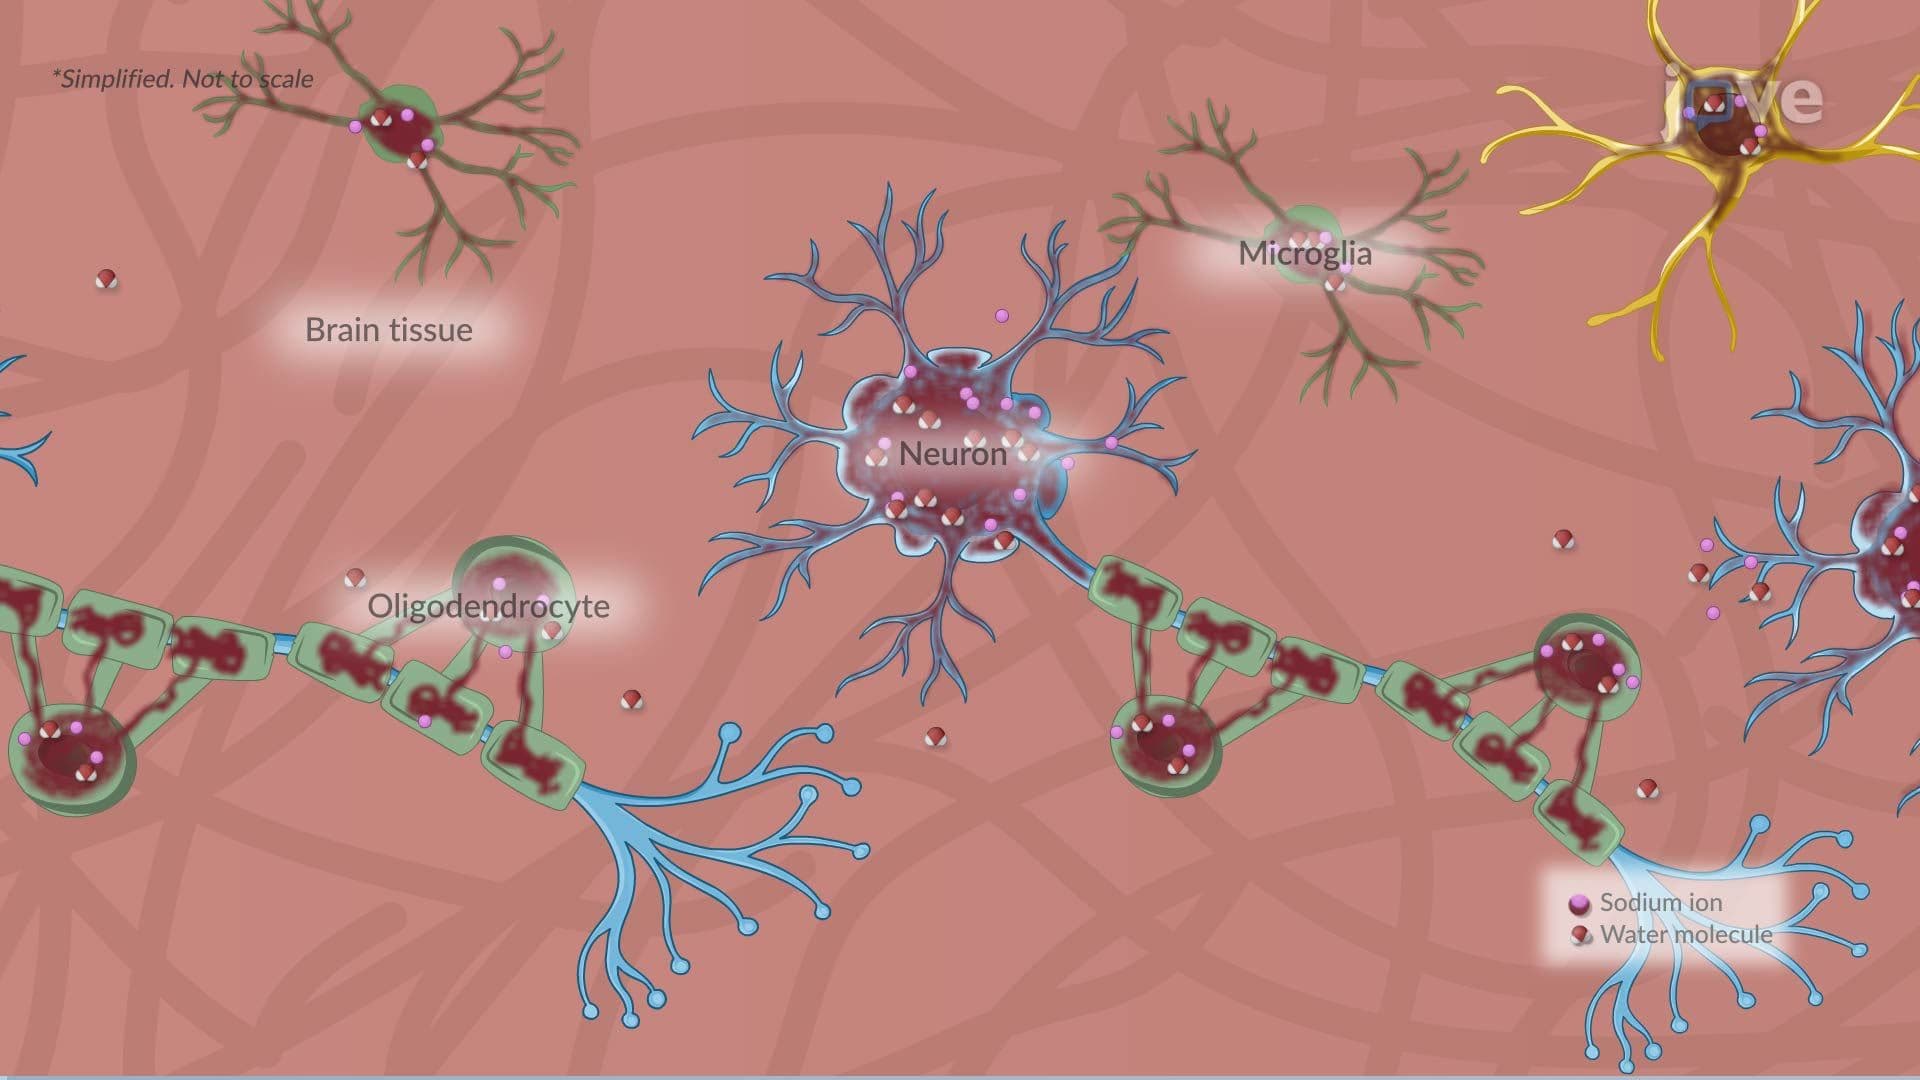
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:21
Cytotoxic Edema: Pathophysiology