Related Experiment Video
Updated: Mar 3, 2026
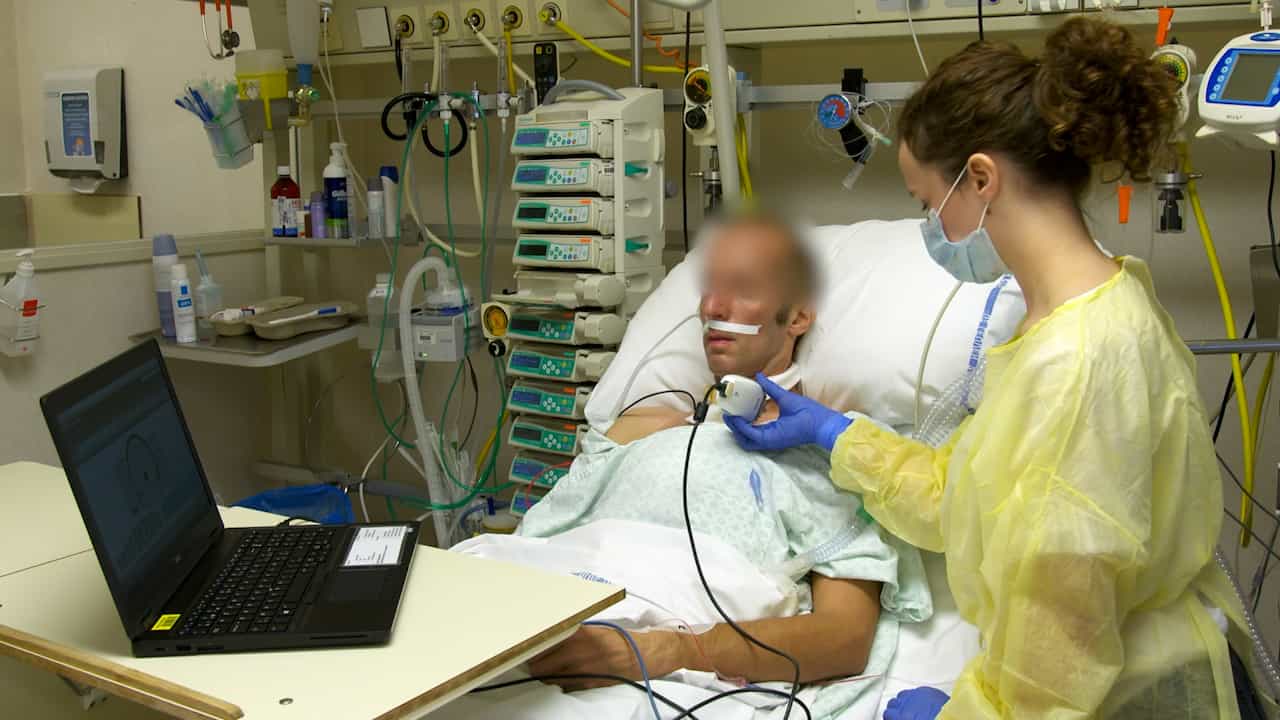

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Risk Factors for Pediatric Extubation Failure: The Importance of Respiratory Muscle Strength
Robinder G Khemani1, Tro Sekayan, Justin Hotz
11Department of Anesthesiology and Critical Care, Children's Hospital Los Angeles, Los Angeles, CA.2Department of Pediatrics, University of Southern California Keck School of Medicine, Los Angeles, CA.3Med-E Link, Amsterdam, The Netherlands.4Department of Respiratory Medicine, King's College London, London, United Kingdom.5Division of Neonatology, Department of Pediatrics, Children's Hospital Los Angeles, Los Angeles, CA.

Insights
Respiratory muscle weakness is common in children undergoing mechanical ventilation and significantly increases the risk of extubation failure. Assessing respiratory muscle strength pre-extubation is crucial for predicting outcomes in pediatric patients.
Area of Science:
- Pediatric Critical Care Medicine
- Respiratory Physiology
- Mechanical Ventilation
Background:
- Respiratory muscle weakness is a common complication of mechanical ventilation.
- Limited data exist on its prevalence and impact on extubation outcomes in children.
Purpose of the Study:
- To identify risk factors for pediatric extubation failure.
- To specifically investigate the association between respiratory muscle strength and extubation outcomes.
Main Methods:
- Secondary analysis of prospectively collected data from 409 mechanically ventilated children in a tertiary care PICU.
- Respiratory muscle strength (aPiMax) measured pre-extubation using esophageal manometry and respiratory inductance plethysmography.
- Evaluated postextubation respiratory effort and upper airway obstruction.
Main Results:
- 8.3% of patients required reintubation within 48 hours.
- Diminished respiratory muscle strength (aPiMax ≤ 30 cm H2O) was found in nearly 35% of children, tripling reintubation risk.
- Risk factors for reintubation included low aPiMax, prolonged ventilation, postextubation upper airway obstruction, and high respiratory effort.
Conclusions:
- Neuromuscular weakness at extubation is prevalent in children.
- This weakness is an independent predictor of reintubation, especially when combined with high postextubation respiratory effort.
Objective:
Respiratory muscle weakness frequently develops during mechanical ventilation, although in children there are limited data about its prevalence and whether it is associated with extubation outcomes. We sought to identify risk factors for pediatric extubation failure, with specific attention to respiratory muscle strength.
Design:
Secondary analysis of prospectively collected data.
Setting:
Tertiary care PICU.
Patients:
Four hundred nine mechanically ventilated children.
Interventions:
Respiratory measurements using esophageal manometry and respiratory inductance plethysmography were made preextubation during airway occlusion and on continuous positive airway pressure of 5 and pressure support of 10 above positive end-expiratory pressure 5 cm H2O, as well as 5 and 60 minutes postextubation.
Measurements And Main Results:
Thirty-four patients (8.3%) were reintubated within 48 hours of extubation. Reintubation risk factors included lower maximum airway pressure during airway occlusion (aPiMax) preextubation, longer length of ventilation, postextubation upper airway obstruction, high respiratory effort postextubation (pressure rate product, pressure time product, tension time index), and high postextubation phase angle. Nearly 35% of children had diminished respiratory muscle strength (aPiMax ≤ 30 cm H2O) at the time of extubation, and were nearly three times more likely to be reintubated than those with preserved strength (aPiMax > 30 cm H2O; 14% vs 5.5%; p = 0.006). Reintubation rates exceeded 20% when children with low aPiMax had moderately elevated effort after extubation (pressure rate product > 500), whereas children with preserved aPiMax had reintubation rates greater than 20% only when postextubation effort was very high (pressure rate product > 1,000). When children developed postextubation upper airway obstruction, reintubation rates were 47.4% for those with low aPiMax compared to 15.4% for those with preserved aPiMax (p = 0.02). Multivariable risk factors for reintubation included acute neurologic disease, lower aPiMax, postextubation upper airway obstruction, higher preextubation positive end-expiratory pressure, higher postextubation pressure rate product, and lower height.
Conclusions:
Neuromuscular weakness at the time of extubation was common in children and was independently associated with reintubation, particularly when postextubation effort was high.

Related Concept Videos
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:30
Acute Respiratory Failure-III
 01:17
Pulmonary Cycle: Exhalation
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...