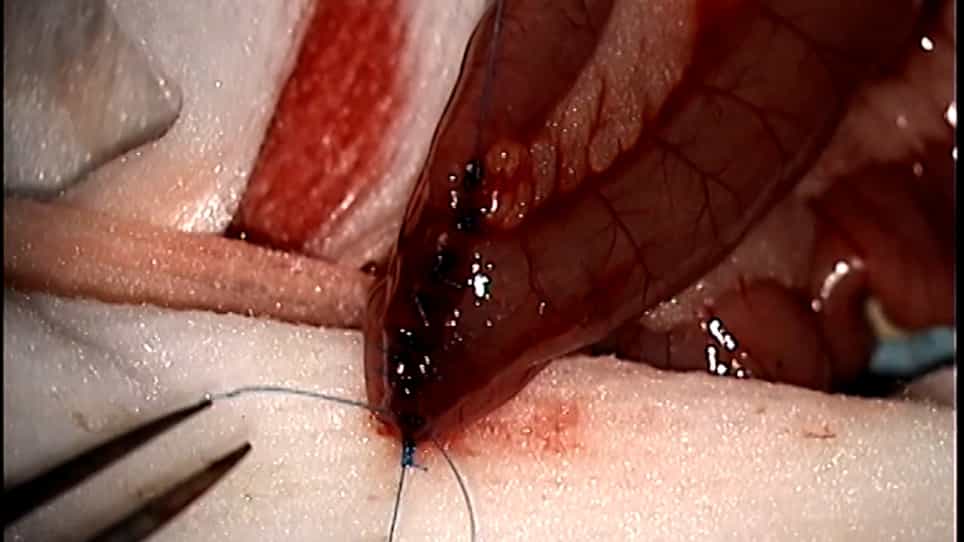
Related Experiment Video
Updated: Mar 3, 2026


One-anastomosis Gastric Bypass OAGB in Rats
Published on: November 10, 2018
Weight Loss Failure and Reoperation After Laparoscopic Adjustable Gastric Banding and Gastric Bypass: a Case-Matched
James G Bittner1, Natasha L Clingempeel2, Luke G Wolf2
1Department of Surgery, Virginia Commonwealth University School of Medicine, PO Box 980519, Richmond, VA, 23298, USA. jbittner4@gmail.com.

Introduction:
Not long ago, laparoscopic adjustable gastric banding (LAGB) was considered a safe and effective treatment of morbid obesity; however, long-term outcomes revealed significant complication and failure rates. We hypothesized that LAGB has higher rates of weight loss failure, reoperation, and overall failure compared to laparoscopic gastric bypass (LRYGB) at long-term follow-up.
Methods:
A matched case-control study was performed. Patients who underwent primary LAGB or LRYGB at a university hospital between 2004 and 2011 were propensity matched for age, gender, race, body mass index (BMI), and weight-related co-morbidities. Outcomes included demographics, percent excess weight loss (% EWL) and reoperation, weight loss failure (<50% EWL), and overall failure (procedure-related reoperation and/or <50% EWL) at 3- and 5-year follow-up.
Results:
In all, 228 LAGB and 228 LRYGB patients matched. LAGB patients had less mean EWL at 3 years (35 vs. 71%, P < 0.05) and 5 years (29.3 vs. 66.7%, P < 0.05). LAGB (11%) and LRYGB (11.5%) patients required procedure-related reoperation. More LAGB patients suffered weight loss failure at 3 years (75 vs. 10.5%, P < 0.05) and 5 years (81.5 vs. 15.4%, P < 0.05). Overall failure rates were higher after LAGB. The most common complication after LAGB was pouch/esophageal enlargement (9.7%) and after LRYGB was internal hernia (4.8%). LAGB patients had higher morbidity (19 vs. 12.7%, P = 0.04) but similar procedure-related mortality (0 vs. 0.4%).
Conclusions:
LAGB has significantly higher rates of weight loss failure compared to LRYGB with similar rates of procedure-related reoperation. Overall failure rates are higher after LAGB. These data suggest the long-term effectiveness of LAGB might be limited.