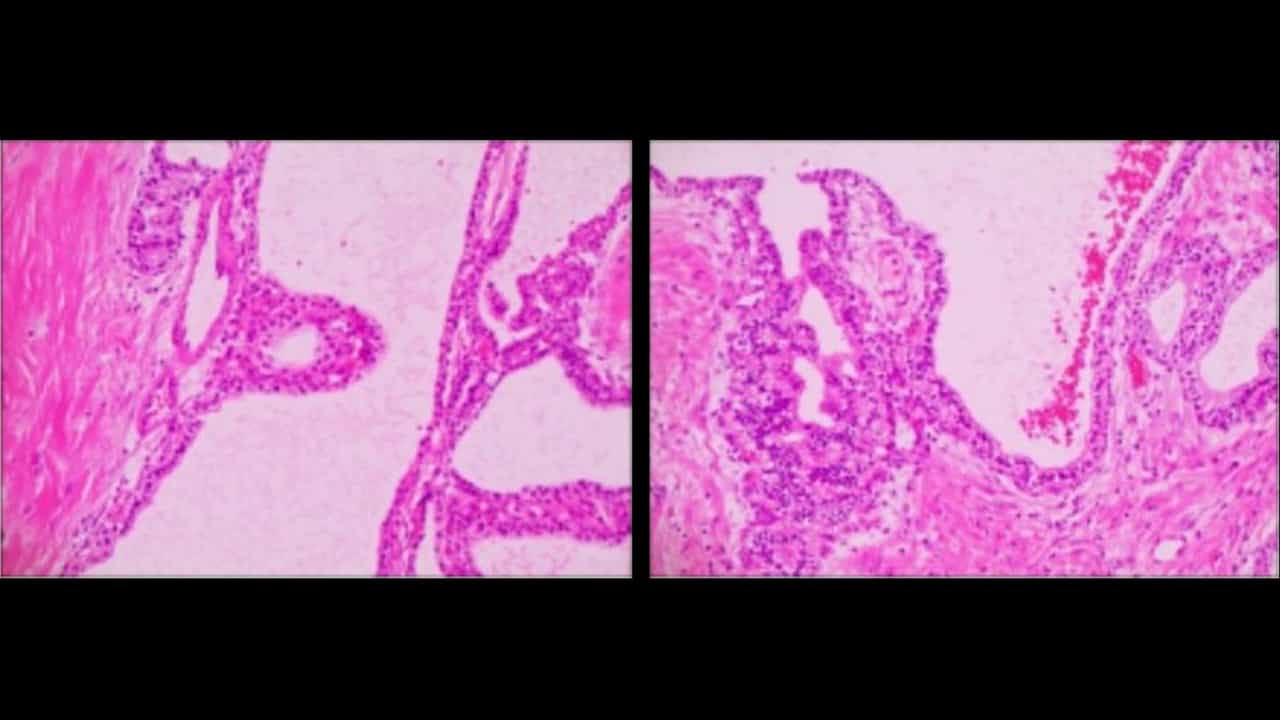

Pancreatic Cystic Lesions: Diagnostic, Management and Indications for Operation. Part I

Abstract:
We notice an increasing frequency in the detection and evaluation of pancreatic cystic lesions (PCLs) over the last three decades. They show awide spectrum of imaging and clinical features. The diagnosis and discrimination of these lesions are very important because of the risk for concurrent or later development of malignancy. The main reason is the increased awareness of these lesions and the extensive use of cross-sectional imaging, an always improving technique (1). Commonly, PCLs are diagnosed incidentally during investigation for often unrelated and nonspecific abdominal complaints using state-of-the art abdominal imaging (CT, MRT). The term PCN denotes a histologically heterogeneous collection of neoplasms showing a wide spectrum of diagnoses, ranging from completely benign to potentially malignant, to carcinoma in situ, to frankly invasive and malignant (2,3). In 1978, Compagno and Oertel were the first to recognize the crucial distinction between the serous and the mucinous cystic neoplasms of the pancreas by explaining the importance of identifying the mucinous neoplasms because of their overt or latent malignant potential (4,5). Since then, the interest in PCLs increased markedly, especially so with the recognition of the importance and prevalence of intraductal papillary mucinous neoplasms (IPMNs). Nowadays, PCLs represent a common and often difficult challenge in clinical practice, because of the increase in their detection in asymptomatic patients and our still immature understanding of some aspects of their biologic behavior. Their important differences regarding their outcome and the fact of being increasingly often identified has put a special focus on these neoplasms by surgeons, pathologists, gastroenterologists, radiologists, and oncologists alike. Management of patients with PCNs can be challenging and varies considerably among the various subtypes of PCNs. Their treatment ranges from resection of malignant lesions, to resection and/or surveillance in the case of premalignant lesions, to simple observation in the case of benign or indolent lesions. Under these circumstances, the accurate classification of PCNs becomes crucial. Therapeutic decision making and classification rely mainly on the presenting symptoms and radiologic findings, often without actual histologic tissue. It is of extreme importance to identify suspicious features indicating potential or certain malignancy in order to select the appropriate treatment. The risk of overtreatment (unnecessary pancreatectomy) should he balanced carefully with the risk of under treatment (missing the opportunity to cure a potentially curable malignant or premalignant disease).
More Related Videos
 03:34
Laparoscopic Duodenum-Preserving Pancreatic Head Resection via Inferior Infracolic Approach: A Surgical Approach for Benign Lesions
Published on: February 9, 2024
 14:56
Application of Indocyanine Green Fluorescence Imaging Technology in Laparoscopic Duodenum-Preserving Pancreatic Head Resection
Published on: November 21, 2025
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...