Related Experiment Video
Updated: Mar 3, 2026


Generation of Human Nasal Epithelial Cell Spheroids for Individualized Cystic Fibrosis Transmembrane Conductance Regulator Study
Published on: April 11, 2018
Low Beta-Adrenergic Sweat Responses in Cystic Fibrosis and Cystic Fibrosis Transmembrane Conductance
Danieli Barino Salinas1, Lucia Kang1, Colleen Azen2
1Department of Pediatrics-Pediatric Pulmonology, Children's Hospital Los Angeles, Keck School of Medicine-University of Southern California (USC), Los Angeles, California.

Insights
The β-adrenergic sweat test is safe for children with cystic fibrosis (CF) or CFTR-related metabolic syndrome (CRMS). However, this test did not differentiate between CF and CRMS groups in young children.
Area of Science:
- Pediatric endocrinology
- Pulmonology
- Medical diagnostics
Background:
- β-adrenergic stimulated sweat secretion is dependent on the cystic fibrosis transmembrane conductance regulator (CFTR) function.
- CFTR dysfunction distinguishes cystic fibrosis (CF) patients from healthy individuals.
- Newborn screening for CF identifies infants who may have CF or CFTR-related metabolic syndrome (CRMS), necessitating prognostic tools.
Purpose of the Study:
- To assess the feasibility, safety, and efficacy of the β-adrenergic sweat test in preschool-aged children identified through CF newborn screening.
- To determine if β-adrenergic sweat testing can help differentiate prognoses for individuals with CFTR-related metabolic syndrome (CRMS).
Main Methods:
- A cross-sectional study involving preschool-aged children (4-6 years) with positive CF newborn screening results.
- Sweat rates measured by evaporimetry (transepidermal water loss) before and after cholinergic or β-adrenergic stimulation.
- Comparison of net peak sweat responses between CF (n=16) and CRMS (n=10) cohorts.
Main Results:
- The β-adrenergic sweat test protocol was well-tolerated in children, with normal vital signs and electrocardiograms.
- Mean evaporative sweat rates were similar between CF and CRMS groups following both cholinergic (p=0.72) and β-adrenergic (p=0.14) stimulation.
- Evaporimetry-measured β-adrenergic sweat secretion rates did not distinguish between the CF and CRMS cohorts.
Conclusions:
- The β-adrenergic sweat test is a safe and well-tolerated diagnostic method for young children.
- Current evaporimetry-based β-adrenergic sweat testing does not differentiate between CF and CRMS in this pediatric population.
- Further research may be needed to refine sweat testing methodologies for prognostic determination in CRMS patients.
Abstract:
β-adrenergically stimulated sweat secretion depends on the function of the cystic fibrosis transmembrane conductance regulator (CFTR) and discriminates between cystic fibrosis (CF) patients and healthy controls. Therefore, we sought to determine the feasibility, safety, and efficacy of assaying β-adrenergic sweating in children identified by CF newborn screening to help determine prognoses for individuals with CFTR-related metabolic syndrome (CRMS). Preschool age children with a positive newborn screening test for CF participated in this cross-sectional study. Sweat rates were measured by evaporimetery (cyberDERM, inc.) as transepidermal water losses (g H2O/m2/h) before and after selectively stimulating sweat glands either cholinergically or β-adrenergically. Net peak sweat responses assayed as evaporation rates were compared between CF and CRMS cohorts. After a pilot test in adults, children between 4 and 6 years of age were evaluated (CF, n = 16; CRMS, n = 10). The test protocol was well tolerated; electrocardiograms and vital signs were within normal range for all subjects. The mean evaporative sweat rates in both groups in response to cholinergic stimulation were similar (CF, 60.3 ± 23.8; CRMS, 57.7 ± 13.9; p = 0.72) as well as to β-adrenergic stimulation (CF, 1.1 ± 1.7; CRMS, 2.0 ± 2.0; p = 0.14). The β-adrenergic sweat test is safe and well tolerated by young children. However, the β-adrenergic sweat secretion rates as measured by evaporimetery did not discriminate between CF and CRMS cohorts.

Related Concept Videos
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation,...
 01:26
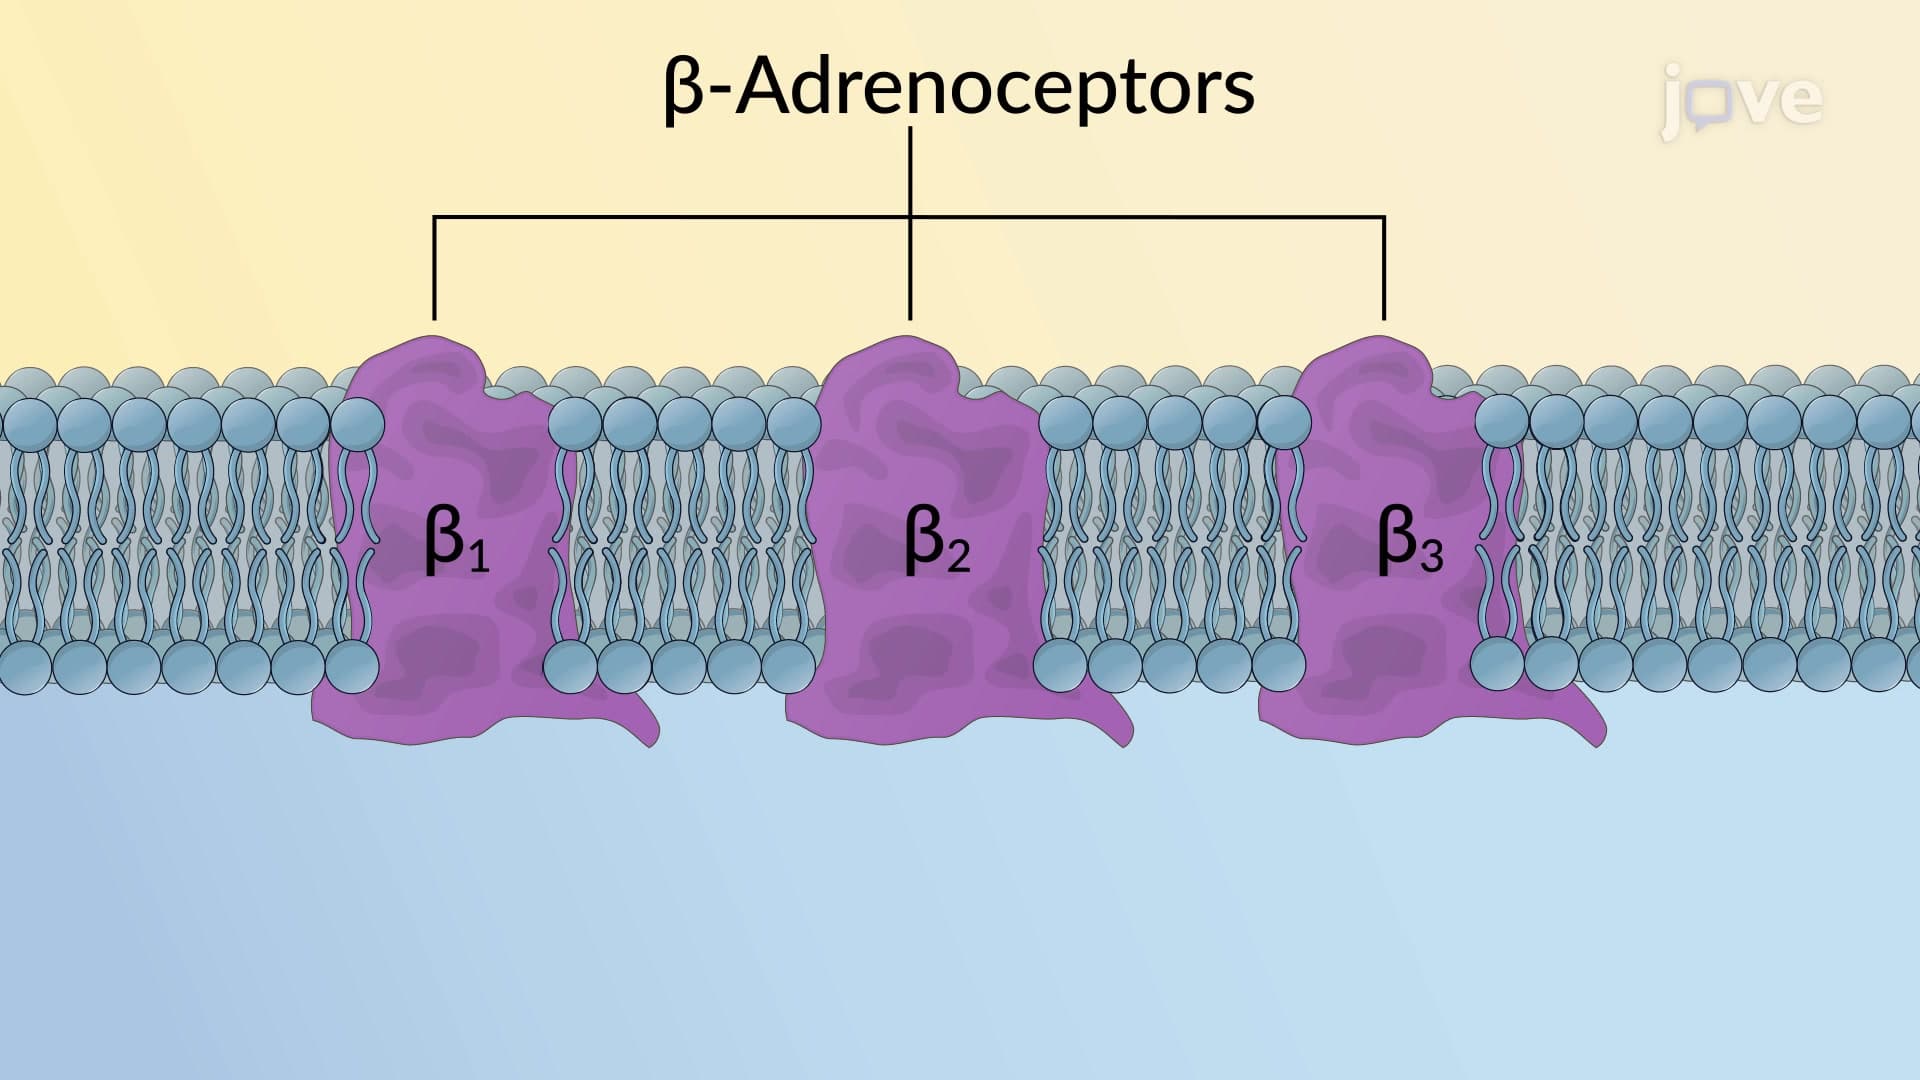
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:24
Cystic Fibrosis: Management
Sinus disease and chronic...
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors,...
 01:19
Overview of Carbohydrate Metabolism
Glucose transport into cells is facilitated by a family of transport proteins called GLUT (Glucose Transporters). GLUT4 is the primary glucose transporter for insulin-stimulated glucose...