Related Experiment Video
Updated: Mar 2, 2026
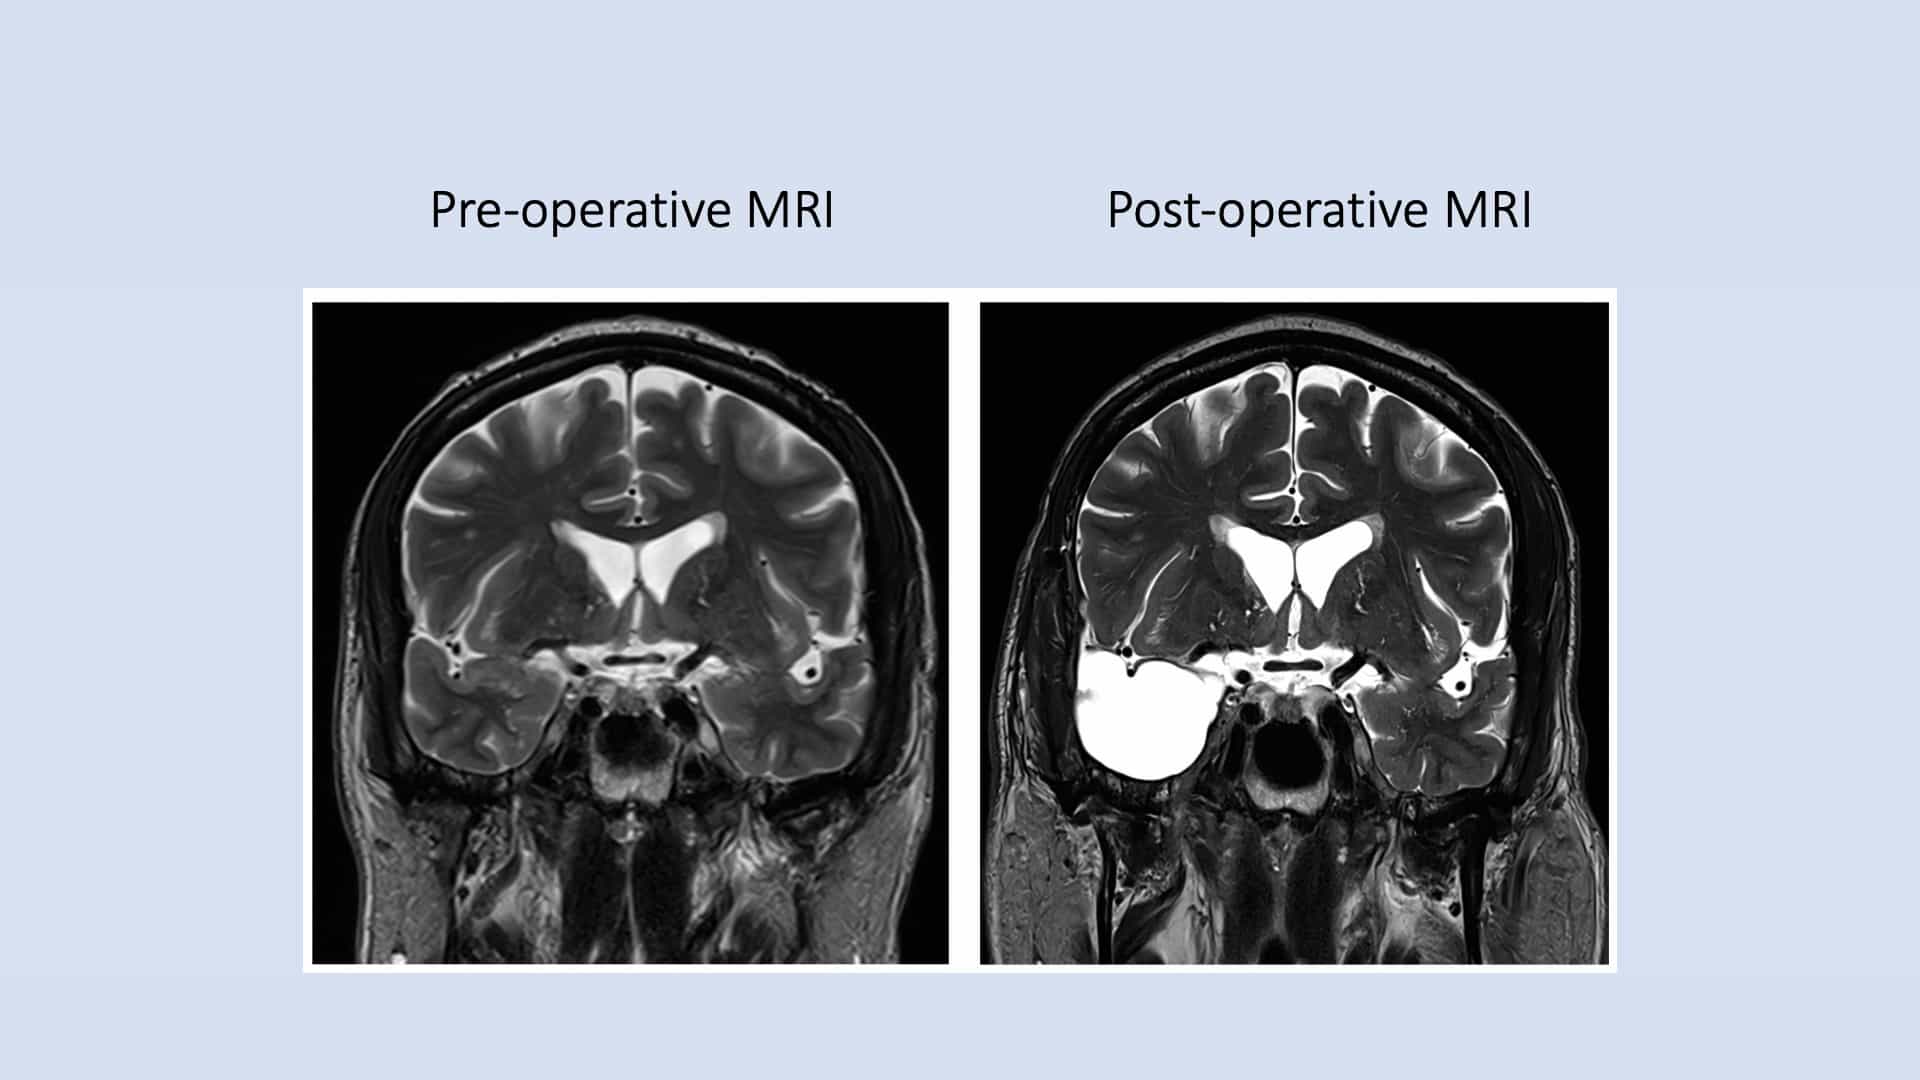

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Usefulness of StereoEEG-based tailored surgery for medial temporal lobe epilepsy. Preliminary results in 11 patients
Yuichi Kubota1, Taku Ochiai2, Tomokatsu Hori3
1Department of Neurosurgery, Tokyo Women's Medical University, Shinjuku, Tokyo, Japan.

Objective:
Surgical options for medial temporal lobe epilepsy (MTLE) include anterior temporal lobectomy (ATL) and selective amygdalohippocampectomy (SAH). Optimal criteria for choosing the appropriate surgical approach remain uncertain. This article reports 11 consecutive cases in which electrophysiological findings of stereoelectroencephalography (SEEG) were used to determine the optimal surgical approach.
Patients And Methods:
Eleven consecutive patients with MTLE underwent SEEG evaluation and were placed in either the medial or the medial+lateral group based on the findings. Patients in the medial group underwent SAH using the subtemporal approach, and patients in the medial+lateral group underwent SEEG-guided anterior temporal lobectomy. SEEG findings were also compared with other examinations including flumazenil (FMZ)-positron emission tomography (PET), fluorine-18 labeled fluorodeoxyglucose (FDG)-PET, and magnetoencephalography (MEG). Results were evaluated to determine which examinations most consistently identified the epileptogenic zone.
Results:
Of the 11 cases, 4 patients were placed in the medial group, and 7 patients in the medial+lateral group. Of patients, 90.9% were classified in class I of the Engel Epilepsy Surgery Outcome Scale, while 72.7% were classified in class I by the International League Against Epilepsy (ILAE) system. Analyzed by group, 100% of the medial group experienced an Engel class I outcome in the medial group, compared to 85.7% in the medial+lateral group. SEEG findings were comparable with FDG-PET results (10 of 11, 91%).
Conclusion:
Tailored surgery guided by SEEG is an electrophysiologically feasible treatment for MTLE that can result in favorable outcomes. Although seizures are thought to originate in the medial temporal lobe in MTLE, it is important for involvement of the lateral temporal cortex to be also considered in some cases.