Pharmacokinetic and Pharmacodynamic Efficacies of Continuous versus Intermittent Administration of Meropenem in
Hui-Ying Zhao1, Jian Gu2, Jie Lyu1
1Department of Critical Care Medicine, Peking University People's Hospital, Beijing 100044, China.

Background:
The antibiotic meropenem is commonly administered in patients with severe sepsis and septic shock. We compared the pharmacokinetic, clinical, and bacteriological efficacies of continuous infusion of meropenem versus intermittent administration in such patients.
Methods:
Patients admitted to the Intensive Care Unit (ICU) with severe sepsis or septic shock who received meropenem were randomly assigned to either the continuous (n = 25) or intermittent groups (n = 25). The continuous group received a loading dose of 0.5 g of meropenem followed by a continuous infusion of 3 g/day; the intermittent group received an initial dose of 1.5 g followed by 1 g for every 8 h. Clinical success, microbiological eradication, superinfection, ICU mortality, length of ICU stay, and duration of meropenem treatment were assessed. Serial plasma meropenem concentrations for the first and third dosing periods (steady state) were also measured.
Results:
Clinical success was similar in both the continuous (64%) and intermittent (56%) groups (P = 0.564); the rates of microbiological eradication and superinfection (81.8% vs. 66.7% [ P = 0.255] and 4% vs. 16% [ P = 0.157], respectively) showed improvement in the continuous group. The duration of meropenem treatment was significantly shorter in the continuous group (7.6 vs. 9.4 days; P= 0.035), where a better steady-state concentration was also achieved. Peak and trough concentrations were significantly different between the continuous and intermittent groups both in the first (Cmax: 19.8 mg/L vs. 51.8 mg/L, P= 0.000; Cmin: 11.2 mg/L vs. 0.5 mg/L, P= 0.000) and third dosing periods (Cmax: 12.5 mg/L vs. 46.4 mg/L, P= 0.000; Cmin: 11.4 mg/L vs. 0.6 mg/L, P= 0.000). For medium-susceptibility pathogens, continuous infusion concentrations above the minimal inhibitory concentration were 100%, which was better than that in the intermittent group.
Conclusions:
Continuous infusion of meropenem provides significantly shorter treatment duration and a tendency for superior bacteriological efficacy than intermittent administration. Continuous infusion may be more optimal against intermediate-susceptibility pathogens.
Insights
Continuous meropenem infusion in severe sepsis patients led to shorter treatment durations and improved bacterial eradication compared to intermittent dosing. This method may be superior for treating infections caused by intermediate-susceptibility pathogens.
Area of Science:
- Pharmacology
- Infectious Diseases
- Critical Care Medicine
Background:
- Meropenem is a key antibiotic for severe sepsis and septic shock.
- Comparing continuous vs. intermittent meropenem infusion is crucial for optimizing patient outcomes.
Purpose of the Study:
- To compare the pharmacokinetic, clinical, and bacteriological efficacy of continuous versus intermittent meropenem infusion.
- To evaluate meropenem's effectiveness in Intensive Care Unit (ICU) patients with severe sepsis or septic shock.
Main Methods:
- Randomized controlled trial comparing continuous (n=25) and intermittent (n=25) meropenem infusion in ICU patients.
- Assessed clinical success, microbiological eradication, superinfection, mortality, ICU stay, and meropenem treatment duration.
- Measured serial plasma meropenem concentrations at steady state.
Main Results:
- Clinical success rates were similar (64% vs. 56%).
- Continuous infusion showed improved microbiological eradication (81.8% vs. 66.7%) and reduced superinfections (4% vs. 16%).
- Significantly shorter treatment duration (7.6 vs. 9.4 days) and better steady-state concentrations were observed with continuous infusion.
Conclusions:
- Continuous meropenem infusion offers a shorter treatment duration and potentially superior bacteriological efficacy.
- Continuous infusion may be more effective against intermediate-susceptibility pathogens.
More Related Videos


Related Concept Videos
 01:15
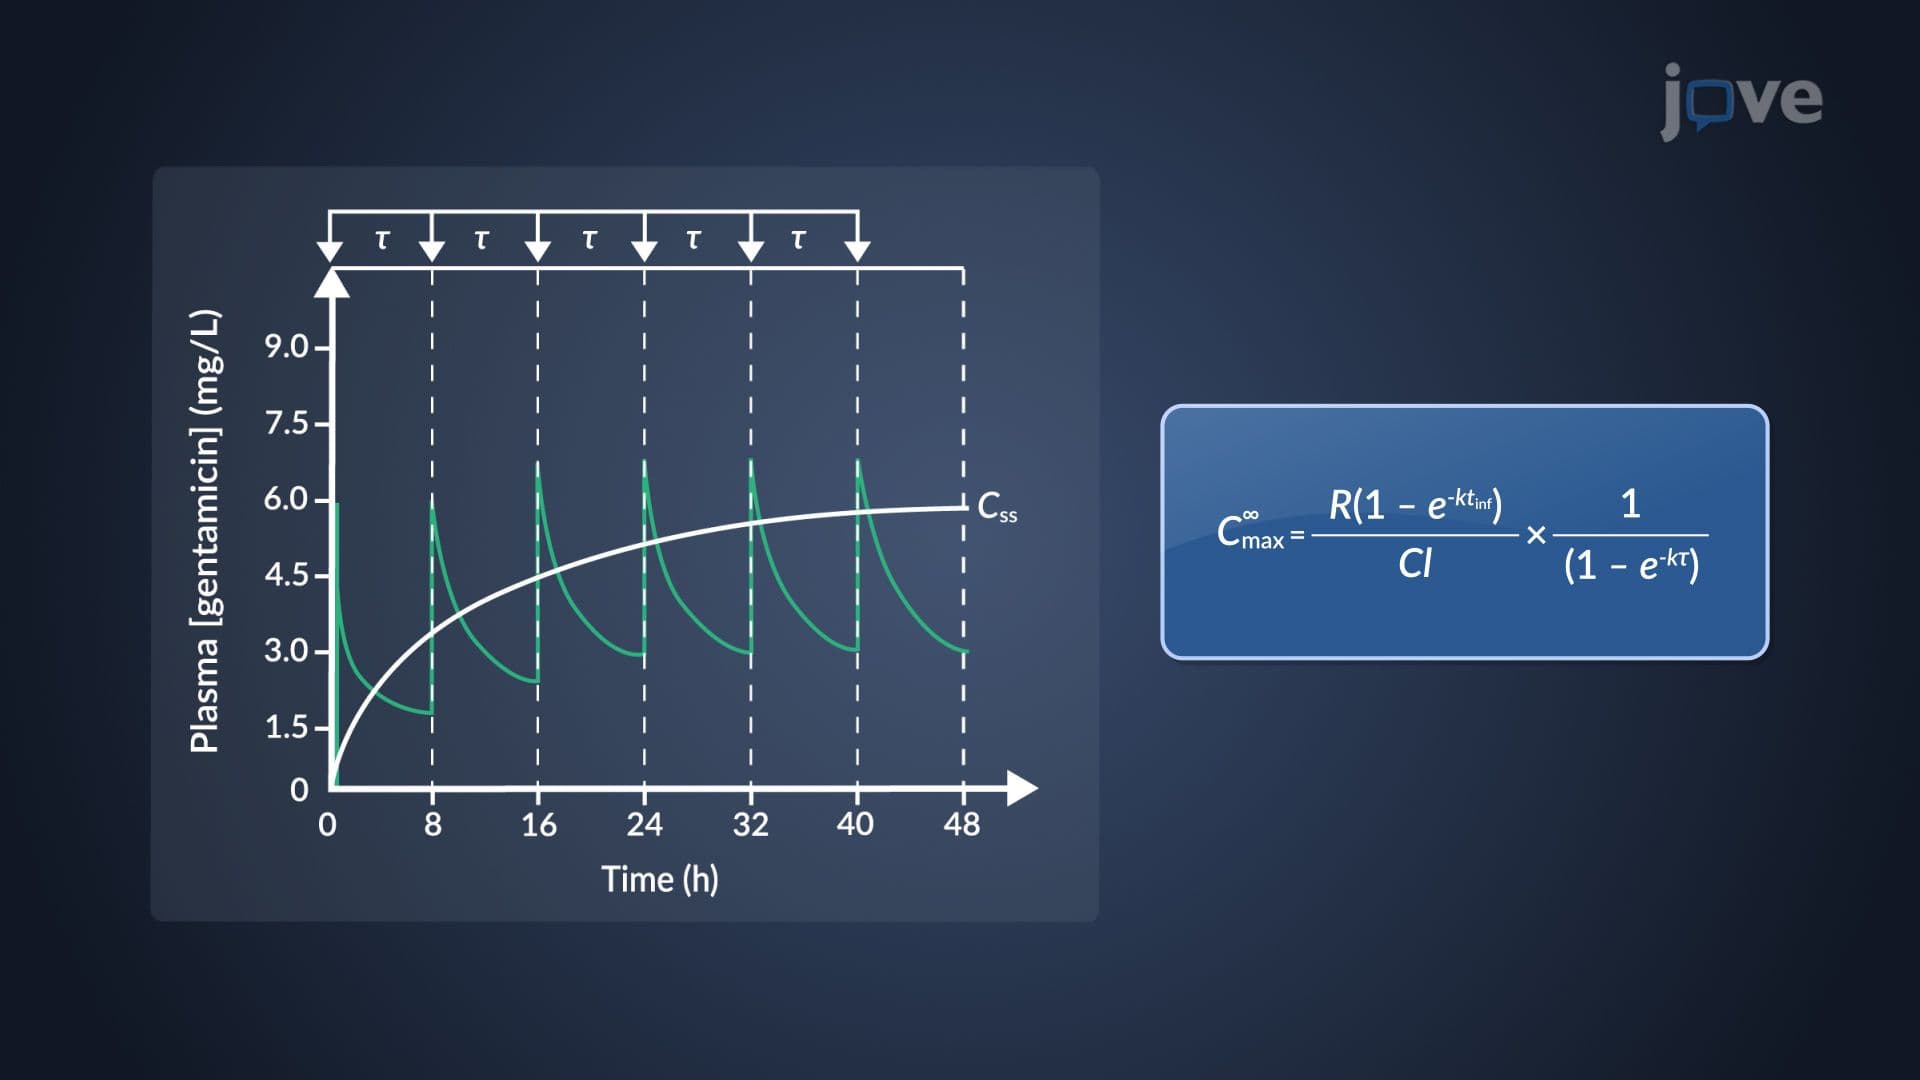
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:24
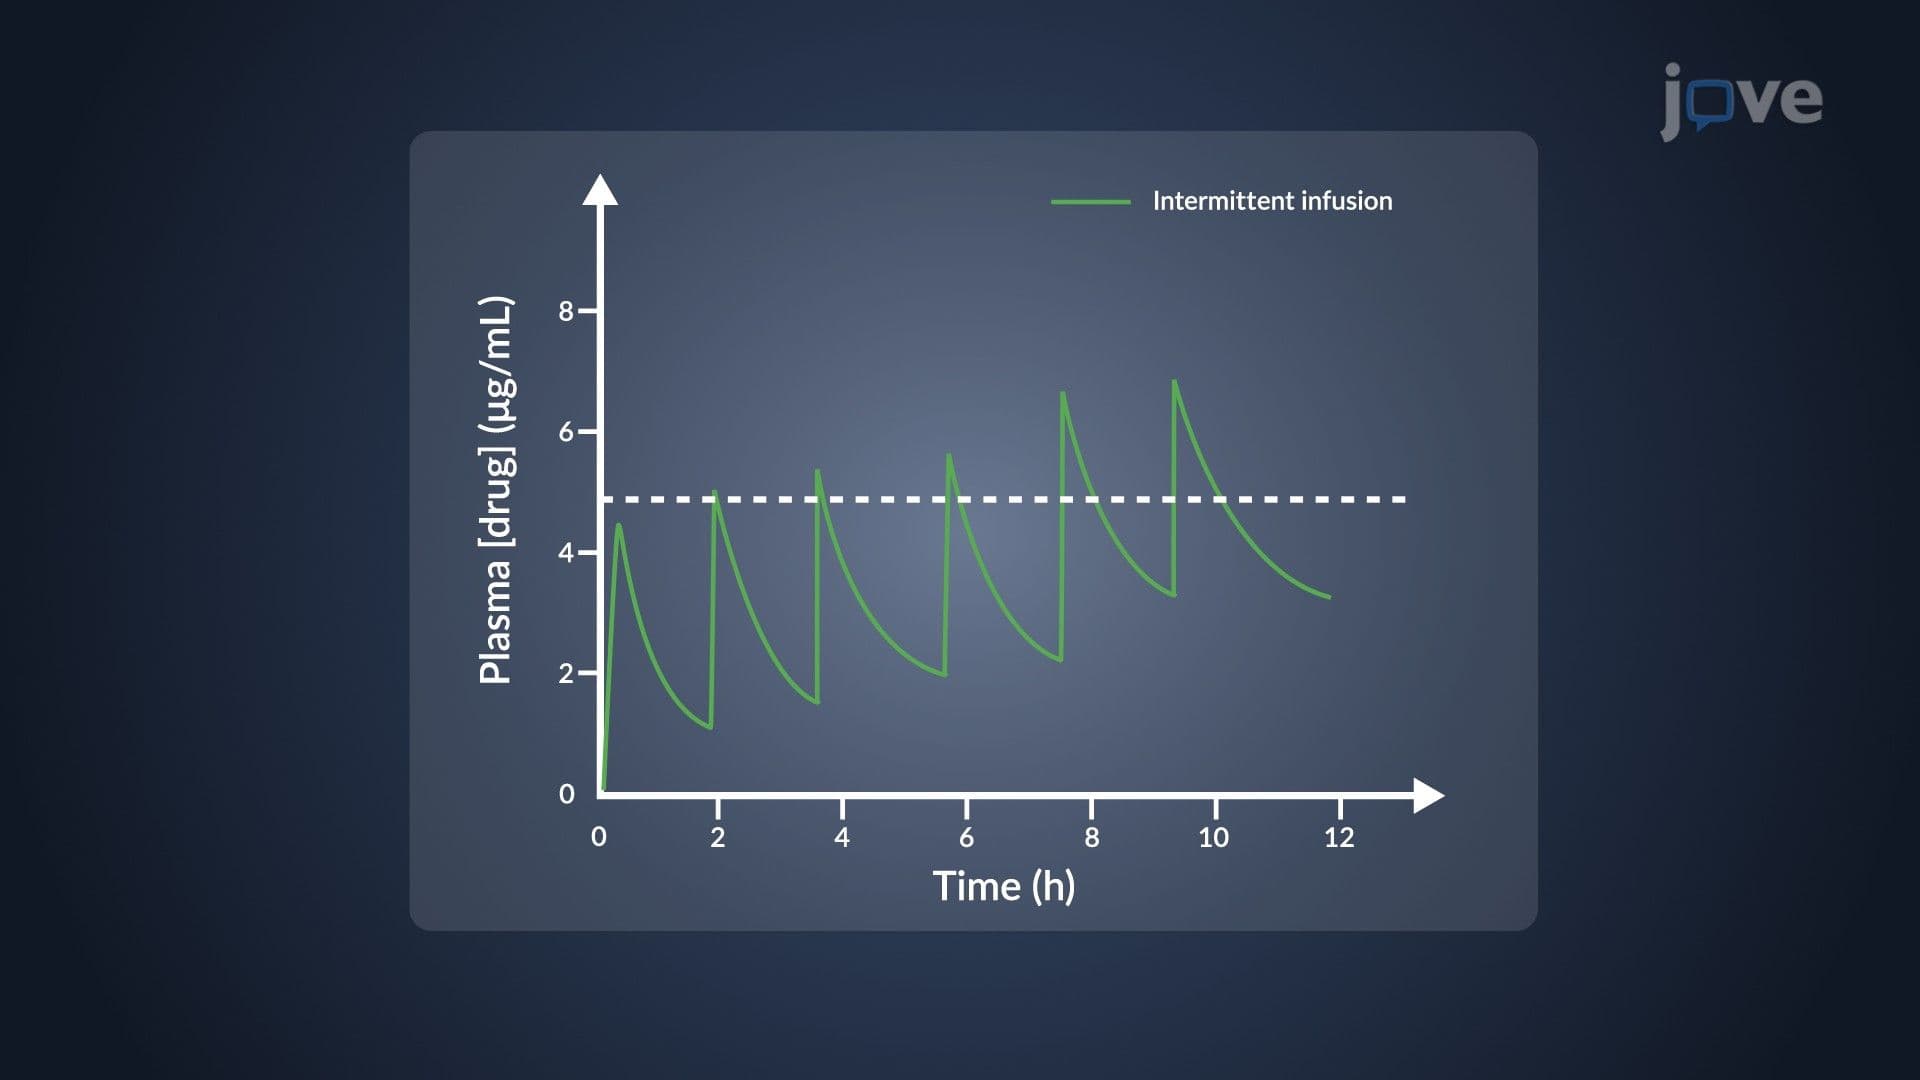
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:19
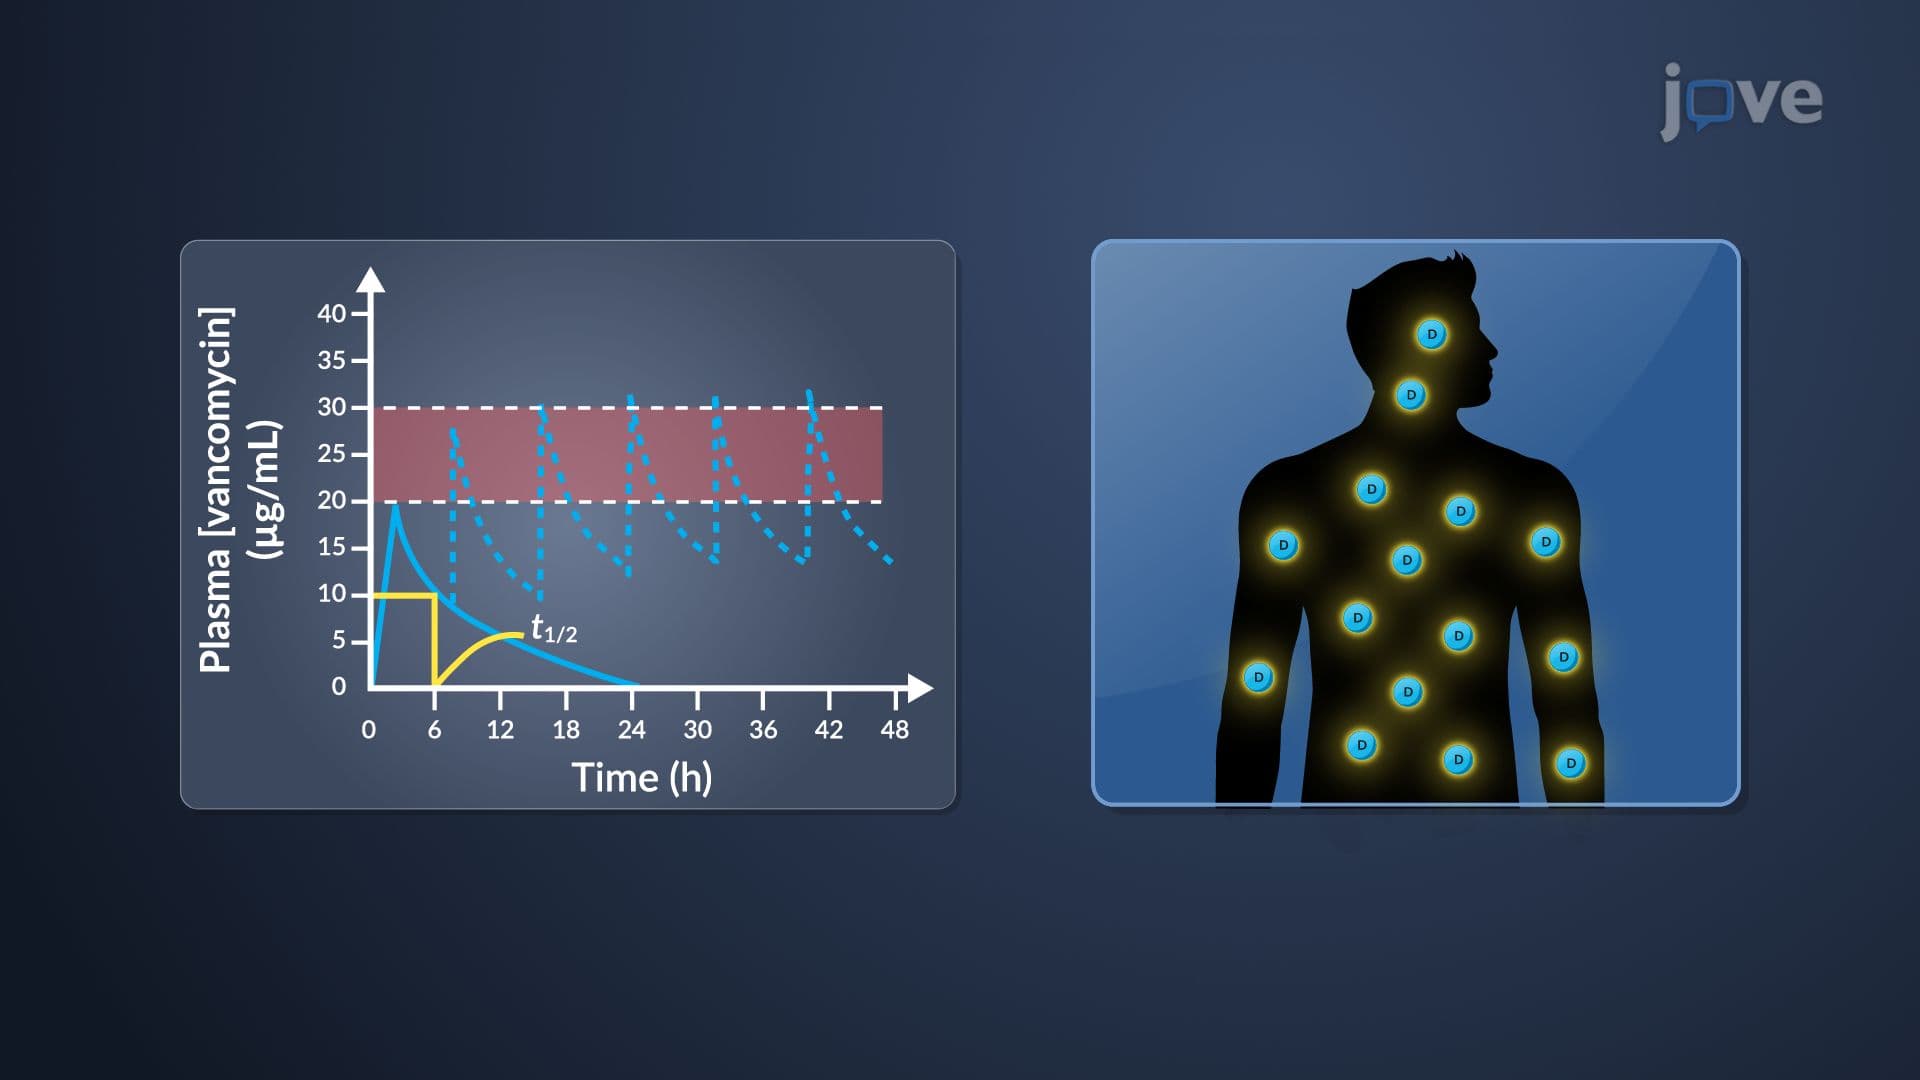
Dosage Interval and Administration Route: Determination Methods