Related Experiment Video
Updated: Mar 2, 2026

Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Respiratory muscle strength and pulmonary function in children with rhinitis and asthma after a six-minute walk test
Ana Alice de Almeida Soares1, Camila Moraes Barros1, Cássia Giulliane Costa Santos1
1a University Hospital, Federal University of Sergipe , Aracaju , Sergipe , Brazil.

Insights
Children with rhinitis and mild asthma show reduced respiratory muscle strength and lung function after exercise, even without symptoms. This highlights the connection between upper and lower airways in pediatric respiratory conditions.
Area of Science:
- Pediatric Pulmonology
- Respiratory Medicine
- Exercise Physiology
Background:
- Rhinitis and asthma significantly impact children's quality of life.
- Limited research exists on the submaximal exercise performance of children with asthma or rhinitis.
- Understanding respiratory responses to exercise is crucial for managing these conditions in pediatric populations.
Purpose of the Study:
- To evaluate maximal respiratory pressures and spirometric parameters in children with rhinitis or mild asthma.
- To assess the ability of these children to sustain submaximal exercise before and after the 6-minute walk test (6MWT).
- To compare the exercise performance and respiratory function of children with rhinitis and mild asthma to healthy children.
Main Methods:
- A cross-sectional study involving 89 children aged 6-12 years, divided into healthy (H), rhinitis (R), and mild asthma (A) groups.
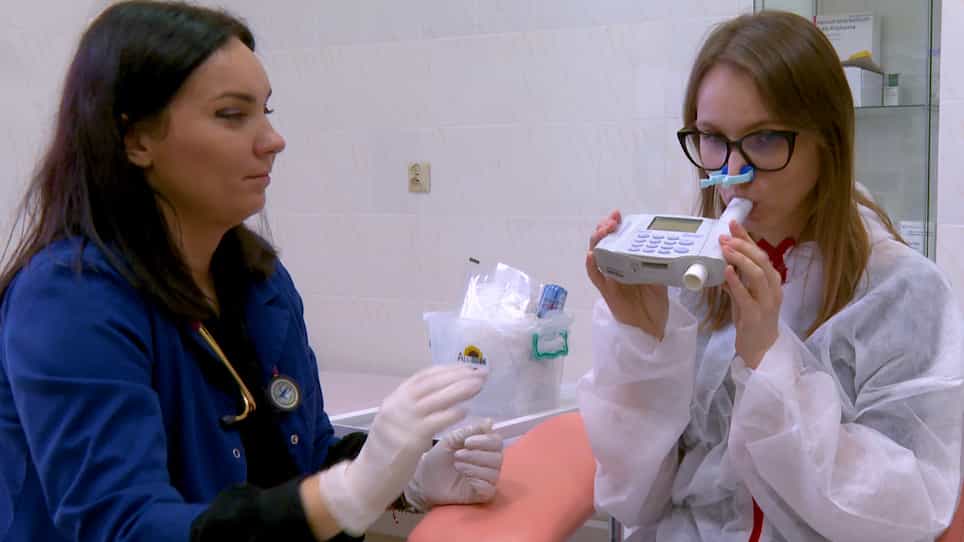
- Measurements included maximal respiratory pressures and spirometric parameters (e.g., FEV1, FEF25-75) taken before and at 5, 10, and 30 minutes post-6MWT.
- Statistical analysis used Wilcoxon test and ANOVA/Kruskal-Wallis test for group comparisons.
Main Results:
- The 6-minute walk test distance was comparable across all groups.
- Children with mild asthma (A) showed significant post-6MWT decreases in FEV1, FEV0.75, and FEF25-75.
- Children with rhinitis (R) exhibited significant post-6MWT reductions in FEV0.75, FEF25-75, and FEV1/CVF, alongside lower maximal inspiratory pressures in both A and R groups compared to H.
Conclusions:
- Children with rhinitis and mild asthma demonstrate impaired respiratory muscle strength and pulmonary function after submaximal exercise.
- These functional alterations occur even in the absence of overt clinical symptoms.
- The findings support the concept of 'united airways,' emphasizing the link between upper and lower respiratory tract conditions.
Objective:
Rhinitis and asthma decrease quality of life. Few studies have assessed the performance of children with asthma or rhinitis under submaximal exercise. We evaluated maximal respiratory pressures, spirometric parameters, and ability to sustain submaximal exercise in these children before and after the 6-minute walk test (6MWT), compared to healthy children.
Methods:
This cross-sectional, analytical study included 89 children aged 6-12 years in outpatient follow-up: 27 healthy (H), 31 with rhinitis (R), and 31 with mild asthma under control (A). Pulmonary function parameters and maximal respiratory pressures were measured before and 5, 10, and 30 minutes after the 6MWT. Wilcoxon test was used to compare numerical numerical variables between two groups and analysis of variance or Kruskal-Wallis test for comparison among three groups.
Results:
Total distance traveled in the 6MWT was similar among the three groups. Compared to pre-test values, VEF1 (Forced Expiratory Volume in 1 second), VEF0.75 (Forced Expiratory Volume in 0.75 second), and FEF25-75 (Forced Expiratory Flow 25-75% of the Forced Vital Capacity - CVF - curve) decreased significantly after the 6MWT in group A, and VEF0.75, FEF25-75, and VEF1/CVF decreased significantly in group R. Groups A and R had lower Maximum Inspiratory Pressure values than group H before and after the 6MWT at all time points assessed.
Conclusions:
The findings suggest that children with rhinitis and mild asthma present with alterations in respiratory muscle strength and pulmonary function not associated with clinical complaints, reinforcing the concept of the united airways.
More Related Videos
Related Concept Videos
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma