Related Experiment Video
Updated: Mar 2, 2026
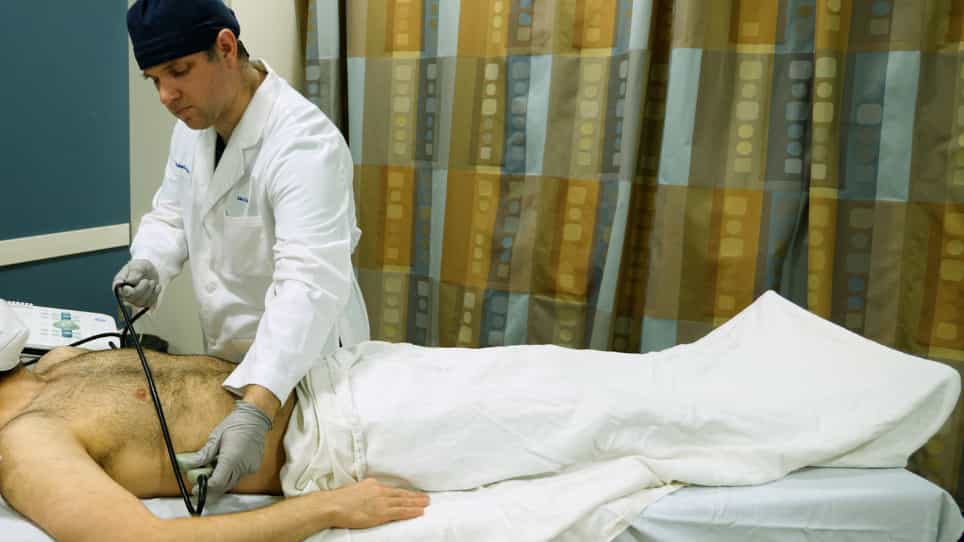
Focused Assessment with Sonography for Trauma FAST Exam: Image Acquisition
Published on: September 22, 2023
Detection of pneumothoraces in patients with multiple blunt trauma: use and limitations of eFAST
Thomas C Sauter1, Simon Hoess1, Beat Lehmann1
1Department of Emergency Medicine, Inselspital, Bern University Hospital, University of Bern, Freiburgstrasse, Bern, Switzerland.

Background:
Extended focused assessment with sonography for trauma (eFAST) has been shown to have moderate sensitivity for detection of pneumothorax in trauma. Little is known about the location or size of missed pneumothoraces or clinical predictors of pneumothoraces in patients with false-negative eFAST.
Methods:
This retrospective cross-sectional study includes all patients with multiple blunt trauma diagnosed with pneumothorax who underwent both eFAST and CT performed in the ED of a level 1 trauma centre in Switzerland between 1 June 2012 and 30 September 2014. Sensitivity of eFAST for pneumothorax was determined using CT as the gold standard. Demographic and clinical characteristics of those who had a pneumothorax detected by eFAST and those who did not were compared using the Mann-Whitney U or Pearson's χ2 tests. Univariate binary logistic regression models were used to identify predictors for pneumothoraces in patients with negative eFAST examination.
Results:
The study included 109 patients. Overall sensitivity for pneumothorax on eFAST was 0.59 and 0.81 for pneumothoraces requiring treatment. Compared with those detected by eFAST, missed pneumothoraces were less likely to be ventral (30 (47.6%) vs 4 (9.3%), p <0.001) and more likely to be apical and basal (7 (11.1%) vs 15 (34.9%), p=0.003; 11 (17.5%) vs 18 (41.9%), p=0.008, respectively). The missed pneumothoraces were smaller than the detected pneumothoraces (left side: 30.7±17.4 vs 12.1±13.9 mm; right side: 30.2±10.1 vs 6.9±10.2 mm, both p <0.001). No clinical variables were identified which predicted pneumothoraces in falsely negative eFAST. Among those pneumothoraces missed by eFAST, 30% required tube thoracostomy compared with 88.9% of those detected with eFAST.
Conclusion:
In our study, pneumothoraces missed by eFAST were smaller and in atypical locations compared with those detected by eFAST and needed thoracic drainage less often.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:24
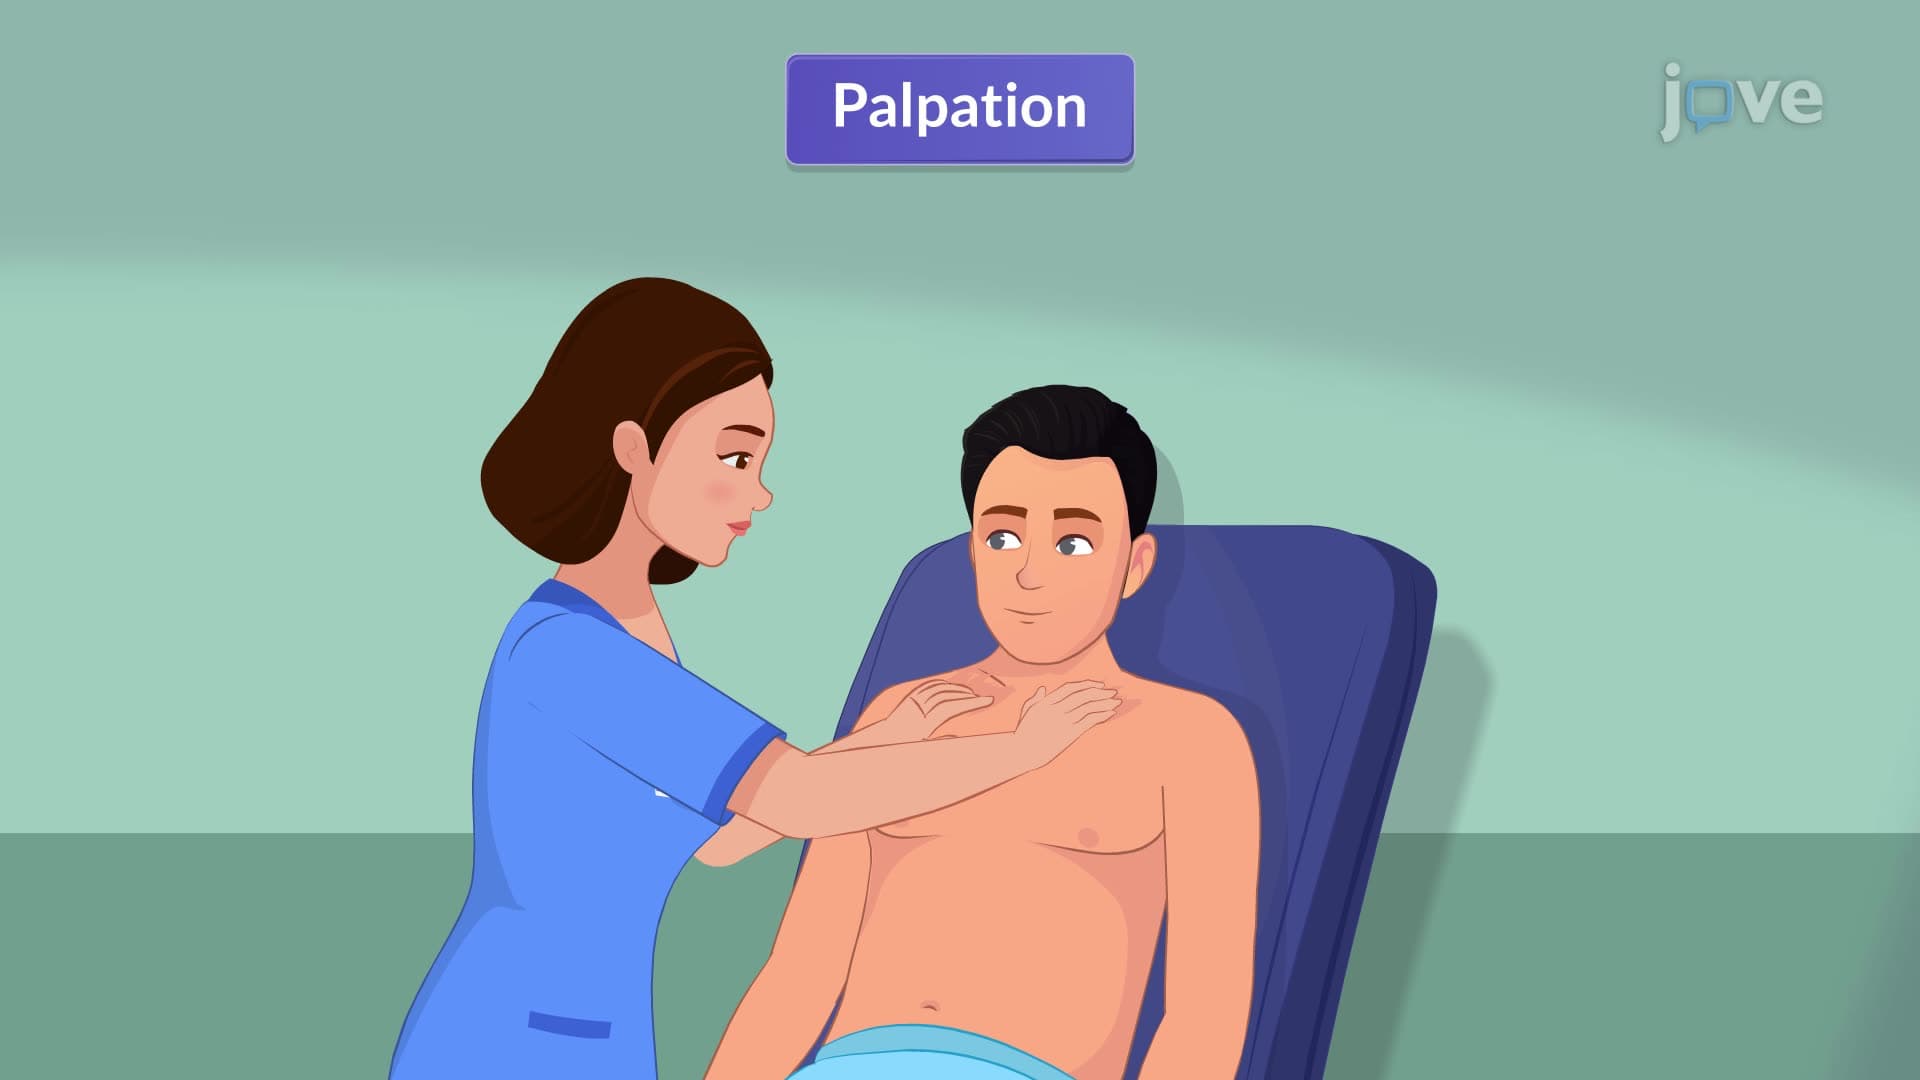
Physical Assessment of the Respiratory Tract II: Palpation
Thoracic Palpation
Thoracic palpation detects tenderness, masses, lesions, respiratory excursions, and vocal fremitus. The nurse assesses...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...