Related Experiment Video
Updated: Mar 2, 2026

A Standardized Procedure of Dressing Management for Toxic Epidermal Necrolysis
Published on: March 14, 2025
Interventions for cutaneous molluscum contagiosum
Johannes C van der Wouden1, Renske van der Sande2, Emma J Kruithof1
1Department of General Practice and Elderly Care Medicine, Amsterdam Public Health Research Institute, VU University Medical Center, PO Box 7057, Amsterdam, Netherlands, 1007 MB.

Background:
Molluscum contagiosum is a common skin infection that is caused by a pox virus and occurs mainly in children. The infection usually resolves within months in people without immune deficiency, but treatment may be preferred for social and cosmetic reasons or to avoid spreading the infection. A clear evidence base supporting the various treatments is lacking.This is an update of a Cochrane Review first published in 2006, and updated previously in 2009.
Objectives:
To assess the effects of specific treatments and management strategies, including waiting for natural resolution, for cutaneous, non-genital molluscum contagiosum in people without immune deficiency.
Search Methods:
We updated our searches of the following databases to July 2016: the Cochrane Skin Group Specialised Register, CENTRAL, MEDLINE, Embase, and LILACS. We searched six trial registers and checked the reference lists of included studies and review articles for further references to relevant randomised controlled trials. We contacted pharmaceutical companies and experts in the field to identify further relevant randomised controlled trials.
Selection Criteria:
Randomised controlled trials of any treatment of molluscum contagiosum in people without immune deficiency. We excluded trials on sexually transmitted molluscum contagiosum and in people with immune deficiency (including those with HIV infection).
Data Collection And Analysis:
Two review authors independently selected studies, assessed methodological quality, and extracted data from selected studies. We obtained missing data from study authors where possible.
Main Results:
We found 11 new studies for this update, resulting in 22 included studies with a total of 1650 participants. The studies examined the effects of topical (20 studies) and systemic interventions (2 studies).Among the new included studies were the full trial reports of three large unpublished studies, brought to our attention by an expert in the field. They all provided moderate-quality evidence for a lack of effect of 5% imiquimod compared to vehicle (placebo) on short-term clinical cure (4 studies, 850 participants, 12 weeks after start of treatment, risk ratio (RR) 1.33, 95% confidence interval (CI) 0.92 to 1.93), medium-term clinical cure (2 studies, 702 participants, 18 weeks after start of treatment, RR 0.88, 95% CI 0.67 to 1.14), and long-term clinical cure (2 studies, 702 participants, 28 weeks after start of treatment, RR 0.97, 95% CI 0.79 to 1.17). We found similar but more certain results for short-term improvement (4 studies, 850 participants, 12 weeks after start of treatment, RR 1.14, 95% CI 0.89 to 1.47; high-quality evidence). For the outcome 'any adverse effect', we found high-quality evidence for little or no difference between topical 5% imiquimod and vehicle (3 studies, 827 participants, RR 0.97, 95% CI 0.88 to 1.07), but application site reactions were more frequent in the groups treated with imiquimod (moderate-quality evidence): any application site reaction (3 studies, 827 participants, RR 1.41, 95% CI 1.13 to 1.77, the number needed to treat for an additional harmful outcome (NNTH) was 11); severe application site reaction (3 studies, 827 participants, RR 4.33, 95% CI 1.16 to 16.19, NNTH over 40).For the following 11 comparisons, there was limited evidence to show which treatment was superior in achieving short-term clinical cure (low-quality evidence): 5% imiquimod less effective than cryospray (1 study, 74 participants, RR 0.60, 95% CI 0.46 to 0.78) and 10% potassium hydroxide (2 studies, 67 participants, RR 0.65, 95% CI 0.46 to 0.93); 10% Australian lemon myrtle oil more effective than olive oil (1 study, 31 participants, RR 17.88, 95% CI 1.13 to 282.72); 10% benzoyl peroxide cream more effective than 0.05% tretinoin (1 study, 30 participants, RR 2.20, 95% CI 1.01 to 4.79); 5% sodium nitrite co-applied with 5% salicylic acid more effective than 5% salicylic acid alone (1 study, 30 participants, RR 3.50, 95% CI 1.23 to 9.92); and iodine plus tea tree oil more effective than tea tree oil (1 study, 37 participants, RR 0.20, 95% CI 0.07 to 0.57) or iodine alone (1 study, 37 participants, RR 0.07, 95% CI 0.01 to 0.50). Although there is some uncertainty, 10% potassium hydroxide appears to be more effective than saline (1 study, 20 participants, RR 3.50, 95% CI 0.95 to 12.90); homeopathic calcarea carbonica appears to be more effective than placebo (1 study, 20 participants, RR 5.57, 95% CI 0.93 to 33.54); 2.5% appears to be less effective than 5% solution of potassium hydroxide (1 study, 25 participants, RR 0.35, 95% CI 0.12 to 1.01); and 10% povidone iodine solution plus 50% salicylic acid plaster appears to be more effective than salicylic acid plaster alone (1 study, 30 participants, RR 1.43, 95% CI 0.95 to 2.16).We found no statistically significant differences for other comparisons (most of which addressed two different topical treatments). We found no randomised controlled trial evidence for expressing lesions or topical hydrogen peroxide.Study limitations included no blinding, many dropouts, and no intention-to-treat analysis. Except for the severe application site reactions of imiquimod, none of the evaluated treatments described above were associated with serious adverse effects (low-quality evidence). Among the most common adverse events were pain during application, erythema, and itching. Included studies of the following comparisons did not report adverse effects: calcarea carbonica versus placebo, 10% povidone iodine plus 50% salicylic acid plaster versus salicylic acid plaster, and 10% benzoyl peroxide versus 0.05% tretinoin.We were unable to judge the risk of bias in most studies due to insufficient information, especially regarding concealment of allocation and possible selective reporting. We considered five studies to be at low risk of bias.
Authors' Conclusions:
No single intervention has been shown to be convincingly effective in the treatment of molluscum contagiosum. We found moderate-quality evidence that topical 5% imiquimod was no more effective than vehicle in terms of clinical cure, but led to more application site reactions, and high-quality evidence that there was no difference between the treatments in terms of short-term improvement. However, high-quality evidence showed a similar number of general side effects in both groups. As the evidence found did not favour any one treatment, the natural resolution of molluscum contagiosum remains a strong method for dealing with the condition.
Insights
No single treatment effectively cures molluscum contagiosum, a common childhood pox virus skin infection. Natural resolution remains a viable option due to a lack of convincing evidence for various interventions.
Area of Science:
- Dermatology
- Infectious Diseases
- Evidence-Based Medicine
Background:
- Molluscum contagiosum is a prevalent pox virus skin infection primarily affecting children.
- While often self-limiting, treatments are sought for cosmetic reasons or to prevent spread.
- A robust evidence base for molluscum contagiosum treatments is currently lacking.
Purpose of the Study:
- To evaluate the efficacy of various treatments for molluscum contagiosum in immunocompetent individuals.
- To assess management strategies, including observation for natural resolution.
Main Methods:
- Systematic updated search of multiple databases (Cochrane Skin Group, CENTRAL, MEDLINE, Embase, LILACS) and trial registers up to July 2016.
- Inclusion of randomized controlled trials (RCTs) for non-genital molluscum contagiosum in immunocompetent patients.
- Independent selection, quality assessment, and data extraction by two review authors.
Main Results:
- 22 RCTs (1650 participants) evaluated topical and systemic interventions.
- Topical 5% imiquimod showed no significant difference in clinical cure compared to vehicle (placebo), with moderate-quality evidence.
- Limited evidence suggests potential efficacy for several topical treatments (e.g., 10% potassium hydroxide, Australian lemon myrtle oil) compared to controls, but with significant uncertainty and low-quality evidence.
Conclusions:
- No single intervention has demonstrated convincing efficacy for molluscum contagiosum treatment.
- Topical 5% imiquimod was not more effective than placebo for cure and increased application site reactions.
- Given the lack of superior evidence, natural resolution remains a primary management strategy for molluscum contagiosum.
Related Concept Videos
 01:30
Skin Cancer
Basal Cell Carcinoma (BCC): BCC is the most common type of skin cancer, accounting for about 80% of cases. It typically develops in...
 01:23
Skin Diseases and Disorders
Gram-positive Staphylococcus spp. and Streptococcus spp. are responsible for many of the most common skin infections. However, many...
 01:23
Hand hygiene
Hand washing...
 01:25
Introduction to the Integumentary System
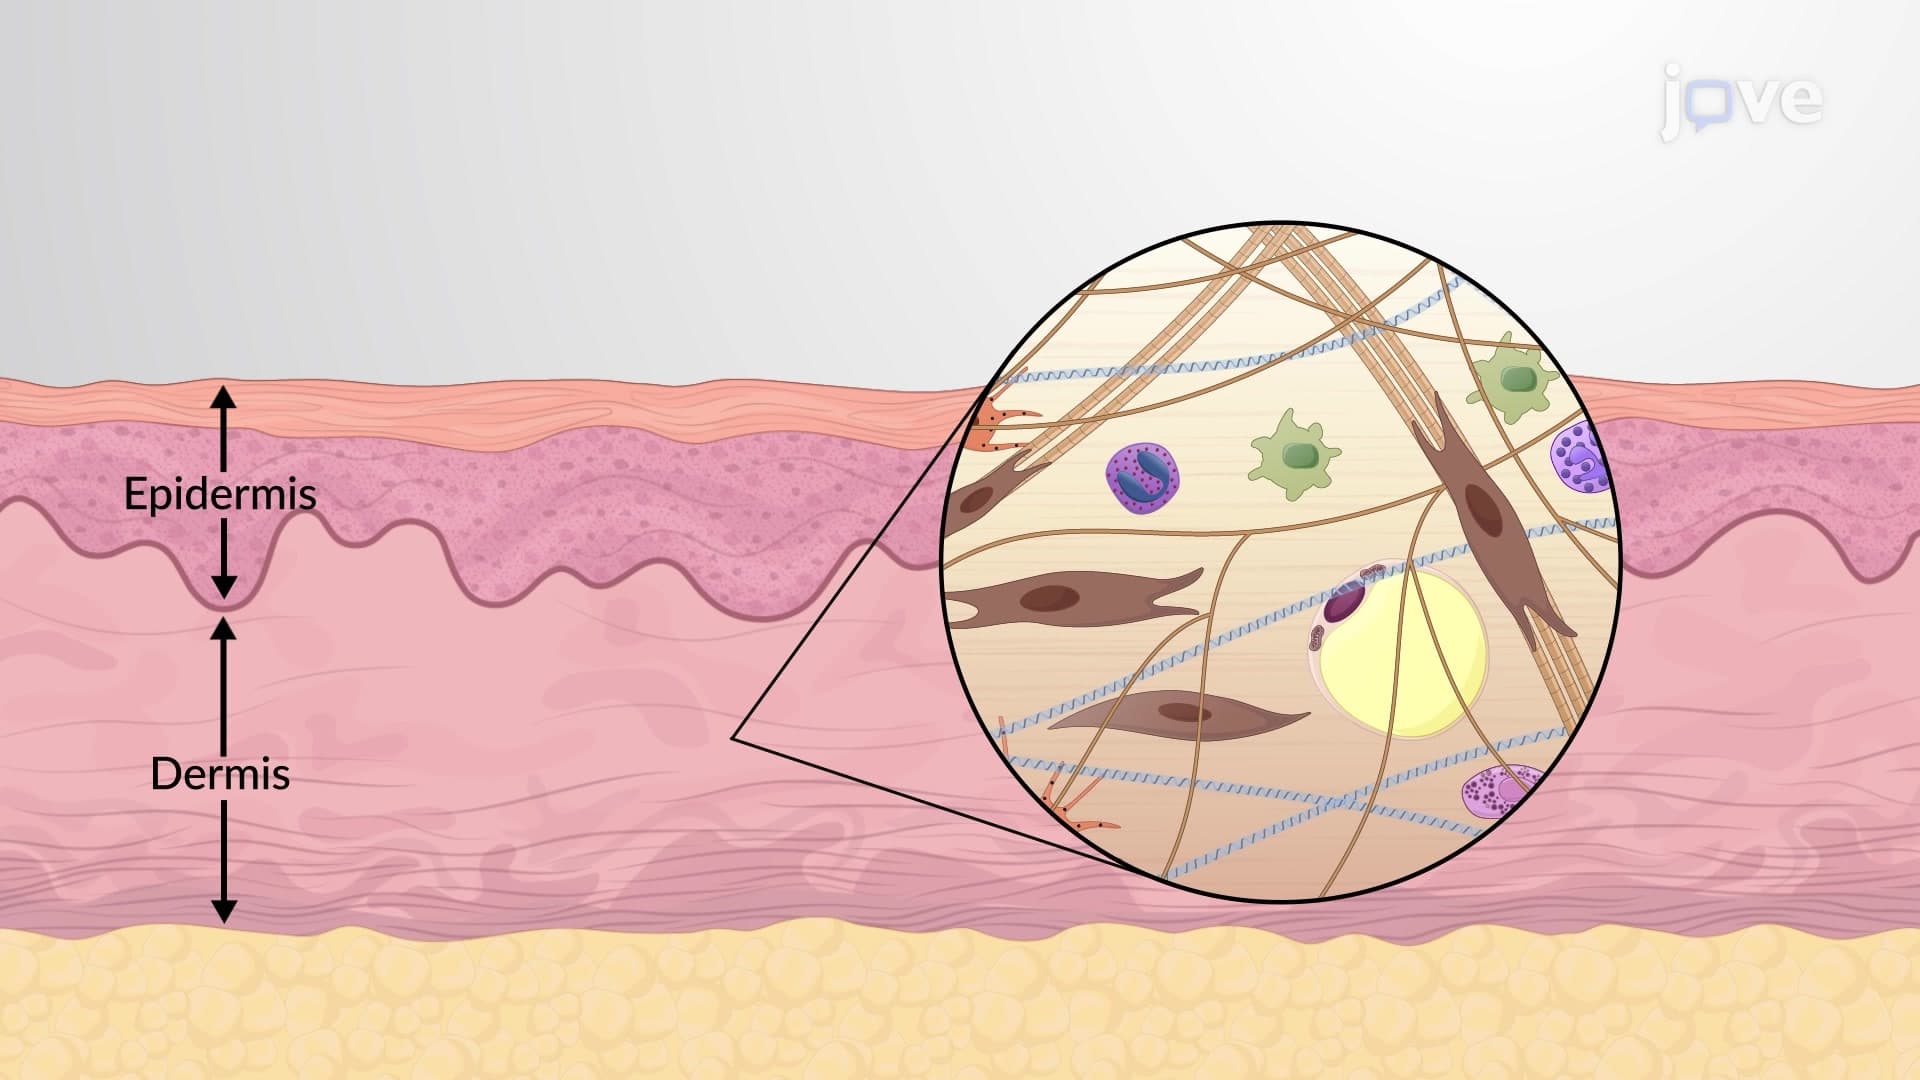
The skin, which is the primary organ of the integumentary system, consists of three main layers: the epidermis, dermis, and hypodermis (subcutaneous tissue). The epidermis is the...
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:14
Changes in Skin Color: Clinical Perspectives
Albinism
Albinism is a genetic disorder that affects (completely or partially) the coloring of skin, hair, and eyes. The defect is primarily...