Related Experiment Video
Updated: Mar 1, 2026


Guidelines for Elective Pediatric Fiberoptic Intubation
Published on: January 17, 2011
Conversion from prolonged intravenous fentanyl infusion to enteral methadone in critically ill children
Vijay Srinivasan1, Daniel Pung1, Sean P O'Neill1
1Vijay Srinivasan, Department of Anesthesiology and Critical Care Medicine, the Children's Hospital of Philadelphia, Philadelphia, PA 19104, United States.

Insights
Rapid conversion from intravenous fentanyl to enteral methadone within 48 hours in critically ill children reduced withdrawal and pain. A methadone to fentanyl dose ratio of approximately 2.5:1 is recommended for successful transitions.
Area of Science:
- Pediatric Critical Care Medicine
- Pharmacology
- Pain Management
Background:
- Critically ill children often require prolonged mechanical ventilation with sedation and analgesia.
- Intravenous (IV) fentanyl is commonly used for sedation and analgesia.
- Transitioning from IV fentanyl to enteral methadone is a strategy to facilitate liberation from intensive care.
Purpose of the Study:
- To describe the institutional experience with direct conversion from IV fentanyl infusion to enteral methadone in mechanically ventilated children.
- To evaluate the occurrence of withdrawal symptoms during this conversion process.
- To identify factors associated with successful conversion and minimal withdrawal.
Main Methods:
- Retrospective study of invasively mechanically ventilated children (0-18 years) receiving IV fentanyl > 5 days.
- Patients were converted directly to enteral methadone.
- Groups were defined as rapid conversion (RCG, ≤48 hours) and slow conversion (SCG, >48 hours).
- Outcomes included withdrawal scores (WAT-1), pain scores, and rescue opioid requirements.
Main Results:
- The rapid conversion group (RCG) had significantly lower withdrawal scores (WAT-1) at 7 days compared to the slow conversion group (SCG) (2.5 vs 5, P=0.027).
- RCG also experienced lower overall pain scores (3 vs 6, P=0.007) and required fewer rescue opioids (3 vs 12, P=0.003).
- The initial methadone:fentanyl daily dose ratio was higher in RCG (2.3:1) than SCG (1.1:1).
Conclusions:
- Direct conversion from IV fentanyl to enteral methadone in critically ill children can be variable.
- Successful conversion within 48 hours, utilizing a methadone:fentanyl dose ratio of approximately 2.5:1, is associated with reduced withdrawal and opioid needs.
- This strategy may improve patient outcomes and facilitate earlier liberation from intensive care.
Aim:
To describe our institutional experience with conversion from intravenous (IV) fentanyl infusion directly to enteral methadone and occurrence of withdrawal in critically ill mechanically ventilated children exposed to prolonged sedation and analgesia.
Methods:
With Institutional Review Board approval, we retrospectively studied consecutively admitted invasively mechanically ventilated children (0-18 years) sedated with IV fentanyl infusion > 5 d and subsequently converted directly to enteral methadone. Data were obtained on subject demographics, illness severity, daily IV fentanyl and enteral methadone dosing, time to complete conversion, withdrawal scores (WAT-1), pain scores, and need for rescue opioids. Patients were classified as rapid conversion group (RCG) if completely converted ≤ 48 h and slow conversion group (SCG) if completely converted in > 48 h. Primary outcome was difference in WAT-1 scores at 7 d. Secondary outcomes included differences in overall pain scores, and differences in daily rescue opioids.
Results:
Compared to SCG (n = 21), RCG (n = 21) had lower median WAT-1 scores at 7 d (2.5 vs 5, P = 0.027). Additionally, RCG had lower overall median pain scores (3 vs 6, P = 0.007), and required less median daily rescue opioids (3 vs 12, P = 0.003) than SCG. The starting daily median methadone dose was 2.3 times the daily median fentanyl dose in the RCG, compared to 1.1 times in the SCG (P = 0.049).
Conclusion:
We observed wide variation in conversion from IV fentanyl infusion directly to enteral methadone and variability in withdrawal in critically ill mechanically ventilated children exposed to prolonged sedation. In those children who converted successfully from IV fentanyl infusion to enteral methadone within a period of 48 h, a methadone:fentanyl dose conversion ratio of approximately 2.5:1 was associated with less withdrawal and reduced need for rescue opioids.


Related Concept Videos
 01:28
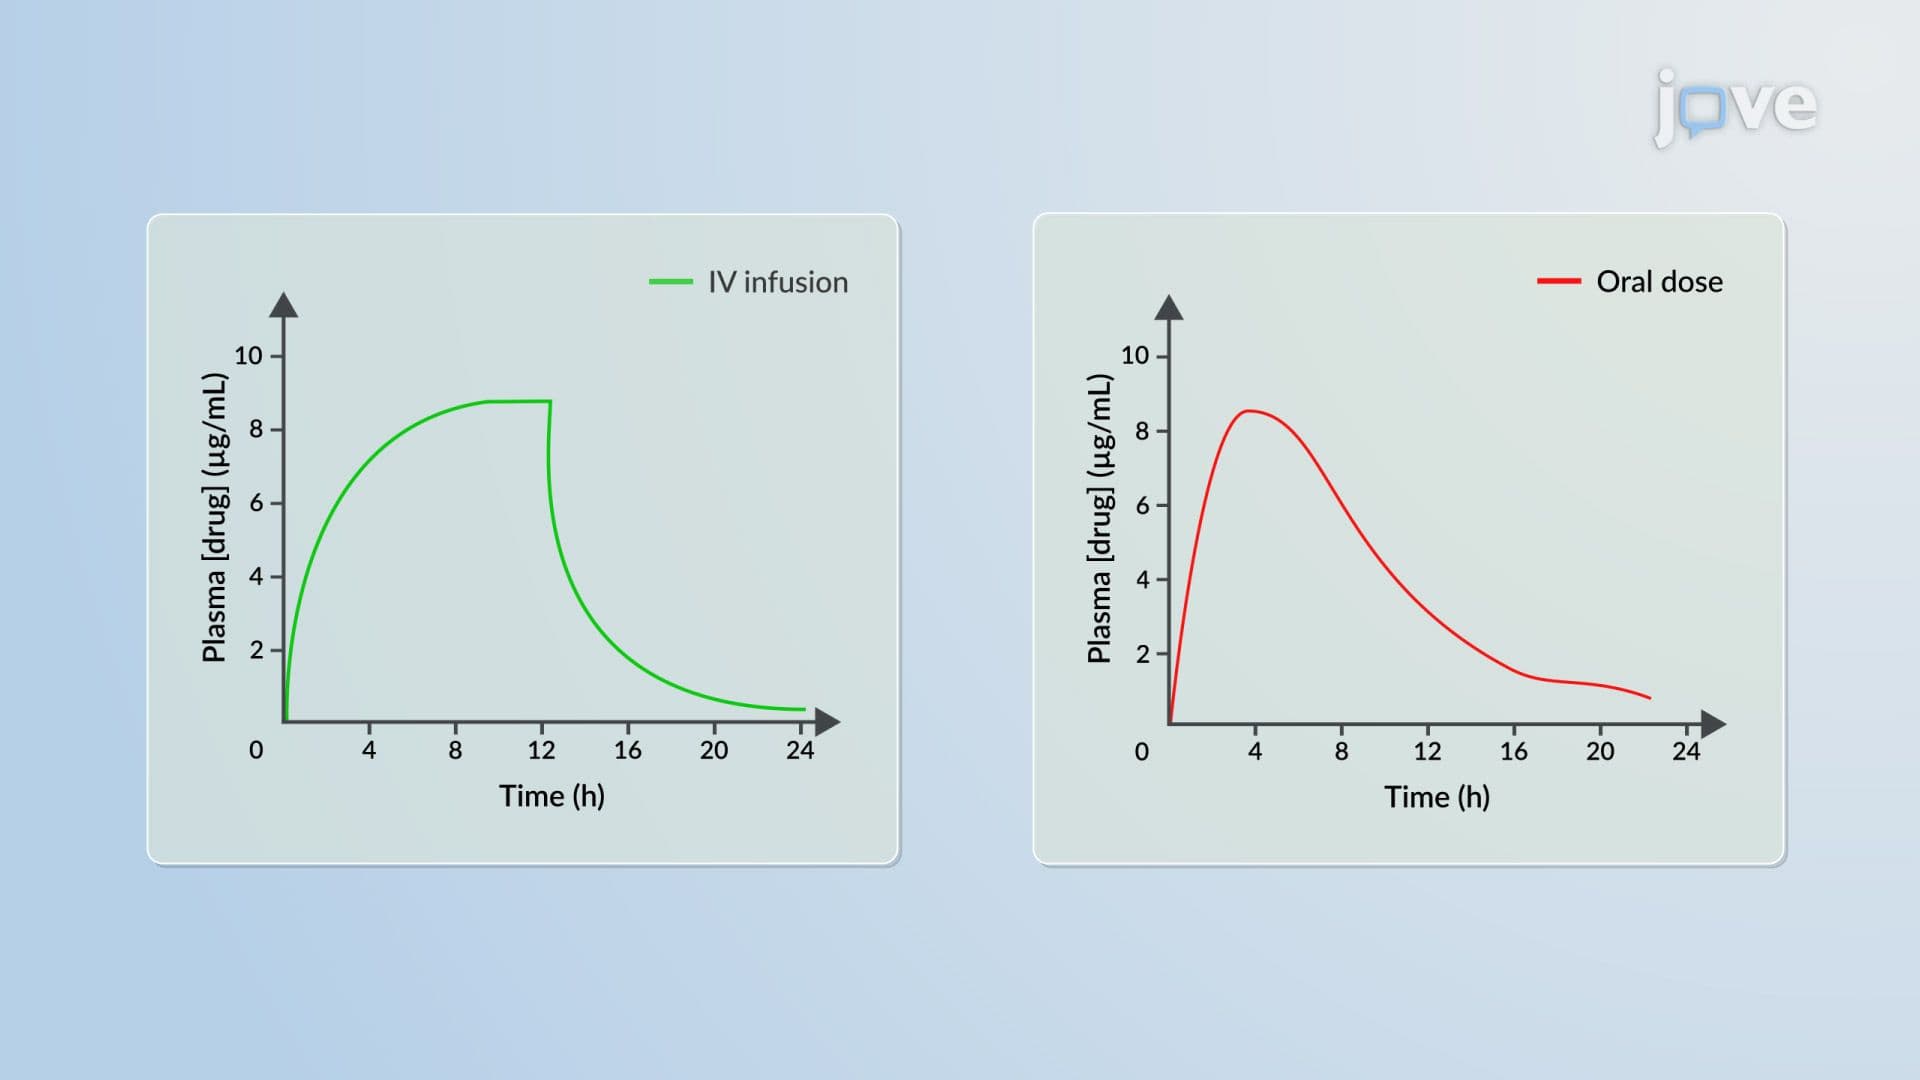
IV Infusion to Oral Dosing: Conversion Methods
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:15
Opioid Analgesics: Synthetic and Semisynthetic Opioids
 01:24
Parenteral Anesthetics: Overview
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:18
Drug Delivery: Enteral Route