Related Experiment Video
Updated: Mar 1, 2026
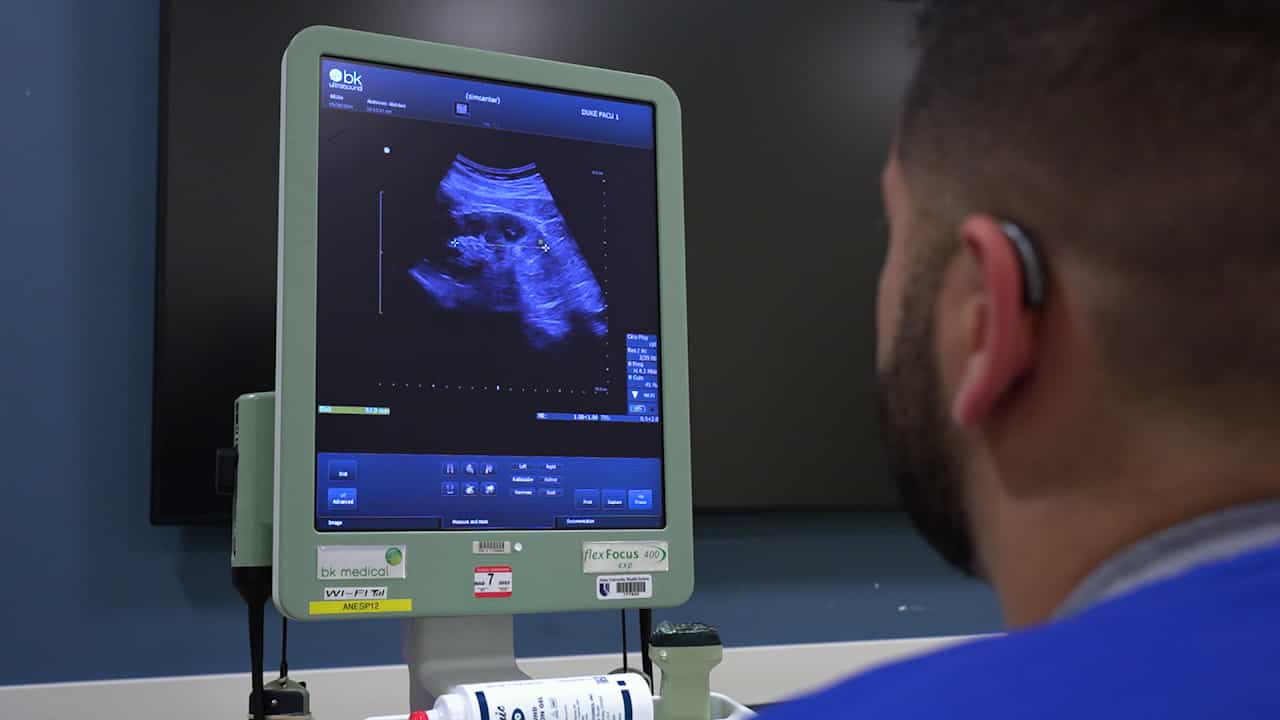

Author Spotlight: Developing a Bedside Protocol for Kidney and Genitourinary Ultrasonography
Published on: June 21, 2024
Indications for kidney biopsy in idiopathic childhood nephrotic syndrome
Alanoud Alshami1, Abishek Roshan1, Marisa Catapang1
1Division of Nephrology, Department of Pediatrics, University of British Columbia, Vancouver, British Columbia, Canada.

Background:
Most cases of childhood nephrotic syndrome (NS) are due to minimal change disease (MCD), while a minority of children have focal segmental glomerulosclerosis (FSGS) and an unfavorable clinical course, requiring a kidney biopsy to confirm diagnosis. We hypothesized that clinical characteristics at diagnosis and initial response to corticosteroid treatment accurately predict FSGS and can be used to guide consistent practice in the indications for kidney biopsy.
Methods:
This was a case control study (1990-2012). Inclusion criteria included age 1-17 years, meeting the diagnostic criteria for NS, and having biopsy-proven FSGS or MCD. Clinical characteristics at diagnosis included age, kidney function [estimated glomerular filtration rate (eGFR)], hypertension, hematuria, nephritis (reduced eGFR, hematuria, hypertension), and response to steroids.
Results:
From a total of 169 children who underwent kidney biopsy for NS we included 65 children with MCD and 22 with FSGS for analysis. There were no significant between-group differences in age, sex, or eGFR at the time of diagnosis. The FSGS group had a higher proportion of hypertension (40 vs. 15%; p = 0.02), hematuria (80 vs. 47%; p = 0.01), and nephritis (22 vs. 2%; p = 0.004) and was more likely to be steroid resistant after 6 weeks of treatment than the MCD group (67 vs. 19%; p < 0.001). As predictors of FSGS, hematuria had a high sensitivity of 0.80 [95% confidence interval (CI) 0.56-0.93] and low specificity of 0.53 (95% CI 0.39-0.66), nephritis had a low sensitivity of 0.22 (95% CI 0.07-0.48) and high specificity of 0.98 (95% CI 0.88-0.99), and steroid resistance had a low sensitivity of 0.67 (95% CI 0.43-0.85) and high specificity of 0.81 (95% CI 0.68-0.90). The combination of steroid resistance after 6 weeks of therapy and/or nephritis at diagnosis yielded the optimal sensitivity and specificity at 0.80 (95% CI 0.56-0.93) and 0.75 (95% CI 0.60-0.86), respectively, confirmed by the highest receiver operator characteristic area under the curve of 0.77.
Conclusion:
Steroid resistance after 6 weeks of therapy and/or nephritis at initial presentation is an accurate predictor of FSGS in children with NS and will be used as the indication for kidney biopsy in our newly developed clinical pathway. This approach will maximize the yield of diagnostic FSGS biopsies while minimizing the number of unnecessary MCD biopsies.
More Related Videos
 09:43
Analyses of Proteinuria, Renal Infiltration of Leukocytes, and Renal Deposition of Proteins in Lupus-prone MRL/lpr Mice
Published on: June 8, 2022
 07:35
Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
Related Concept Videos
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:24
Nephrotic Syndrome I : Introduction
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:24
Nephrotic Syndrome III : Nursing Management
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:10
Nephrons