
Enterovesical Fistula After Enteric Conversion of a Bladder-Drained Pancreatic Allograft: A Case Report
Clifford Akateh1, Amer Rajab, Mitchell Henry
1From the Division of Transplant Surgery, Department of Surgery, The Ohio State University Wexner Medical Center, Columbus, Ohio, USA.

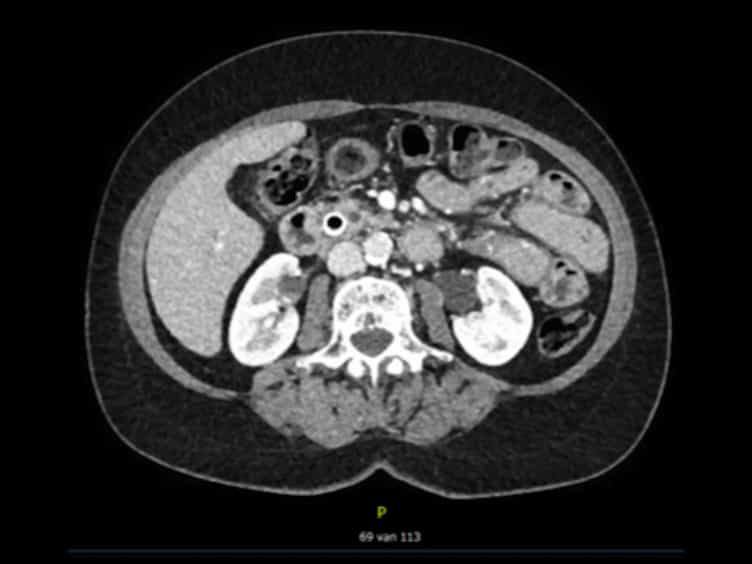
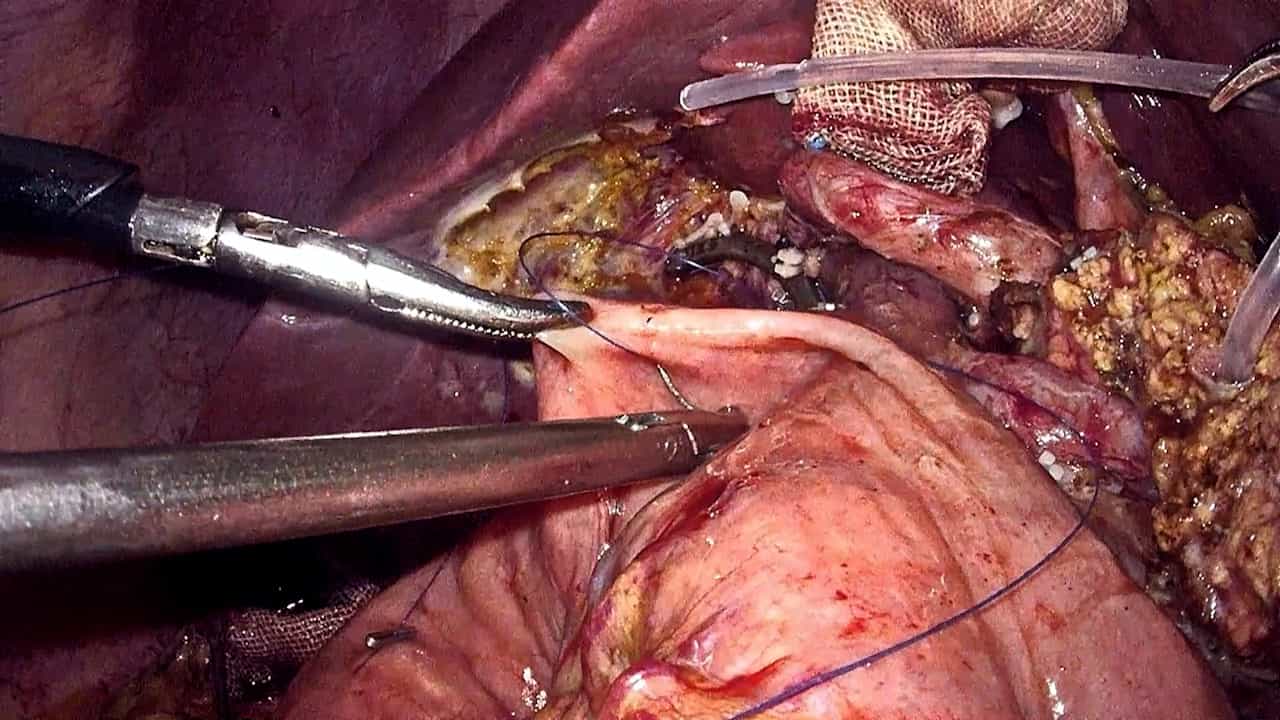
Since the inception of pancreas transplant as a treatment for type 1 diabetes mellitus, there has been considerable debate about the best way to manage exocrine secretions and monitor patients for graft rejection. For patients who undergo bladder exocrine drainage of a pancreatic allograft, a bladder-to-enteric drainage conversion can serve as a rescue procedure in case of anastomotic leaks or other complications. However, this procedure is associated with its own complications, including a rarely described enterovesical fistula. Here we report on a 45-year-old man who underwent a simultaneous kidney and pancreas transplant with bladder drainage to the latter. He developed a pancreatic allograft duodenal leak (duodenal-vesical anastomosis) requiring a bladder-to-enteric drainage conversion. The patient returned 2 weeks after discharge with an enterovesical fistula. He was treated nonsurgically with intravenous antibiotics, bowel rest, and parenteral nutrition, and the fistula successfully closed in approximately 2 weeks. Overall, enterovesical fistula formation is a rare but treatable complication that can occur after a bladder-to-enteric drainage conversion of a pancreatic transplant allograft. It can be managed nonsurgically, which is preferable in these immunocompromised patients.
Since the inception of pancreas transplant as a treatment for type 1 diabetes mellitus, there has been considerable debate about the best way to manage exocrine secretions and monitor patients for graft rejection. For patients who undergo bladder exocrine drainage of a pancreatic allograft, a bladder-to-enteric drainage conversion can serve as a rescue procedure in case of anastomotic leaks or other complications. However, this procedure is associated with its own complications, including a rarely described enterovesical fistula. Here we report on a 45-year-old man who underwent a simultaneous kidney and pancreas transplant with bladder drainage to the latter. He developed a pancreatic allograft duodenal leak (duodenal-vesical anastomosis) requiring a bladder-to-enteric drainage conversion. The patient returned 2 weeks after discharge with an enterovesical fistula. He was treated nonsurgically with intravenous antibiotics, bowel rest, and parenteral nutrition, and the fistula successfully closed in approximately 2 weeks. Overall, enterovesical fistula formation is a rare but treatable complication that can occur after a bladder-to-enteric drainage conversion of a pancreatic transplant allograft. It can be managed nonsurgically, which is preferable in these immunocompromised patients.