Related Experiment Video
Updated: Mar 1, 2026
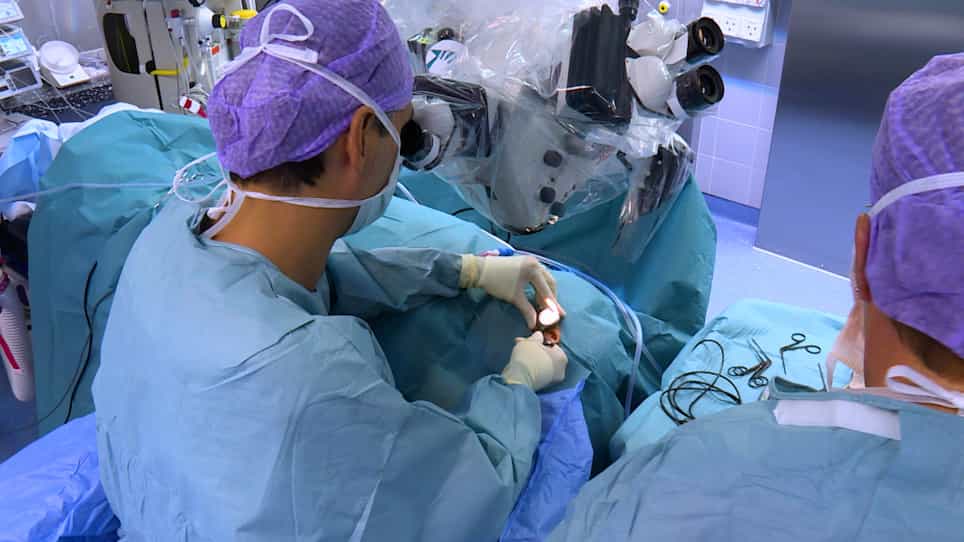
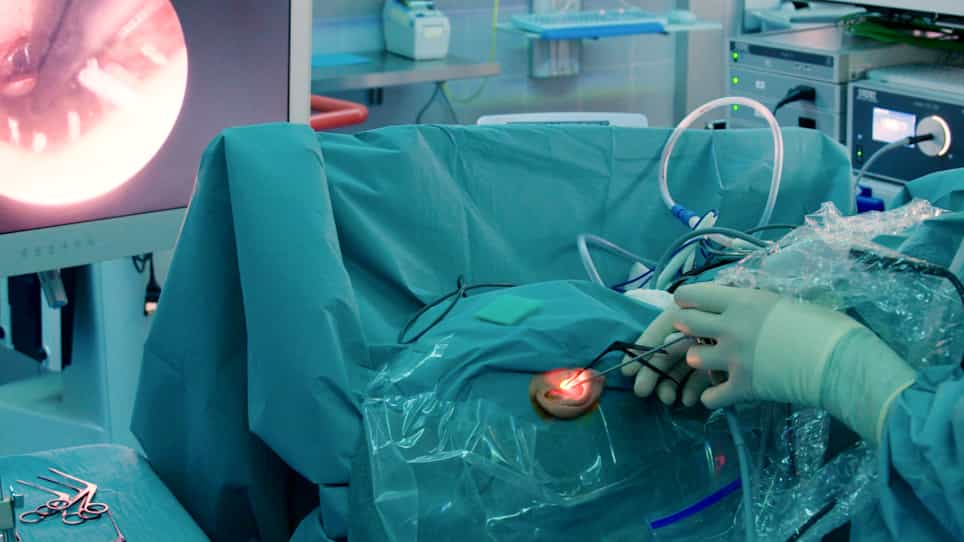
Robot-Assisted Transcanal Endoscopic Ear Surgery for Congenital Cholesteatoma
Published on: December 15, 2023
Endoscopic transcanal approach to the middle ear for management of pediatric cholesteatoma
Saied Ghadersohi1, John M Carter2, Stephen R Hoff1,2
1Department of Otolaryngology-Head and Neck Surgery, Northwestern University Feinberg School of Medicine.

Insights
Endoscopic ear surgery (EES) is effective for pediatric cholesteatoma, offering excellent visualization and low recurrence rates. This study highlights its viability as a primary surgical tool in managing these complex middle ear conditions.
Area of Science:
- Otolaryngology
- Pediatric Surgery
- Medical Technology
Background:
- Pediatric cholesteatoma presents unique surgical challenges.
- Endoscopic ear surgery (EES) offers potential advantages in visualization and access to middle ear structures.
Purpose of the Study:
- To evaluate the outcomes of endoscopic ear surgery (EES) for pediatric cholesteatoma.
- To assess the efficacy and recurrence rates of EES in a pediatric tertiary care setting.
Main Methods:
- A retrospective case series of 65 pediatric cholesteatoma cases (38 ears) was analyzed.
- Cases were subcategorized by cholesteatoma type (acquired vs. congenital) and EES approach.
- Surgical findings, outcomes, recurrence, and residual disease rates were evaluated.
Main Results:
- Overall recurrence was 13.2% and residual disease was 10.5% in 65 cases followed for an average of 2.6 years.
- Transcanal endoscopic ear surgery (EES 3) showed the lowest rates of recurrent and residual disease.
- Surgical time was longer for acquired cholesteatoma (226 minutes) compared to congenital (154 minutes).
Conclusions:
- Endoscopes are a viable tool for pediatric cholesteatoma resection.
- EES provides excellent visualization of the middle ear and its recesses.
- The study supports the use of EES as a primary surgical modality for pediatric cholesteatoma.
Objectives:
To describe outcomes for endoscopic ear surgery (EES) for pediatric cholesteatoma at a tertiary pediatric hospital.
Methods:
Retrospective case series of 65 pediatric cholesteatoma cases in 38 ears. Subgrouping based on cholesteatoma type and EES type. Surgical findings, outcomes, and demographic data were evaluated.
Results:
Endoscopes were used in 65 pediatric cholesteatoma cases in 38 primary ears (34 patients), followed for an average of 2.6 years (9 months to 4.6 years). The endoscope was used as the primary visualization tool in 31 (81.6%) ears (EES 2 or 3), and as an adjunct to the microscope in seven ears (EES 1). Twenty-two (57.9%) ears and 35 (53.4%) cases were transcanal endoscopic ear surgery (EES 3 or TEES). Overall, there was recurrence in five (13.2%) ears and residual in four (10.5%) ears. Cholesteatoma was acquired in 27 ears, with average age 10.9 years; and congenital in 11 ears, with average age 3.8 years. Surgical time was longer for acquired cases (226 vs. 154 minutes). Hearing outcomes were comparable for both cholesteatoma types. Residual disease was seen in three (11.1%) acquired ears and one (9.1%) congenital ear. Overall, the lowest rates of recurrent and residual disease were seen in EES 3 cases, and relatively low rates in EES 2 and 3 ears, including four (12.9%) recurrences and two (6.5%) ears with residual disease.
Conclusion:
The endoscopes are a viable tool for resection of pediatric cholesteatoma and provide excellent visualization of the middle ear and associated recesses.
Level Of Evidence:
4. Laryngoscope, 127:2653-2658, 2017.