Related Experiment Video
Updated: Mar 1, 2026
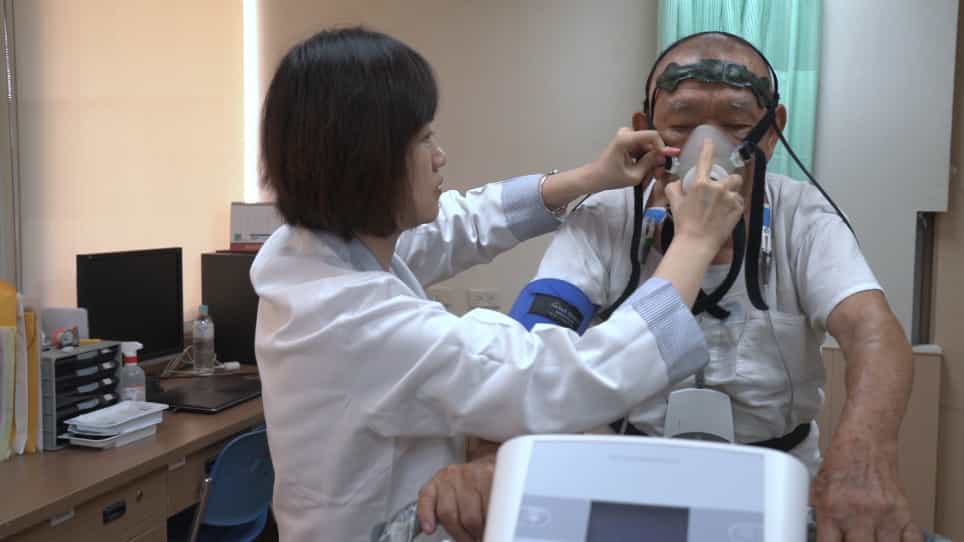

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Cardiopulmonary Exercise Testing in Aortic Stenosis
1le_tuyetvan@hotmail.com.

Abstract:
Patients with moderate to severe aortic stenosis (AVA <1.3 cm2) who were judged, by a referring cardiologist, as asymptomatic or equivocal symptomatic from the aortic stenosis were included in the study. Patients with left ventricular ejection fraction <50% were not included. Twenty-nine percent of the referred patients were judged asymptomatic and 71% equivocal symptomatic from their valve disease. The mean age was 72 years and 90% of the patients had an AVA-index <0.6 cm2/m2. By clinical evaluation in the outpatient clinic, 48% were judged as having functional limitation corresponding to NYHA≥II. The study participants had cardiopulmonary exercise testing (CPX) at inclusion, and, if relevant, pre- and nine months post-aortic valve replacement (AVR). CPX was feasible in 130 of 131 study participants recruited across 19 months. The coefficient of variability by test-retest was 5.4% and 4.6% for peak oxygen consumption (pVO2) and peak oxygen pulse (pO2pulse= pVO2/peak heart rate), respectively. The stroke volume generally increased with exercise, also in those with peak flow velocity across the aortic valve (Vmax) >5 m/s, >4 m/s, and <4 m/s but with high valvuloarterial impedance (Zva >5.5 mm Hg/(mL·m2 )). This was found both when assessed by inert gas rebreathing and by the pO2pulse/hemoglobin index. Both resting and exercise stroke volume were lower for the latter group, with Vmax <4 m/s but high valvuloarterial impedance. A pVO2 <83% of the predicted, which corresponds to the lower 95% percentile found in the healthy sedentary population, was predicted independently by lower stroke volume during exercise, lower heart rate during exercise, lower FEV1, and by higher ventilation/carbon dioxide exhaustion rate (VE/VCO2), but not by the severity of the aortic stenosis as determined by echocardiography. According to the CPX results, the patients were prospectively grouped into 3 groups, as follows: 1) normal pVO2 (>83% of predicted) and pO2pulse (>95% of predicted); 2) subnormal pVO2 or pO2pulse that according to CPX could be explained by causes other than hemodynamic compromise; 3) subnormal pVO2 and pO2pulse. Groups 1 and 2 followed an initial conservative strategy, whereas Group 3 was referred for angiogram and Heart Team evaluation for AVR. The patients were followed for an average of 24 months and, in Groups 1 and 2, one patient (0.9%) suffered cardiac death and seven were hospitalized with heart failure (6.7%). The patient who died and another patient with heart failure had both previously, during the study, declined AVR. For Groups 1 and 2, the rate of the combined endpoint progression to cardiac death, hospitalization with heart failure, or AVR was 37.5%, which seems lower than what was reported in the literature by conventional assessment and strategy for younger asymptomatic patients with comparable echocardiographic severity of aortic stenosis. The endpoint progression to cardiac death, hospitalization with heart failure, or AVR with improvement in pVO2 or in the Physical Component Score of the SF-36 health-related quality of life score was reached in 25.6% in Groups 1+2 and in 62.5% in Group 3 (p=0.003). A decreased pO2pulse, which expresses stroke volume at peak exercise, predicted this endpoint. In 73 operated patients without left ventricular dysfunction and no coronary stenosis, including 37 patients from the above-mentioned study, a CPX 9 months post-AVR showed that the pVO2, on average, was less than that predicted (mean 89% of the predicted ) and 35% of the patients had a subnormal pVO2 (<83% of that predicted). A preoperative mean gradient <40 mm Hg across the aortic valve, the presence of atrial fibrillation, and a permanent pacemaker post-AVR all predicted a post-AVR pVO2 <83% of that predicted. For the 37 patients with a pre-AVR CPX, a postoperative decrease >10% in the absolute pVO2 was noted in 30% and an increase >10% in 24% of patients. A decrease >10% in pVO2 was predicted by preoperative mean gradient <40 mm Hg and an increase in pVO2 was predicted by preoperative AVAI <0.4 cm2/m2 and preoperative pO2pulse
Conclusions:
In this group of patients, where clinical assessment is difficult and conventional exercise testing is regarded as less useful, CPX showed high feasibility and reproducibility. CPX therefore has potential as a useful tool for serial monitoring. In general, the stroke volume increased during exercise, including in patients with severe aortic stenosis or decreased resting stroke volume. CPX gives information on hemodynamics and the physiologic components that determine decreased pVO2. CPX seems useful to identify 1) patients with a low risk of cardiac death and low risk of progression to symptoms from the aortic stenosis, and 2) patients with hemodynamic compromise who improve in functional capacity after AVR. Patients with a preoperative mean gradient <40 mm Hg across the aortic valve, with the presence of atrial fibrillation or who have a permanent pacemaker, postoperatively seem to benefit less from AVR, whereas the benefit seems larger in those with more severe aortic stenosis and a decreased pO2pulse. These findings may be of importance for decisions and information of patients before AVR.
More Related Videos
 07:10
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Related Concept Videos
 01:26
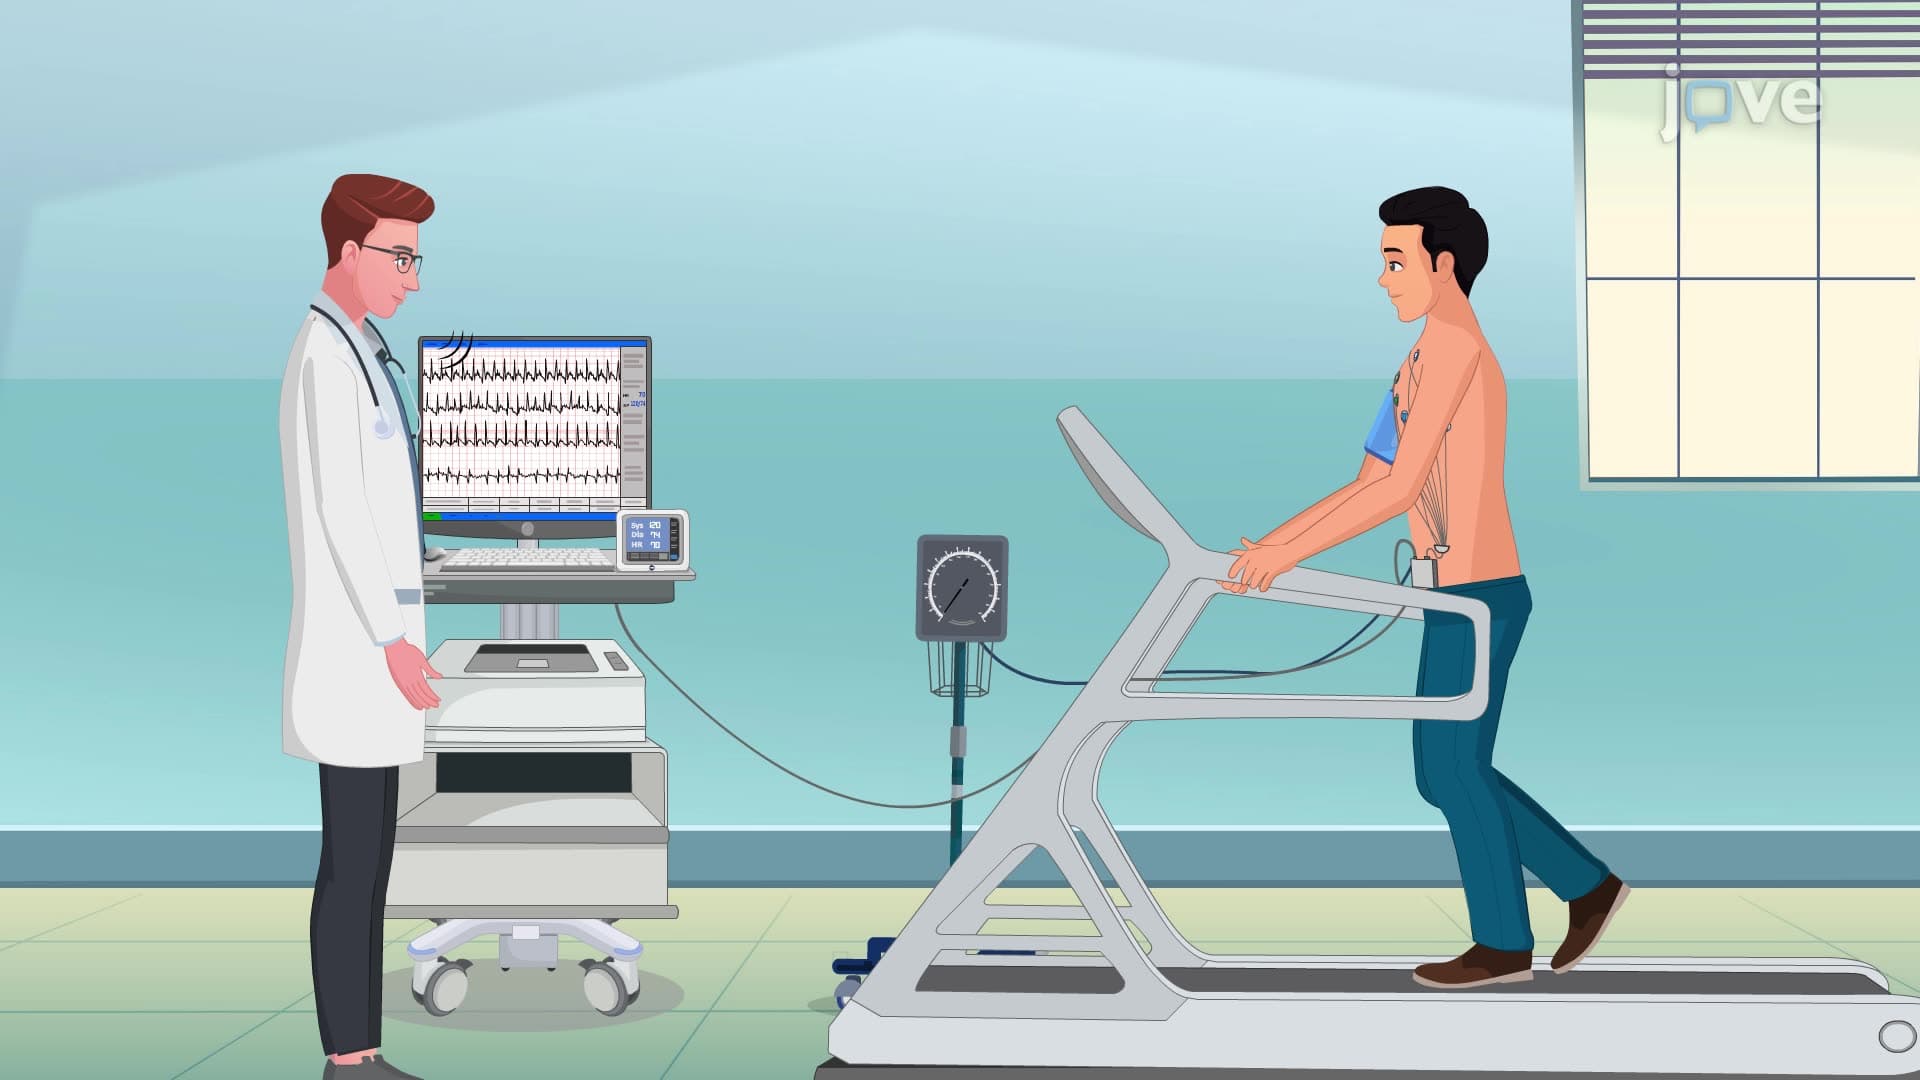
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:25
Aortic Regurgitation III: Medical Management
 01:17
Aortic Regurgitation IV: Nursing Management
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...