Reverse Total Shoulder Arthroplasty: Salvage Procedure for Failed Prior Arthroplasty
Related Experiment Video
Updated: Mar 1, 2026
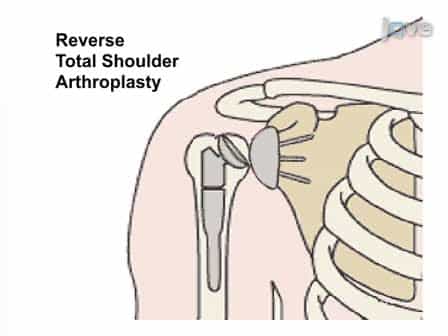
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Seong Hwan Jo1, Jung Youn Kim2, Nam Su Cho1
1Department of Orthopaedic Surgery, Kyung Hee University College of Medicine, Seoul, Korea.

Background:
To evaluate the clinical outcome of revision of primary shoulder replacement by using reverse total shoulder arthroplasty (RTSA).
Methods:
Seven patients underwent revision RTSA with a mean follow-up of 22.1 months (range, 12 to 54 months). Their mean age at the time of operation was 75.5 years (range, 70 to 80 years). Assessments were performed on the preoperative and postoperative visual analogue scale (VAS) score, muscle strength, range of motion, University of California at Los Angeles (UCLA) score, Constant score, subjective satisfaction and the anteroposterior and axillary views of the glenohumeral joint. The primary operation was hemiarthroplasty in 5 patients, total shoulder replacement in 1 patient, and reverse shoulder arthroplasty in 1 patient. The cause of revision surgery was infection in 2 patients, humeral stem loosening in 2 patients, glenoid arthropathy in 2 patients, and glenoid loosening in 1 patient. The mean duration from primary operation to revision surgery was 52 months (range, 27 to 120 months).
Results:
The VAS score for pain during motion was improved from 7.3 preoperatively to 2.1 postoperatively (p = 0.03). There were increases in the mean active forward flexion (from 62.1° to 92.8°), abduction (from 70° to 87.1°), external rotation (from 44.2° to 47.4°), and internal rotation (from L5 to L4; p > 0.05) postoperatively. Performance in activities of daily living improved (p > 0.05), except for lifting 10 lb above the shoulder (from 1.2 to 1.1; p = 0.434). Overall, 5 of 7 patients were satisfied with the results of revision surgery. The mean Constant score improved from 44.8 preoperatively to 57.1 postoperatively (p = 0.018). The mean UCLA score improved from 12.8 preoperatively to 22.8 postoperatively (p = 0.027). In the postoperative radiological evaluation, no radiolucency was observed around the base plate or humeral stem.
Conclusions:
Pain could be reduced after revision RTSA, but improvements in range of motion and function were difficult to achieve. We think that the patients' satisfaction was relatively high despite the low function score due to the preoperative severe pain and marked limitation of range of motion.
More Related Videos
 04:27
Anterior Capsular Reconstruction with Human Dermal Allograft for Irreparable Subscapularis Tears
Published on: May 9, 2025
 07:22
Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025