Related Experiment Video
Updated: Mar 1, 2026
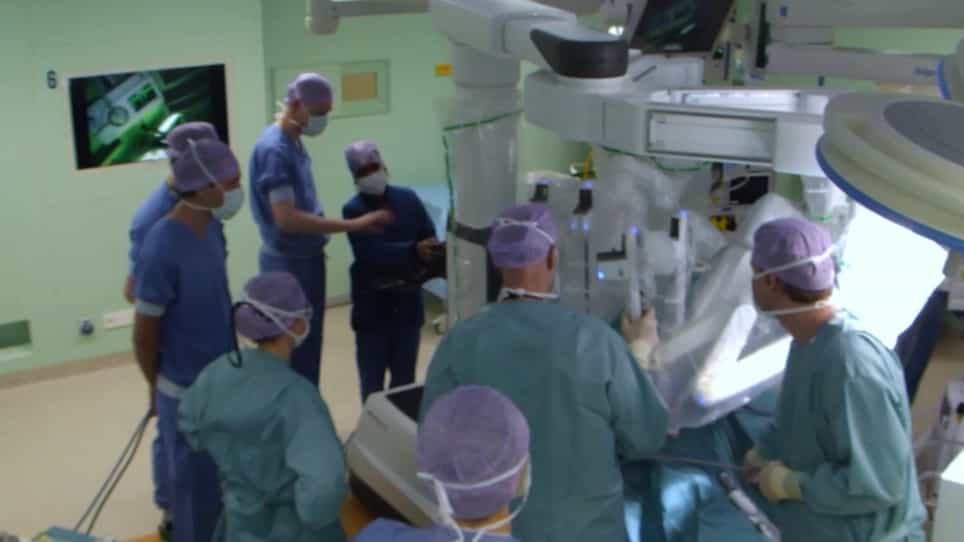
Robotic Enucleation of an Intra-Pancreatic Insulinoma in the Pancreatic Head
Published on: January 3, 2020
Recurrent insulinoma in a 10-year-old boy with Down's syndrome
Noman Ahmad1, Abdulmonem Mohammed Almutawa1, Mohamed Ziyad Abubacker1
1King Faisal Specialist Hospital and Research Centre, Pediatrics, Jeddah, SASaudi Arabia.

Insights
Insulinoma, a rare pancreatic tumor, can be challenging to diagnose in children, even those with Down syndrome. Surgical resection offers a cure, but recurrence is possible, necessitating close follow-up.
Area of Science:
- Pediatric Endocrinology
- Surgical Oncology
- Neuroendocrinology
Background:
- Insulinoma is a rare pancreatic neuroendocrine tumor with low incidence, particularly in children.
- Diagnosis can be delayed due to non-specific symptoms and rarity, even in pediatric cases.
- Limited literature exists on pediatric insulinoma, especially in association with genetic syndromes like Down syndrome.
Purpose of the Study:
- To present a case of recurrent insulinoma in a 10-year-old boy with Down syndrome.
- To highlight diagnostic challenges and management strategies for pediatric insulinoma.
- To emphasize the importance of considering insulinoma in the differential diagnosis of pediatric hypoglycemia.
Main Methods:
- Case report detailing diagnostic workup including biochemical tests (insulin, C-peptide, ketones) and imaging (MRI, octreotide scan, PET scan).
- Description of medical management (diazoxide, octreotide) and surgical interventions (laparoscopic enucleation, open laparotomy).
- Pathological examination to confirm tumor type and benign nature.
Main Results:
- The patient experienced recurrent hypoglycemia, initially misdiagnosed, leading to cushingoid features.
- Tumor localization was achieved with MRI and octreotide scan; recurrence confirmed by MRI and PET scan.
- Surgical resection resulted in complete symptom resolution, both initially and after recurrence.
Conclusions:
- Insulinoma should be considered in pediatric hypoglycemia, particularly with absent ketones and neurological symptoms.
- Advanced imaging (MRI, PET) is crucial for accurate localization of pancreatic beta islet cell tumors.
- Surgical resection is the definitive curative treatment, though lifelong monitoring for recurrence is essential.
Abstract:
An insulinoma is a rare tumour with an incidence of four cases per million per year in adults. The incidence in children is not established. There is limited literature available in children with insulinoma, and only one case is reported in association with Down's syndrome in adults. Insulinoma diagnosis is frequently missed in adults as well as in children. The Whipple triad is the most striking feature although it has limited application in young children. Hypoglycaemia with elevated insulin, C-peptide and absent ketones is highly suggestive of hyperinsulinism. We present a case of 10-year-old boy with Down's syndrome with recurrent insulinoma. He was initially misdiagnosed as having an adrenal insufficiency and developed cushingoid features and obesity secondary to hydrocortisone treatment and excessive sugar intake. The tumour was successfully localised in the head of the pancreas with an MRI and octreotide scan on first presentation. Medical treatment with diazoxide and octreotide could not achieve normal blood glucose levels. The insulinoma was laparoscopically enucleated and pathological examination confirmed a neuroendocrine tumour. Subsequently, he had complete resolution of symptoms. He had a recurrence after 2 years with frequent episodes of hypoglycaemia. The biochemical workup was suggestive of hyperinsulinism. MRI and PET scan confirmed the recurrence at the same site (head of the pancreas). He had an open laparotomy for insulinoma resection. The pathology was consistent with benign insulinoma, and subsequently, he had complete resolution of symptoms.
Learning Points:
Insulinoma is a very rare tumour in children; it should be considered in the differential diagnosis of hypoglycaemia with absent ketones.Refractory neurological symptoms like seizure, migraine, mood changes and regression of learning abilities should suggest evaluation for hypoglycaemia.MRI with contrast and PET scan would localise the majority of pancreatic beta islet cell lesions.Medical treatment with diazoxide, octreotide and the addition of corn starch in feeds is not curative but can be supportive to maintain normoglycemia until the surgical resection.Surgical resection is the only curative treatment. The surgical procedure of choice (laparoscopic/open laparotomy) depends on local expertise, preoperative localisation, tumour size and number.Surgical treatment results in complete resolution of symptoms, but all cases should be closely followed up to monitor for recurrence. The recurrence rate is four times higher in MEN1 cases.

Related Concept Videos
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:05
Insulin Secretory Vesicles
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are...
 01:15
Hypoglycemia and Glucagon