Comparison of cardiac output estimates by bioreactance and inert gas rebreathing methods during cardiopulmonary exercise testing
Related Experiment Video
Updated: Mar 1, 2026

Author Spotlight: Assessment of Cardiac Output Calculation by Thermodilution in Pigs for Effective Perfusion Flow During EVLP
Published on: June 28, 2024
Nduka C Okwose1, Shakir Chowdhury1, David Houghton1
1Institute of Cellular Medicine, Medical School, Newcastle University, Newcastle Upon Tyne, UK.

Purpose:
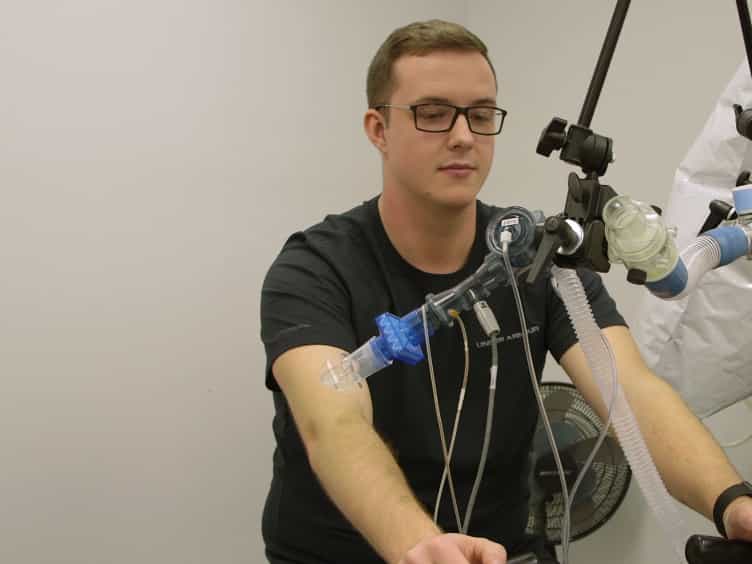
This study assessed the agreement between cardiac output estimated by inert gas rebreathing and bioreactance methods at rest and during exercise.
Methods:
Haemodynamic measurements were assessed in 20 healthy individuals (11 females, nine males; aged 32 ± 10 years) using inert gas rebreathing and bioreactance methods. Gas exchange and haemodynamic data were measured simultaneously under rest and different stages (i.e. 30, 60, 90, 120, 150 and 180 W) of progressive graded cardiopulmonary exercise stress testing using a bicycle ergometer.
Results:
At rest, bioreactance produced significantly higher cardiac output values than inert gas rebreathing (7·8 ± 1·4 versus 6·5 ± 1·7 l min-1 , P = 0·01). At low-to-moderate exercise intensities (i.e. 30-90 W), bioreactance produced significantly higher cardiac outputs compared with rebreathing method (P<0·05). At workloads of 120 W and above, there was no significant difference in cardiac outputs between the two methods (P = 0·10). There was a strong relationship between the two methods (r = 0·82, P = 0·01). Bland-Altman analysis including rest and exercise data showed that inert gas rebreathing reported 1·95 l min-1 lower cardiac output than bioreactance, with lower and upper limits of agreement of -3·1-7·07 l min-1 . Analysis of peak exercise data showed a mean difference of 0·4 l min-1 (lower and upper limits of agreement of -4·9-5·7 l min-1 ) between both devices.
Conclusion:
Bioreactance and inert gas rebreathing methods show acceptable levels of agreement for estimating cardiac output at higher levels of metabolic demand. However, they cannot be used interchangeably due to strong disparity in results at rest and low-to-moderate exercise intensity.
More Related Videos
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Related Concept Videos
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
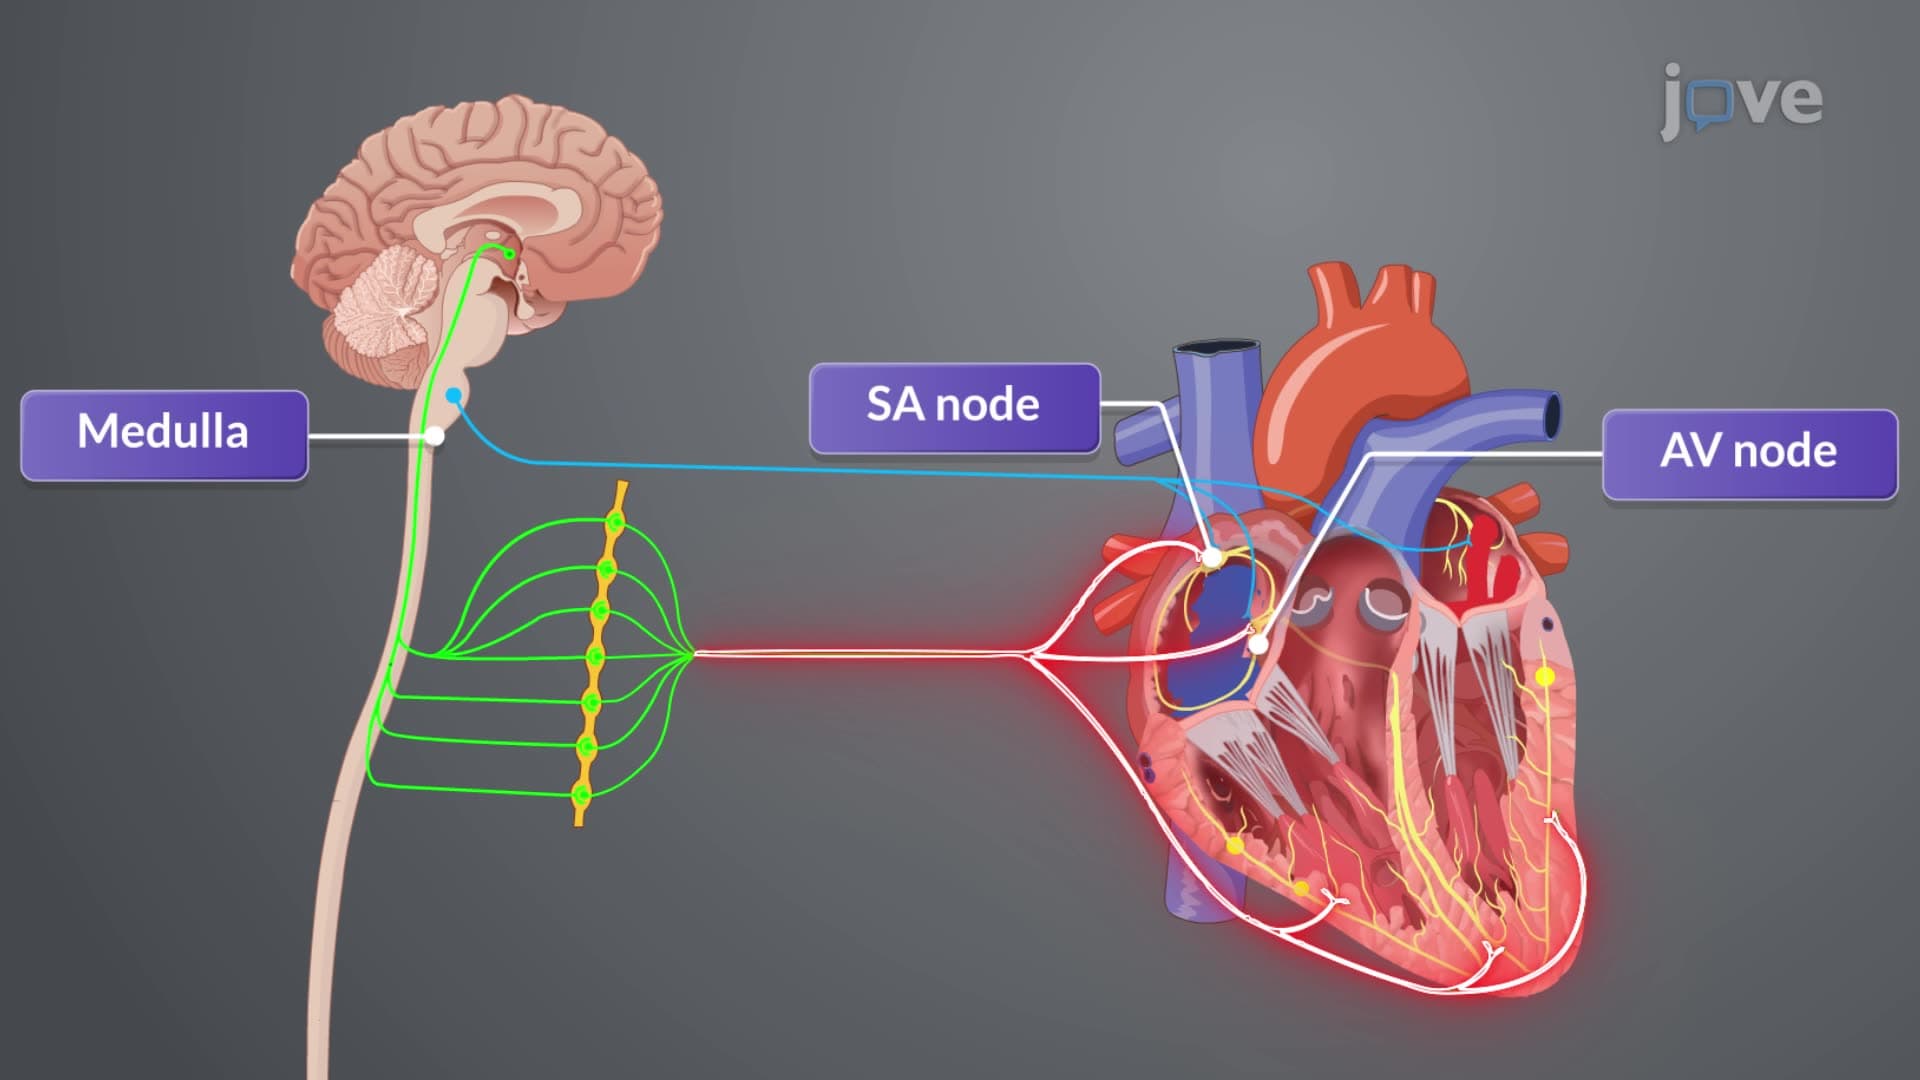
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: