Related Experiment Video
Updated: Mar 1, 2026


Antibiotic Efficacy Testing in an Ex vivo Model of Pseudomonas aeruginosa and Staphylococcus aureus Biofilms in the Cystic Fibrosis Lung
Published on: January 22, 2021
Pharmacokinetics of nebulized colistin methanesulfonate in critically ill patients
Matthieu Boisson1,2,3, Nicolas Grégoire1,2, Marielle Cormier3
1Inserm U1070, Pôle Biologie Santé, 1 rue Georges Bonnet, 86000 Poitiers, France.

Objectives:
Optimal dosing for nebulized colistin methanesulfonate (CMS), the prodrug of colistin, is unknown. We describe the pulmonary and systemic pharmacokinetics of CMS and colistin following nebulization of 0.5 million IU (MIU) of CMS in ventilated patients.
Methods:
Twelve critically ill patients received 0.5 MIU of CMS administered every 8 h as 30 min nebulizations. Blood samples were collected immediately before and until 8 h after first nebulization; mini-bronchoalveolar lavage (mini-BAL) was performed at 1 and 5 h or 3 and 8 h (six patients each) post-dose. Pharmacokinetic analysis was performed for CMS and colistin plasma concentrations using a non-compartmental method. ClinicalTrials.gov: NCT01060891.
Results:
After nebulization, CMS concentrations in epithelial lining fluid (ELF) were much higher (100- to 1000-fold) than those in plasma. Concentrations of colistin in ELF should be considered with caution because when <6 mg/L in BAL, colistin bound to mini-BAL devices. Nevertheless, CMS and colistin concentrations in ELF were much lower than expected from previous results with a 2 MIU dose. From CMS plasma pharmacokinetics it was shown that CMS systemic bioavailability was only slightly decreased for the 0.5 MIU dose compared with 2 MIU.
Conclusions:
This study shows that CMS concentrations were much higher (100- to 1000-fold) in ELF than in plasma after a 0.5 MIU aerosol of CMS, but much lower (10-fold) than expected from previous results with a 2 MIU dose. Therefore, until new pharmacokinetic and pharmacodynamic assessments of the treatment of ventilator-associated pneumonia with nebulized CMS are performed, the 2 MIU dose should be preferred to the 0.5 MIU dose.
Insights
Nebulized colistin methanesulfonate (CMS) at 0.5 million IU resulted in higher concentrations in lung fluid than plasma, but lower than expected. The 2 million IU dose is preferred for treating ventilator-associated pneumonia.
Area of Science:
- Pharmacology
- Critical Care Medicine
- Infectious Diseases
Background:
- Optimal dosing for nebulized colistin methanesulfonate (CMS), the prodrug of colistin, remains undetermined.
- Ventilator-associated pneumonia (VAP) requires effective antibiotic strategies.
Purpose of the Study:
- To determine the pulmonary and systemic pharmacokinetics of CMS and colistin after nebulization of 0.5 million IU (MIU) in ventilated patients.
- To compare the pharmacokinetic profiles of CMS and colistin at a lower dose (0.5 MIU) versus a previously studied higher dose (2 MIU).
Main Methods:
- A pharmacokinetic study involving 12 critically ill, ventilated patients receiving nebulized CMS (0.5 MIU) every 8 hours.
- Collection of plasma and mini-bronchoalveolar lavage (mini-BAL) samples at various time points post-nebulization.
- Non-compartmental pharmacokinetic analysis of CMS and colistin plasma and epithelial lining fluid (ELF) concentrations.
Main Results:
- CMS concentrations in ELF were significantly higher (100- to 1000-fold) than in plasma.
- CMS and colistin concentrations in ELF were approximately 10-fold lower than anticipated based on previous studies using a 2 MIU dose.
- Systemic bioavailability of CMS was only slightly decreased at the 0.5 MIU dose compared to the 2 MIU dose.
Conclusions:
- Nebulized CMS at 0.5 MIU achieves high concentrations in the lungs but lower than expected levels compared to a 2 MIU dose.
- The 2 MIU dose of nebulized CMS is recommended over the 0.5 MIU dose for treating VAP until further pharmacokinetic and pharmacodynamic data are available.
More Related Videos


Related Concept Videos
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:20
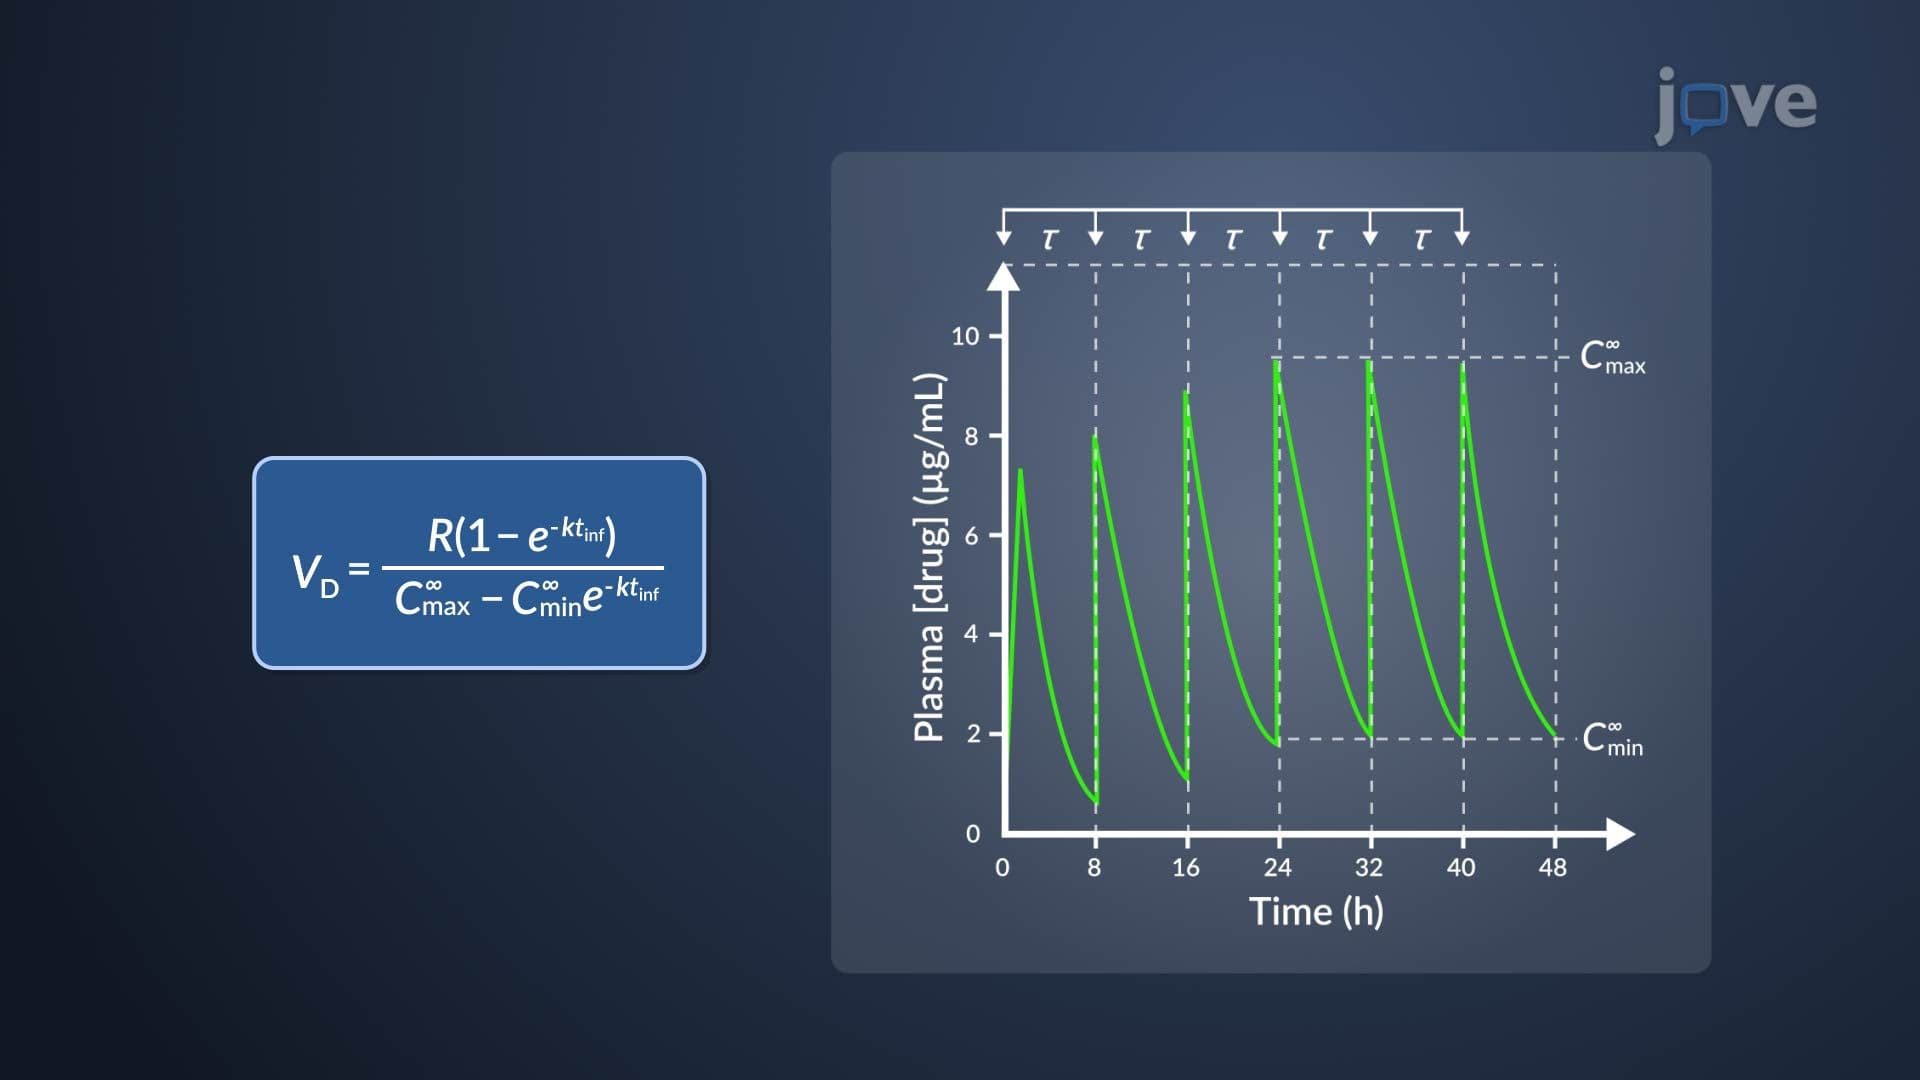
Estimation of k and VD of Aminoglycosides
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence