Related Experiment Video
Updated: Feb 28, 2026
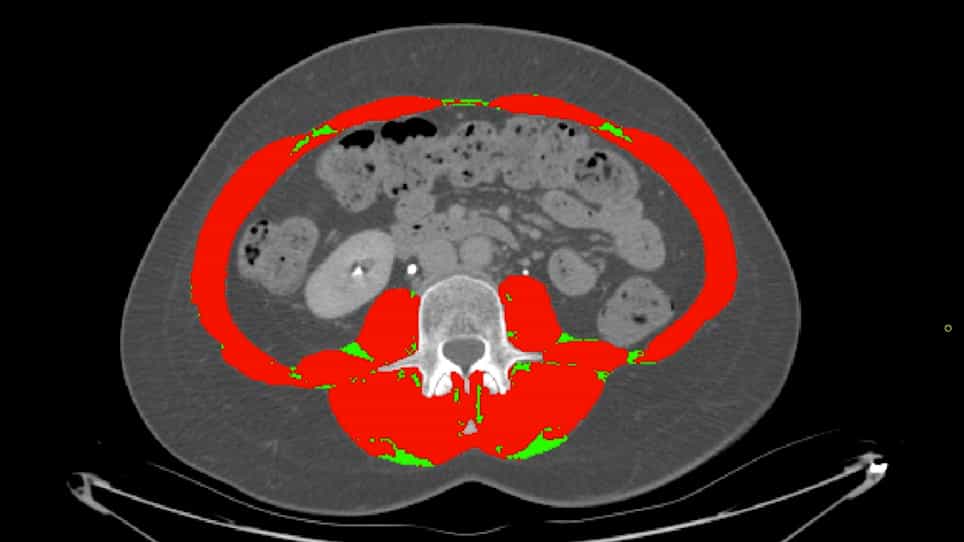
Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Severe Sarcopenia and Increased Fat Stores in Pediatric Patients With Liver, Kidney, or Intestine Failure
Richard S Mangus1, Weston J Bush, Christina Miller
1Department of Surgery, Indiana University School of Medicine, Indianapolis, IN.

Insights
Children with end-stage organ failure exhibit significant muscle loss (sarcopenia) and increased fat stores. This highlights an active physiological mechanism in these critically ill pediatric patients.
Area of Science:
- Pediatric critical care medicine
- Nutritional science
- Transplant medicine
Background:
- Malnutrition and wasting are known predictors of poor clinical outcomes in children with severe chronic illnesses.
- Objective quantification of malnutrition in pediatric end-stage organ failure (ESOF) populations remains understudied.
- Understanding body composition changes is crucial for managing these complex cases.
Purpose of the Study:
- To compare muscle and fat stores in children with end-stage liver, kidney, or intestine failure against healthy controls.
- To quantify the disparities in body composition in pediatric ESOF.
Main Methods:
- Retrospective analysis of pediatric patients (<19 years) with end-stage liver, kidney, or intestine failure undergoing pretransplant computed tomography (CT) imaging.
- Inclusion of age- and sex-matched healthy controls from a trauma database.
- Assessment of nutritional status via scaled scoring of core muscle mass, visceral fat, and subcutaneous fat stores.
Main Results:
- Analysis included 81 pediatric patients (35 liver, 20 kidney, 26 intestine failure).
- Liver failure patients showed a 23% muscle mass reduction, 69% visceral fat increase, and 29% subcutaneous fat increase.
- Kidney failure patients exhibited a 19% muscle mass reduction and 258% subcutaneous fat increase.
- Intestine failure patients had a 24% muscle mass reduction, 30% visceral fat increase, and 46% subcutaneous fat increase.
Conclusions:
- Pediatric end-stage organ failure is characterized by significant sarcopenia (muscle loss) and increased fat deposition.
- These findings suggest an active physiological process where fat is stored concurrently with muscle mass depletion.
- Potential mechanisms include protein loss from catabolism, decreased synthesis (liver), wasting (kidney), or malabsorption (intestine).
Objectives:
Malnutrition and wasting predict clinical outcomes in children with severe chronic illness. Objectively calculated malnutrition in children with end-stage organ failure has not been well studied. This analysis compares children with kidney, liver or intestine failure to healthy controls to quantitate the disparity in muscle and fat stores.
Methods:
Children younger than 19 years with end-stage liver, kidney, or intestine failure and with pretransplant computed tomography (CT) imaging were selected from the transplant database. Age- and sex-matched healthy controls were selected from the trauma database. Measures of nutrition status included a scaled scoring of core muscle mass, and visceral and subcutaneous fat stores. Analysis was conducted using the pooled and individually matched subject-control differences.
Results:
There were 81 subjects included in the final analysis (liver [n = 35], kidney [n = 20], and intestine [n = 26]). Children with end-stage liver disease had a 23% reduction in muscle mass, a 69% increase in visceral fat, and a 29% increase in subcutaneous fat. End-stage renal disease patients had a 19% reduction in muscle mass and a 258% increase in subcutaneous fat. Intestine failure patients had a 24% reduction in muscle mass, a 30% increase in visceral fat, and a 46% increase in subcutaneous fat.
Conclusions:
These results demonstrate significant sarcopenia and increased fat stores in end-stage organ failure patients, which supports the idea of an active physiologic mechanism to store fat while losing muscle mass. Sarcopenia may be related to total protein loss from a catabolic state, or from decreased synthesis (liver), wasting (kidney), or malabsorption (intestine).
Related Concept Videos
 01:21
Overview of Protein Metabolism
Amino acids play various roles in the body once they are absorbed into cells. They are restructured...
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion