Related Experiment Video
Updated: Feb 27, 2026


Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Effects of Intensive BP Control in CKD
Alfred K Cheung1,2, Mahboob Rahman3,4, David M Reboussin5
1Division of Nephrology and Hypertension and alfred.cheung@hsc.utah.edu.

Insights
Lowering systolic blood pressure (BP) to <120 mm Hg in patients with chronic kidney disease (CKD) and hypertension reduced cardiovascular events and death. This intensive BP target did not harm kidney function or show differing effects based on CKD status.
Area of Science:
- Nephrology
- Cardiology
- Clinical Trials
Background:
- The optimal systolic blood pressure (BP) target for patients with chronic kidney disease (CKD) and hypertension is not well-established.
- Subgroup analyses from major trials are crucial for understanding treatment effects in specific populations like those with CKD.
Purpose of the Study:
- To analyze the outcomes of targeting a systolic BP of <120 mm Hg versus <140 mm Hg in patients with CKD and hypertension.
- To assess the impact of intensive BP lowering on cardiovascular events, all-cause mortality, and kidney outcomes in this population.
Main Methods:
- Prespecified subgroup analyses from the Systolic Blood Pressure Intervention Trial (SPRINT) involving participants with baseline CKD.
- Random assignment to either an intensive BP target (<120 mm Hg) or a standard BP target (<140 mm Hg).
- Follow-up for major cardiovascular outcomes, all-cause death, and kidney-specific outcomes, including estimated glomerular filtration rate (eGFR) and end-stage renal disease (ESRD).
Main Results:
- The intensive BP target group showed a reduced rate of the primary composite cardiovascular outcome (HR, 0.81; 95% CI, 0.63 to 1.05) and all-cause death (HR, 0.72; 95% CI, 0.53 to 0.99) compared to the standard target group.
- No significant interaction was observed between CKD status and treatment effect for cardiovascular outcomes, suggesting similar benefits across groups.
- The intensive group experienced a slightly faster decline in eGFR after 6 months, but the main kidney outcome (composite of ≥50% eGFR decrease or ESRD) did not differ significantly between groups (HR, 0.90; 95% CI, 0.44 to 1.83).
Conclusions:
- Targeting a systolic BP of <120 mm Hg in patients with CKD and hypertension (without diabetes) effectively reduced major cardiovascular events and all-cause mortality.
- This intensive BP management strategy did not demonstrate a deleterious effect on kidney outcomes and showed consistent effects regardless of CKD status.
- While some adverse events were more frequent in the intensive group, the overall safety profile was comparable, supporting the benefit of intensive BP control in this cohort.
Abstract:
The appropriate target for BP in patients with CKD and hypertension remains uncertain. We report prespecified subgroup analyses of outcomes in participants with baseline CKD in the Systolic Blood Pressure Intervention Trial. We randomly assigned participants to a systolic BP target of <120 mm Hg (intensive group; n=1330) or <140 mm Hg (standard group; n=1316). After a median follow-up of 3.3 years, the primary composite cardiovascular outcome occurred in 112 intensive group and 131 standard group CKD participants (hazard ratio [HR], 0.81; 95% confidence interval [95% CI], 0.63 to 1.05). The intensive group also had a lower rate of all-cause death (HR, 0.72; 95% CI, 0.53 to 0.99). Treatment effects did not differ between participants with and without CKD (P values for interactions ≥0.30). The prespecified main kidney outcome, defined as the composite of ≥50% decrease in eGFR from baseline or ESRD, occurred in 15 intensive group and 16 standard group participants (HR, 0.90; 95% CI, 0.44 to 1.83). After the initial 6 months, the intensive group had a slightly higher rate of change in eGFR (-0.47 versus -0.32 ml/min per 1.73 m2 per year; P<0.03). The overall rate of serious adverse events did not differ between treatment groups, although some specific adverse events occurred more often in the intensive group. Thus, among patients with CKD and hypertension without diabetes, targeting an SBP<120 mm Hg compared with <140 mm Hg reduced rates of major cardiovascular events and all-cause death without evidence of effect modifications by CKD or deleterious effect on the main kidney outcome.


Related Concept Videos
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:25
Chronic Kidney Disease I: Introduction
 01:18
Hypertension and Regulation of Blood Pressure
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:30
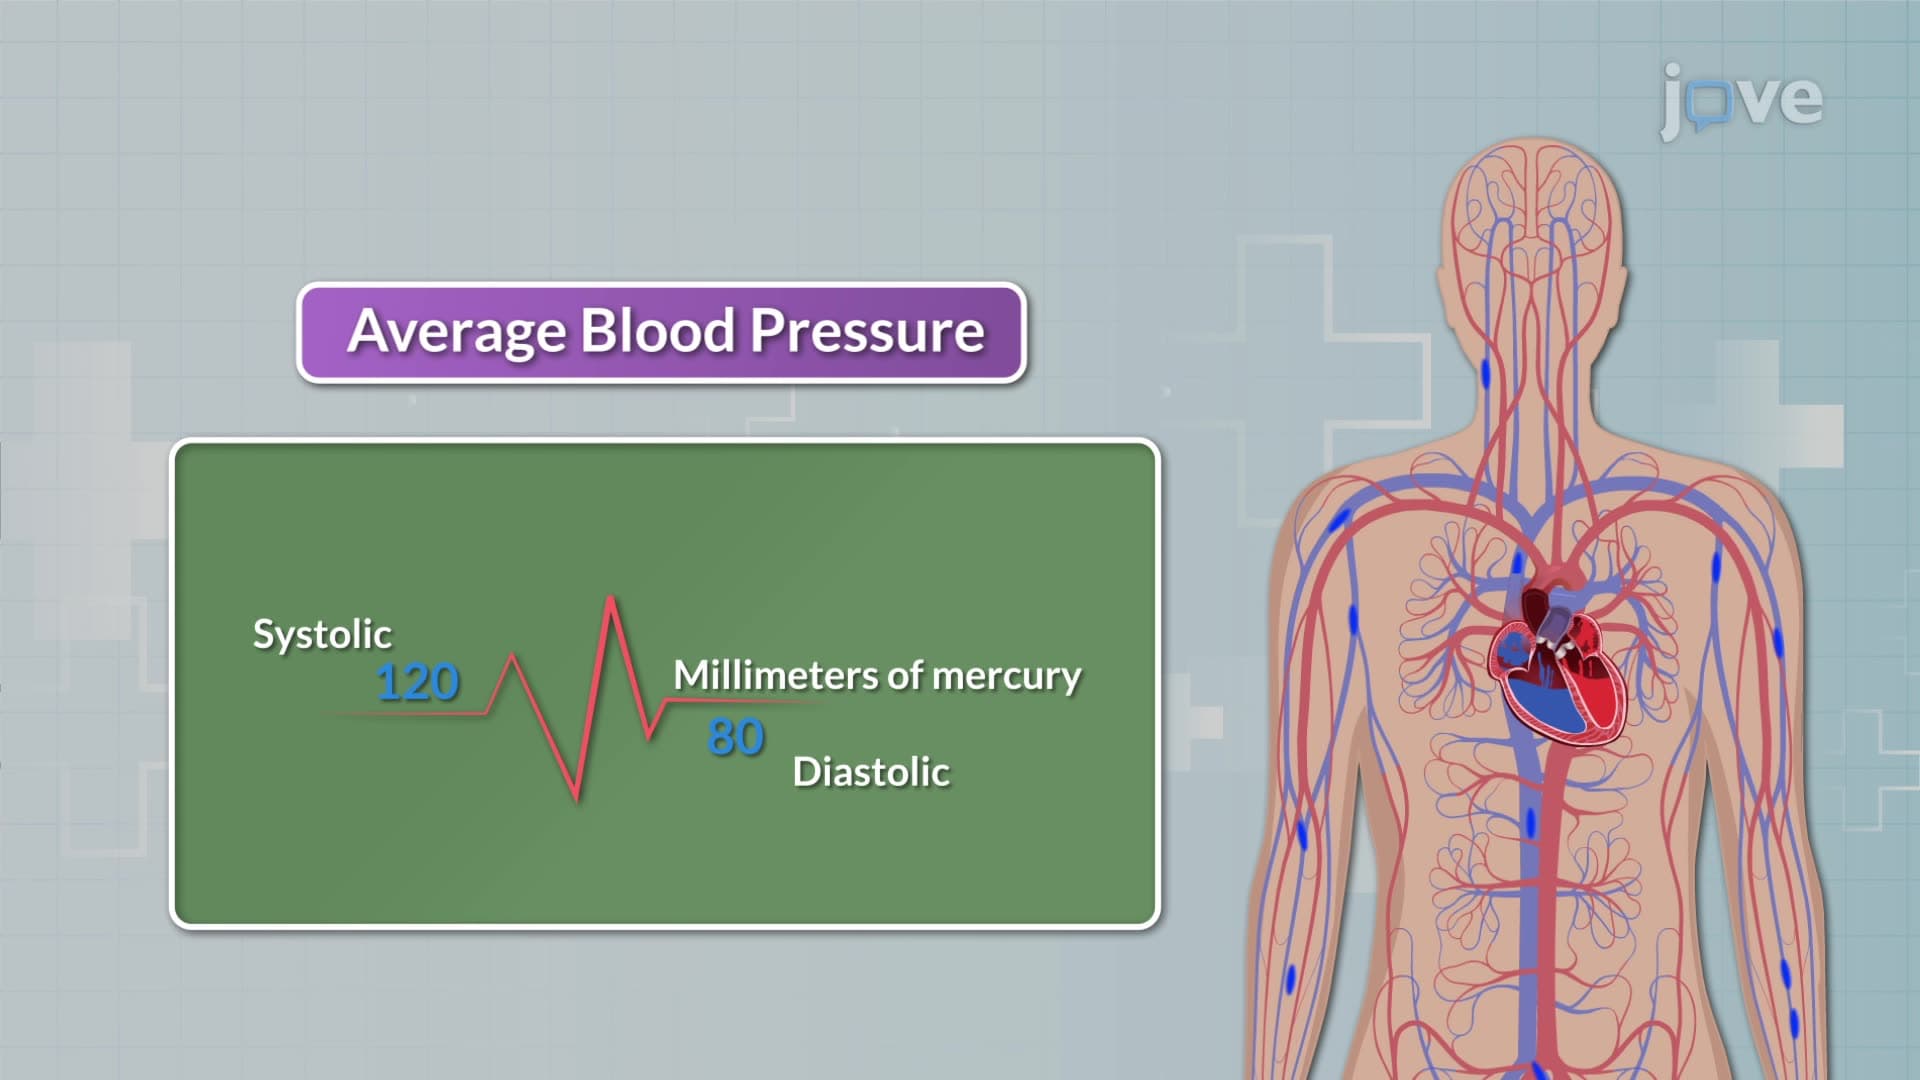
Blood Pressure
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors