Related Experiment Video
Updated: Feb 27, 2026
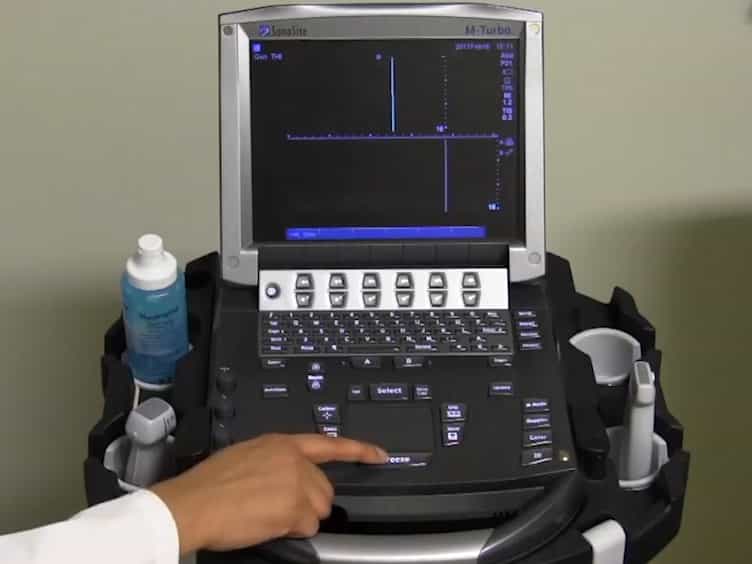
Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Pharmacodynamics of intravenous frusemide bolus in critically ill patients
Agnes Huang1, Nora Luethi2, Johan Mårtensson2
1Department of Intensive Care, Austin Hospital, Melbourne, VIC, Australia. luca.cioccari@gmail.com.

Objective:
To assess the physiological, biochemical and haemodynamic response to a single intravenous (IV) dose of frusemide in critically patients.
Design, Setting And Patients:
A prospective observational study of 21 critically ill patients in a tertiary intensive care unit in Australia.
Interventions:
We collected information on urine output (UO), fluid balance, serum and urinary electrolyte levels, serum biochemical levels and haemodynamics. We compared data from the 6-hour period before administration of a single IV bolus of frusemide 40 mg with data from the 6-hour period after administration.
Results:
We studied 21 patients (12 of whom were women) with a median age of 73 years (interquartile range [IQR], 64-80 years). The IV bolus induced a > 1000 mL increase in UO in six patients (28.6%); a 500-1000 mL increase in six patients (28.6%) and a < 500 mL increase in nine patients (42.8%). The median difference in UO before and after frusemide was 590 mL (IQR, 290-1111 mL). The 6-hour fluid balance became negative in 15 patients (71.4%) and positive in six patients (28.6%), with a median change of -595 mL (IQR, -880 to 98 mL). Frusemide significantly increased urinary sodium, potassium and chloride losses and decreased blood chloride levels. There were no detectable changes in haemodynamics. On linear regression analysis, sodium excretion and UO correlated with higher mean arterial pressure (MAP) and age, and with lower albumin and creatinine levels.
Conclusions:
In a cohort of critically ill patients without chronic renal impairment, frusemide increased UO and urinary sodium, potassium and chloride losses, and induced hypochloraemia and metabolic alkalosis. However, its diuretic effects were extremely variable and were modified by age, MAP and creatinine and albumin levels.

Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 00:59
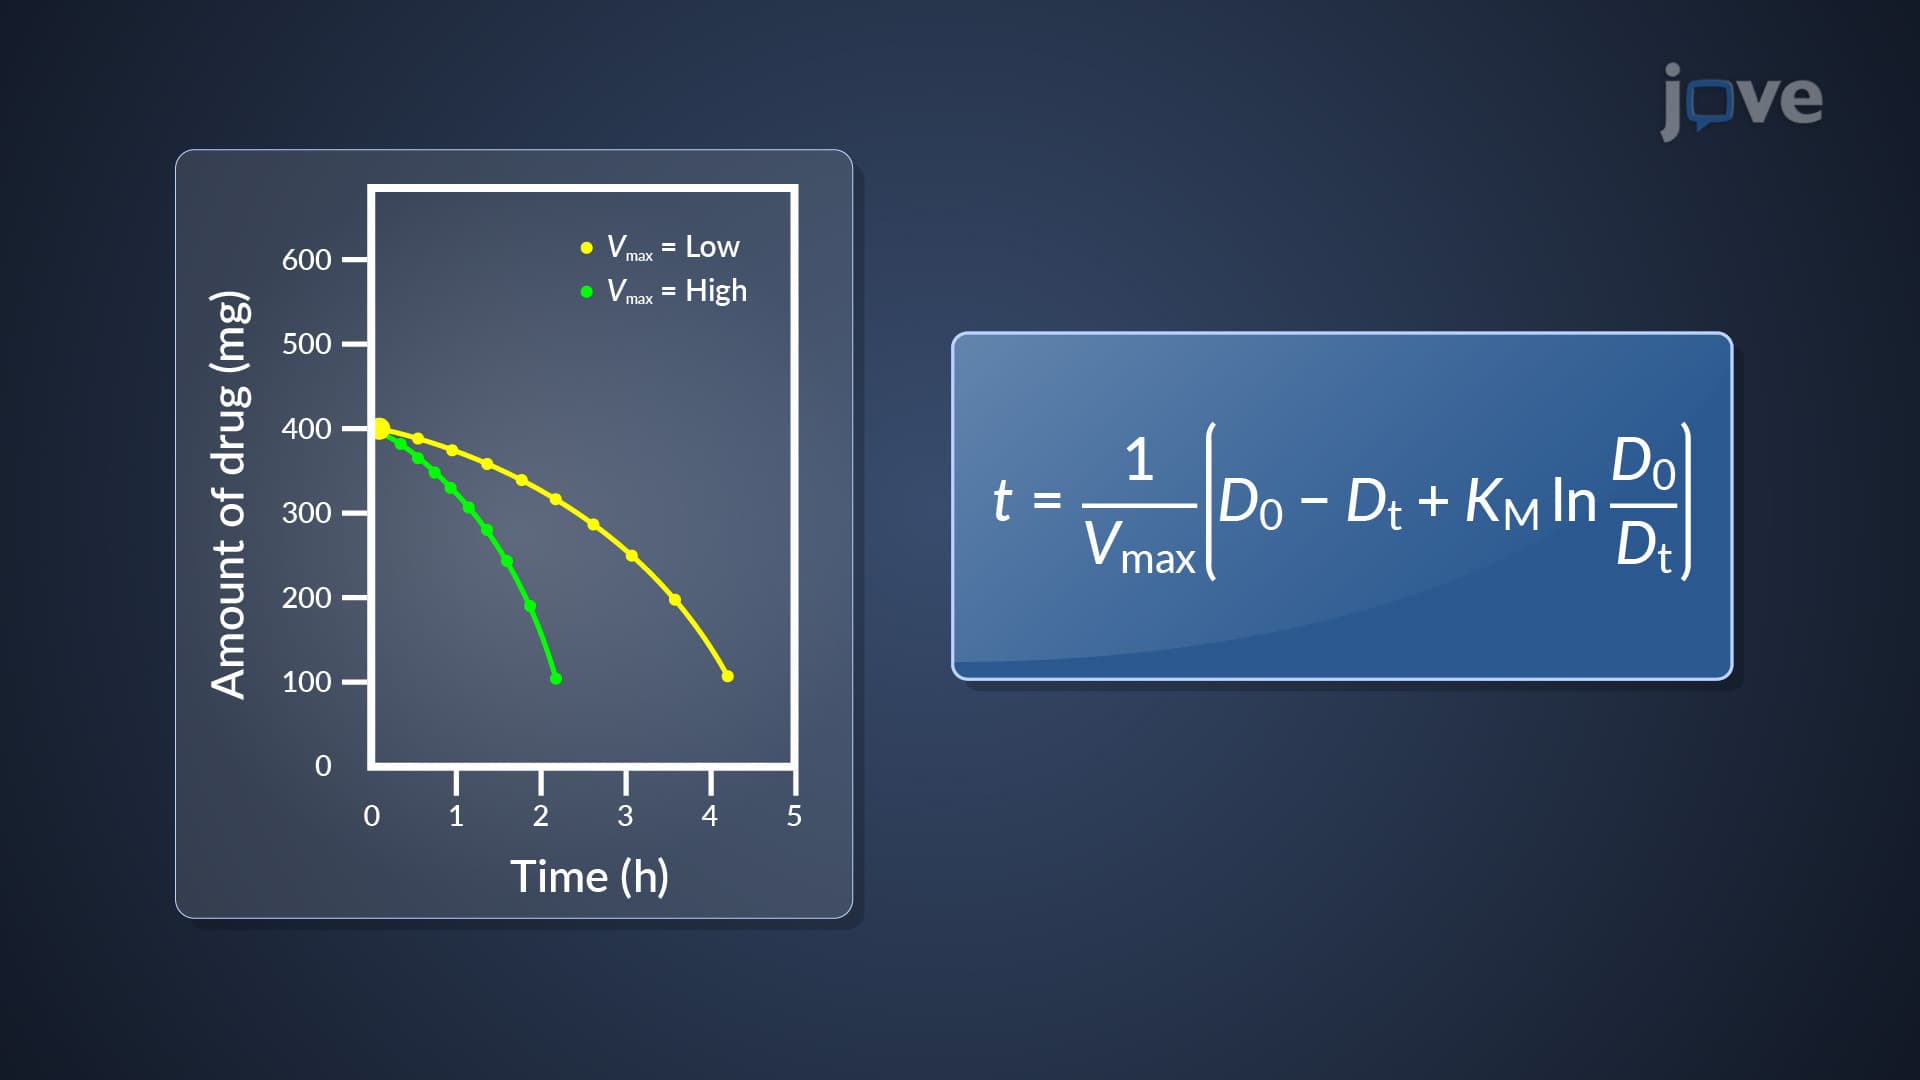
Nonlinear Pharmacokinetics: Drug Elimination for IV Bolus Injection
Following the administration of a single intravenous (IV) bolus injection, we can determine the concentration of the drug in the plasma at any given time. This calculation is achieved using a specific equation that integrates the values of Vmax and KM.
We can also...
 01:24
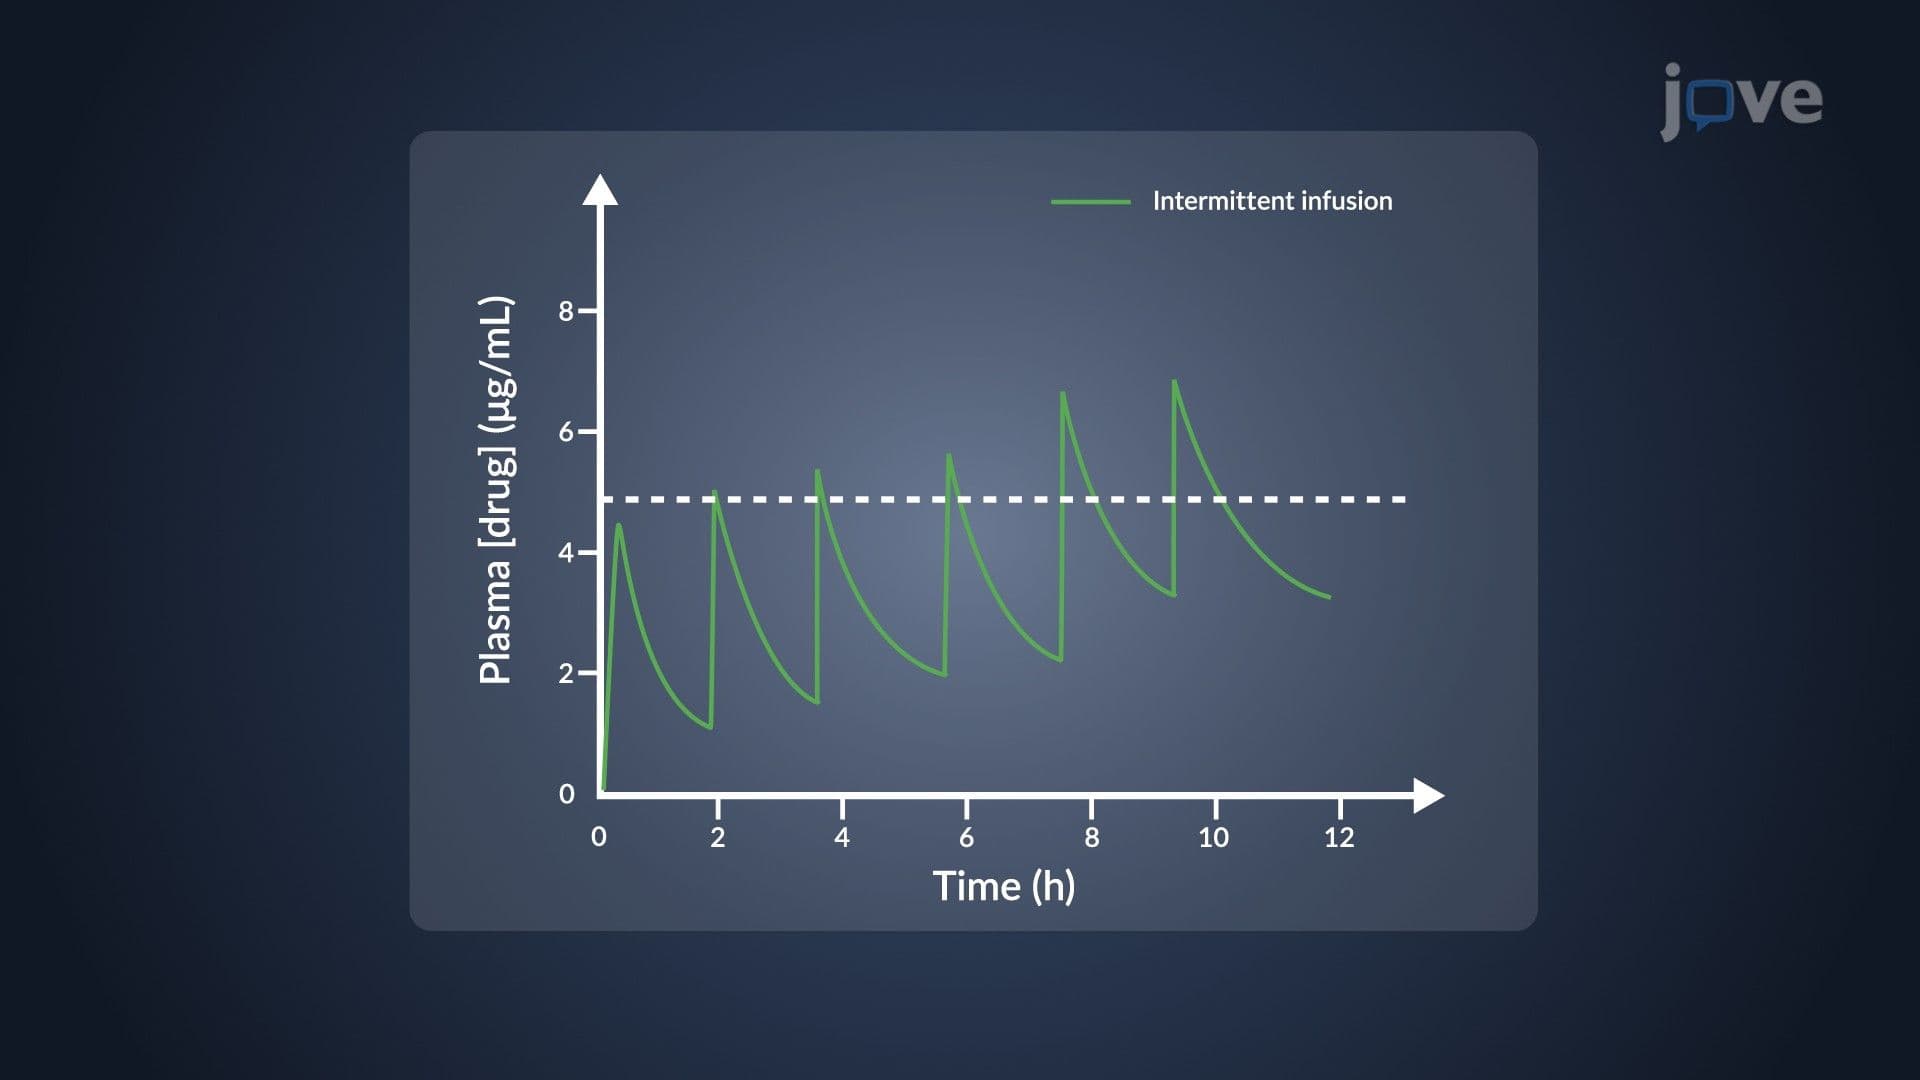
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:18
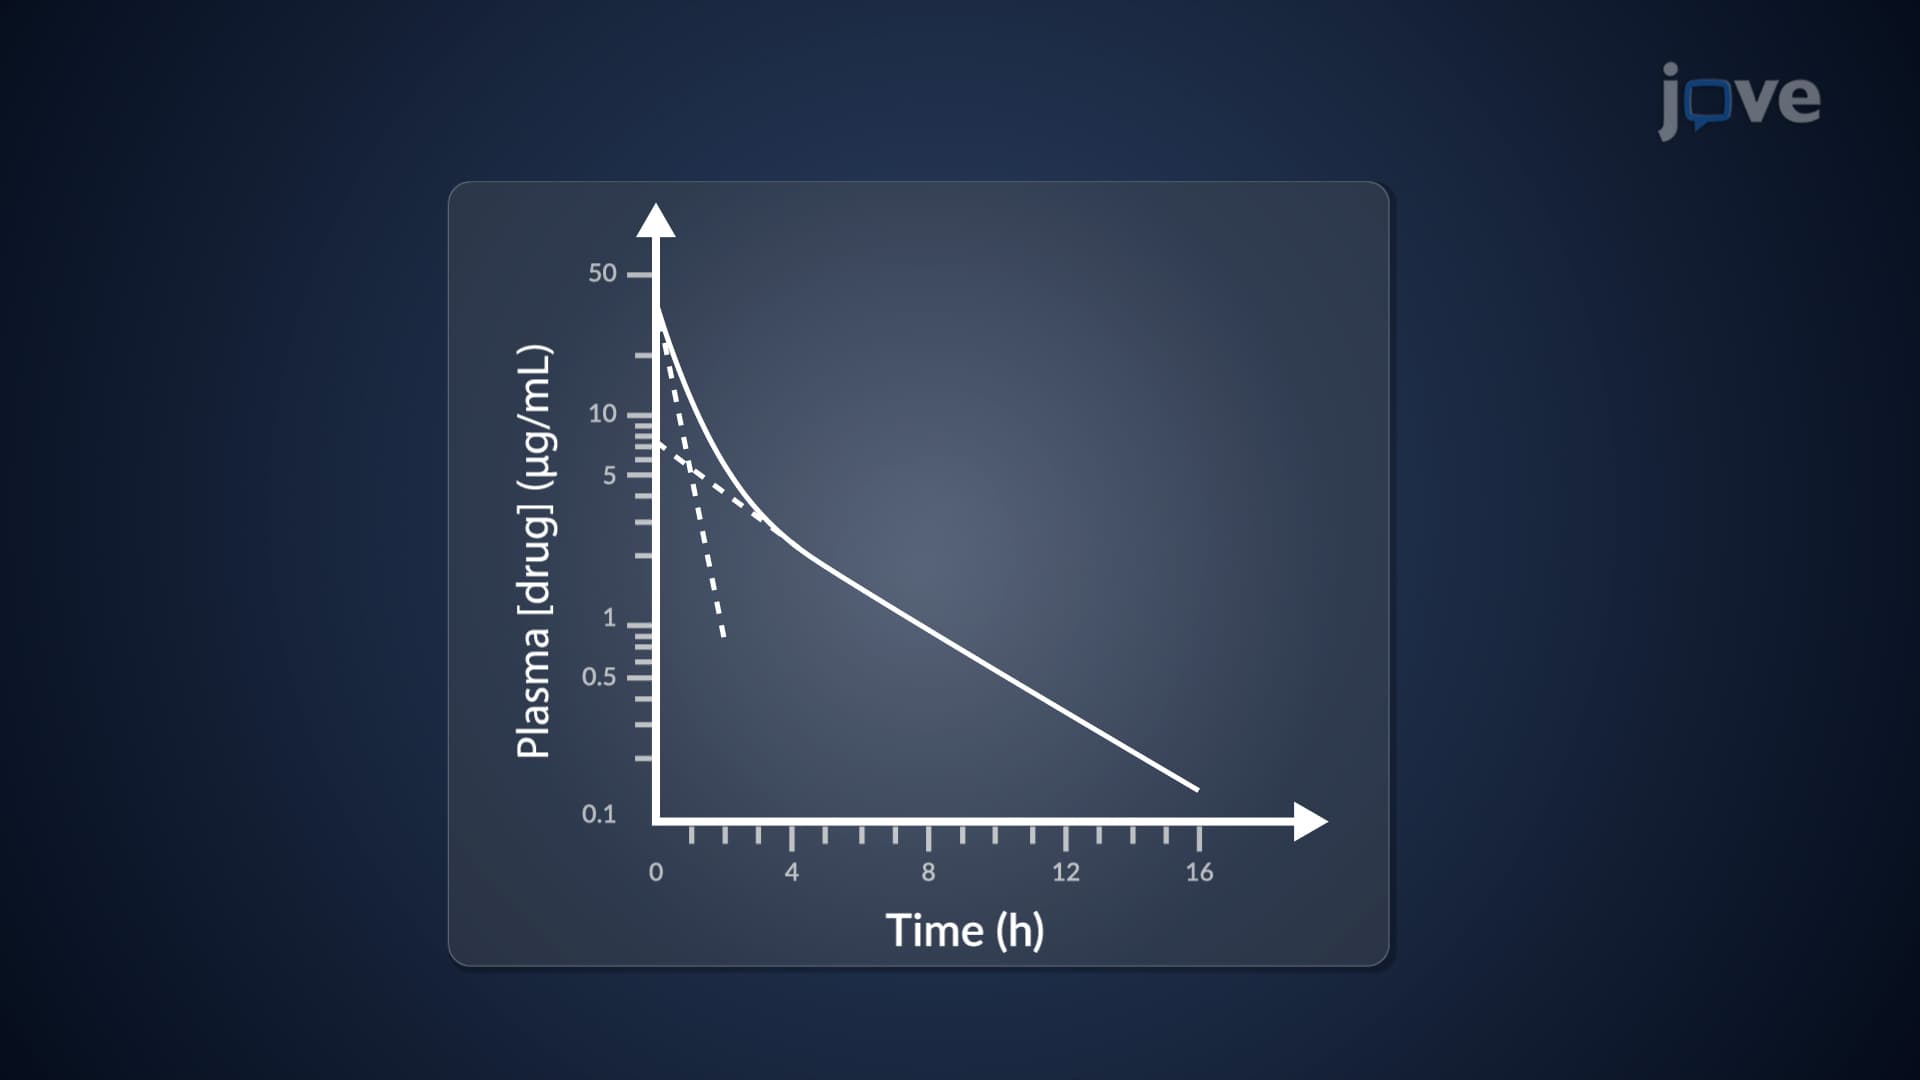
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...
 01:09
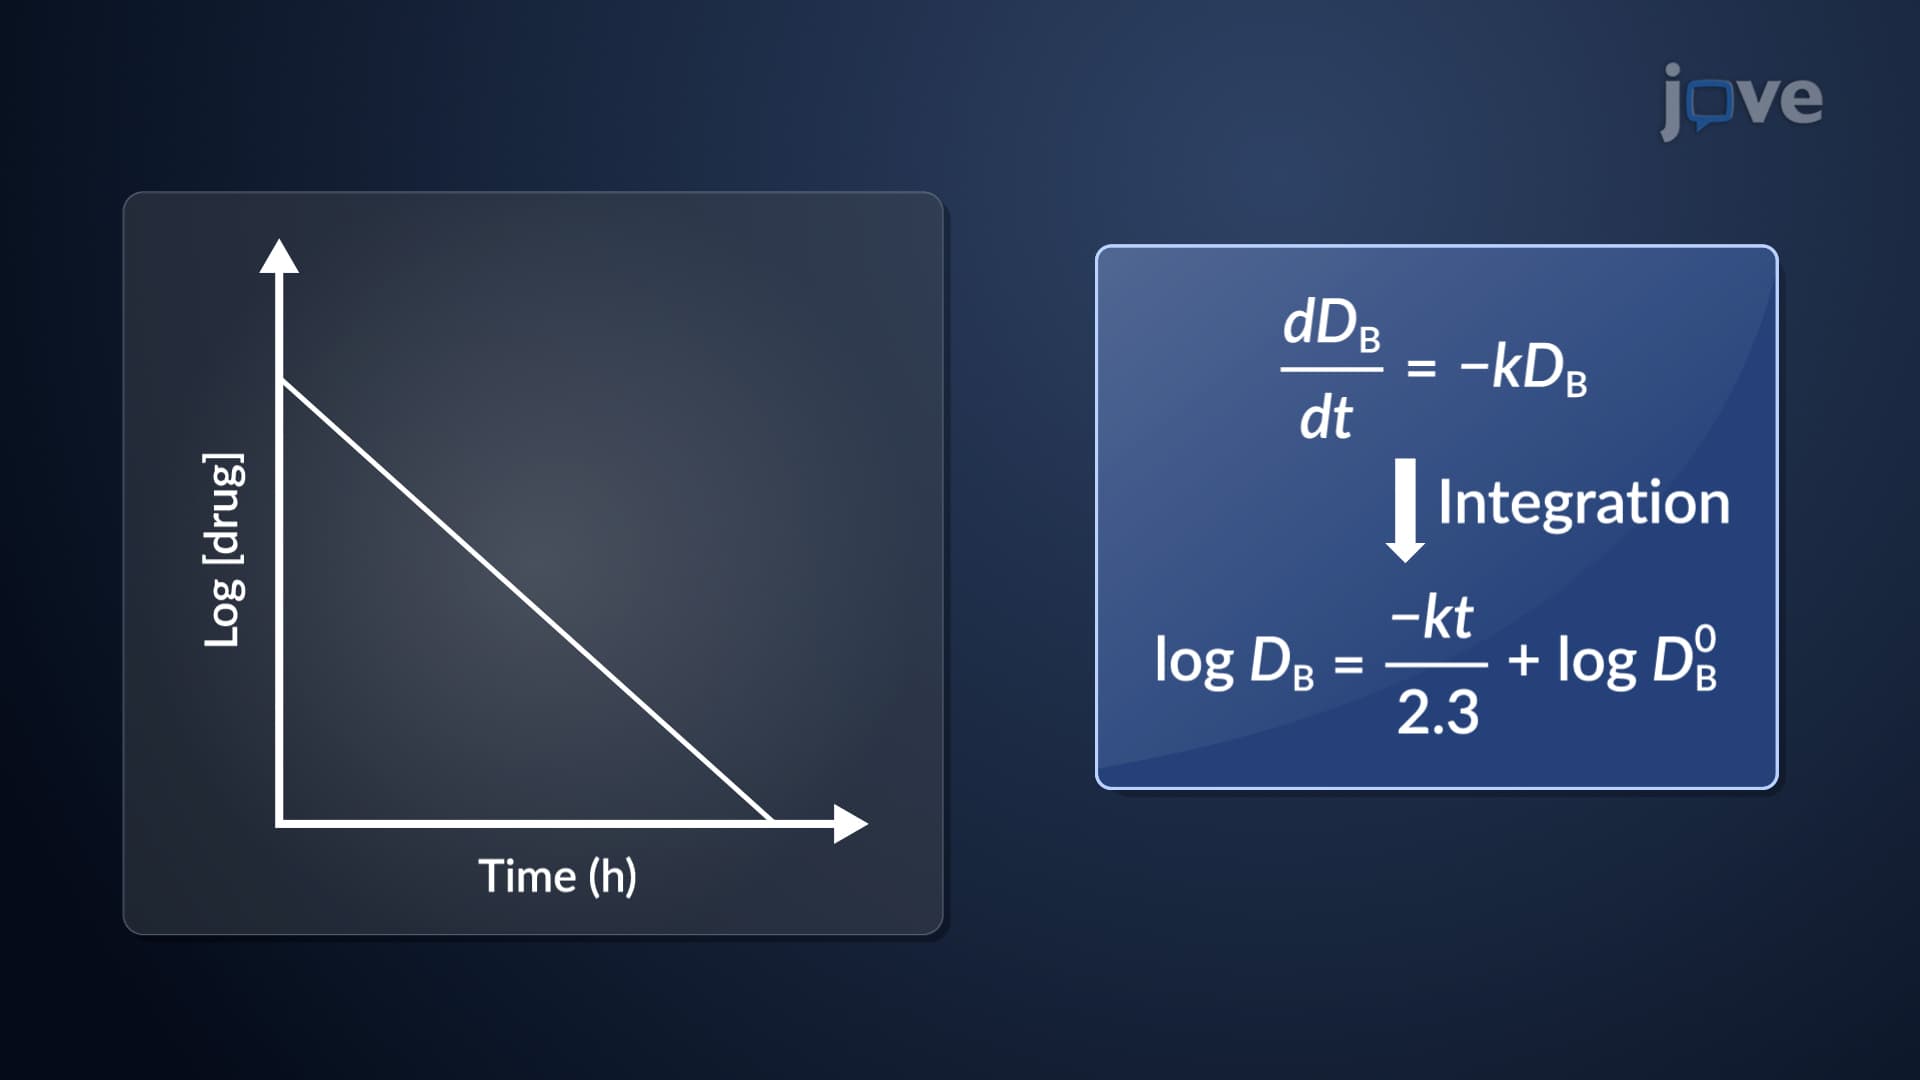
One-Compartment Open Model for IV Bolus Administration: Estimation of Elimination Rate Constant, Half-Life and Volume of Distribution