

Cardiovascular Testing and Clinical Outcomes in Emergency Department Patients With Chest Pain
Alexander T Sandhu1,2,3, Paul A Heidenreich1,3, Jay Bhattacharya2,3
1Veterans Affairs Palo Alto Health Care System, Palo Alto, California.

Insights
Routine cardiac testing for emergency department patients with chest pain increases downstream procedures like angiography and revascularization. However, this testing does not reduce acute myocardial infarction admissions, suggesting it may not be routinely warranted.
Area of Science:
- Cardiology
- Emergency Medicine
- Health Services Research
Background:
- Patients presenting to the emergency department (ED) with chest pain undergo noninvasive testing and coronary angiography, but outcomes are uncertain.
- Evaluating the impact of these diagnostic strategies on patient outcomes is crucial for optimizing care.
Purpose of the Study:
- To determine if cardiovascular testing (noninvasive imaging or coronary angiography) is associated with changes in coronary revascularization or acute myocardial infarction (AMI) admission rates.
- To assess outcomes in patients presenting to the ED with chest pain but without initial findings of ischemia.
Main Methods:
- Retrospective cohort analysis of national claims data (Truven MarketScan) from 2011-2012.
- Used weekday vs. weekend presentation as an instrumental variable to adjust for unobserved case-mix variation.
- Included 926,633 privately insured patients aged 18-64 presenting to the ED with chest pain without initial ischemia.
Main Results:
- Testing within 30 days was linked to increased coronary angiography and revascularization at 1 year, but not a significant change in AMI admissions.
- Testing within 2 days also showed increased coronary revascularization without a difference in AMI admissions.
- Patients receiving testing had higher baseline risk and AMI admission rates than those not tested.
Conclusions:
- Cardiac testing in chest pain patients is associated with increased downstream procedures but not reduced AMI admissions.
- Routine cardiac testing may not be warranted for all patients presenting with chest pain.
- Further research is needed to identify high-risk subgroups who may benefit from specific testing strategies.
Importance:
Noninvasive testing and coronary angiography are used to evaluate patients who present to the emergency department (ED) with chest pain, but their effects on outcomes are uncertain.
Objective:
To determine whether cardiovascular testing-noninvasive imaging or coronary angiography-is associated with changes in the rates of coronary revascularization or acute myocardial infarction (AMI) admission in patients who present to the ED with chest pain without initial findings of ischemia.
Design, Setting, And Participants:
This retrospective cohort analysis used weekday (Monday-Thursday) vs weekend (Friday-Sunday) presentation as an instrument to adjust for unobserved case-mix variation (selection bias) between 2011 and 2012. National claims data (Truven MarketScan) was used. The data included a total of 926 633 privately insured patients ages 18 to 64 years who presented to the ED with chest pain without initial diagnosis consistent with acute ischemia.
Exposures:
Noninvasive testing or coronary angiography within 2 days or 30 days of presentation.
Main Outcomes And Measures:
The primary end points were coronary revascularization (percutaneous coronary intervention or coronary artery bypass graft surgery) and AMI admission at 7, 30, 180, and 365 days. The secondary end points were coronary angiography and coronary artery bypass grafting in those who underwent angiography.
Results:
The patients were ages 18 to 64 years with an average age of 44.4 years. A total of 536 197 patients (57.9%) were women. Patients who received testing (224 973) had increased risk at baseline and had greater risk of AMI admission than those who did not receive testing (701 660) (0.35% vs 0.14% at 30 days). Weekday patients (571 988) had similar baseline comorbidities to weekend patients (354 645) but were more likely to receive testing. After risk factor adjustment, testing within 30 days was associated with a significant increase in coronary angiography (36.5 per 1000 patients tested; 95% CI, 21.0-52.0) and revascularization (22.8 per 1000 patients tested; 95% CI, 10.6-35.0) at 1 year but no significant change in AMI admissions (7.8 per 1000 patients tested; 95% CI, -1.4 to 17.0). Testing within 2 days was also associated with a significant increase in coronary revascularization but no difference in AMI admissions.
Conclusions And Relevance:
Cardiac testing in patients with chest pain was associated with increased downstream testing and treatment without a reduction in AMI admissions, suggesting that routine testing may not be warranted. Further research into whether specific high-risk subgroups benefit from testing is needed.
More Related Videos


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...
 01:29
Angina III: Clinical Manifestations and Assessment
 01:26
Exercise Stress Test
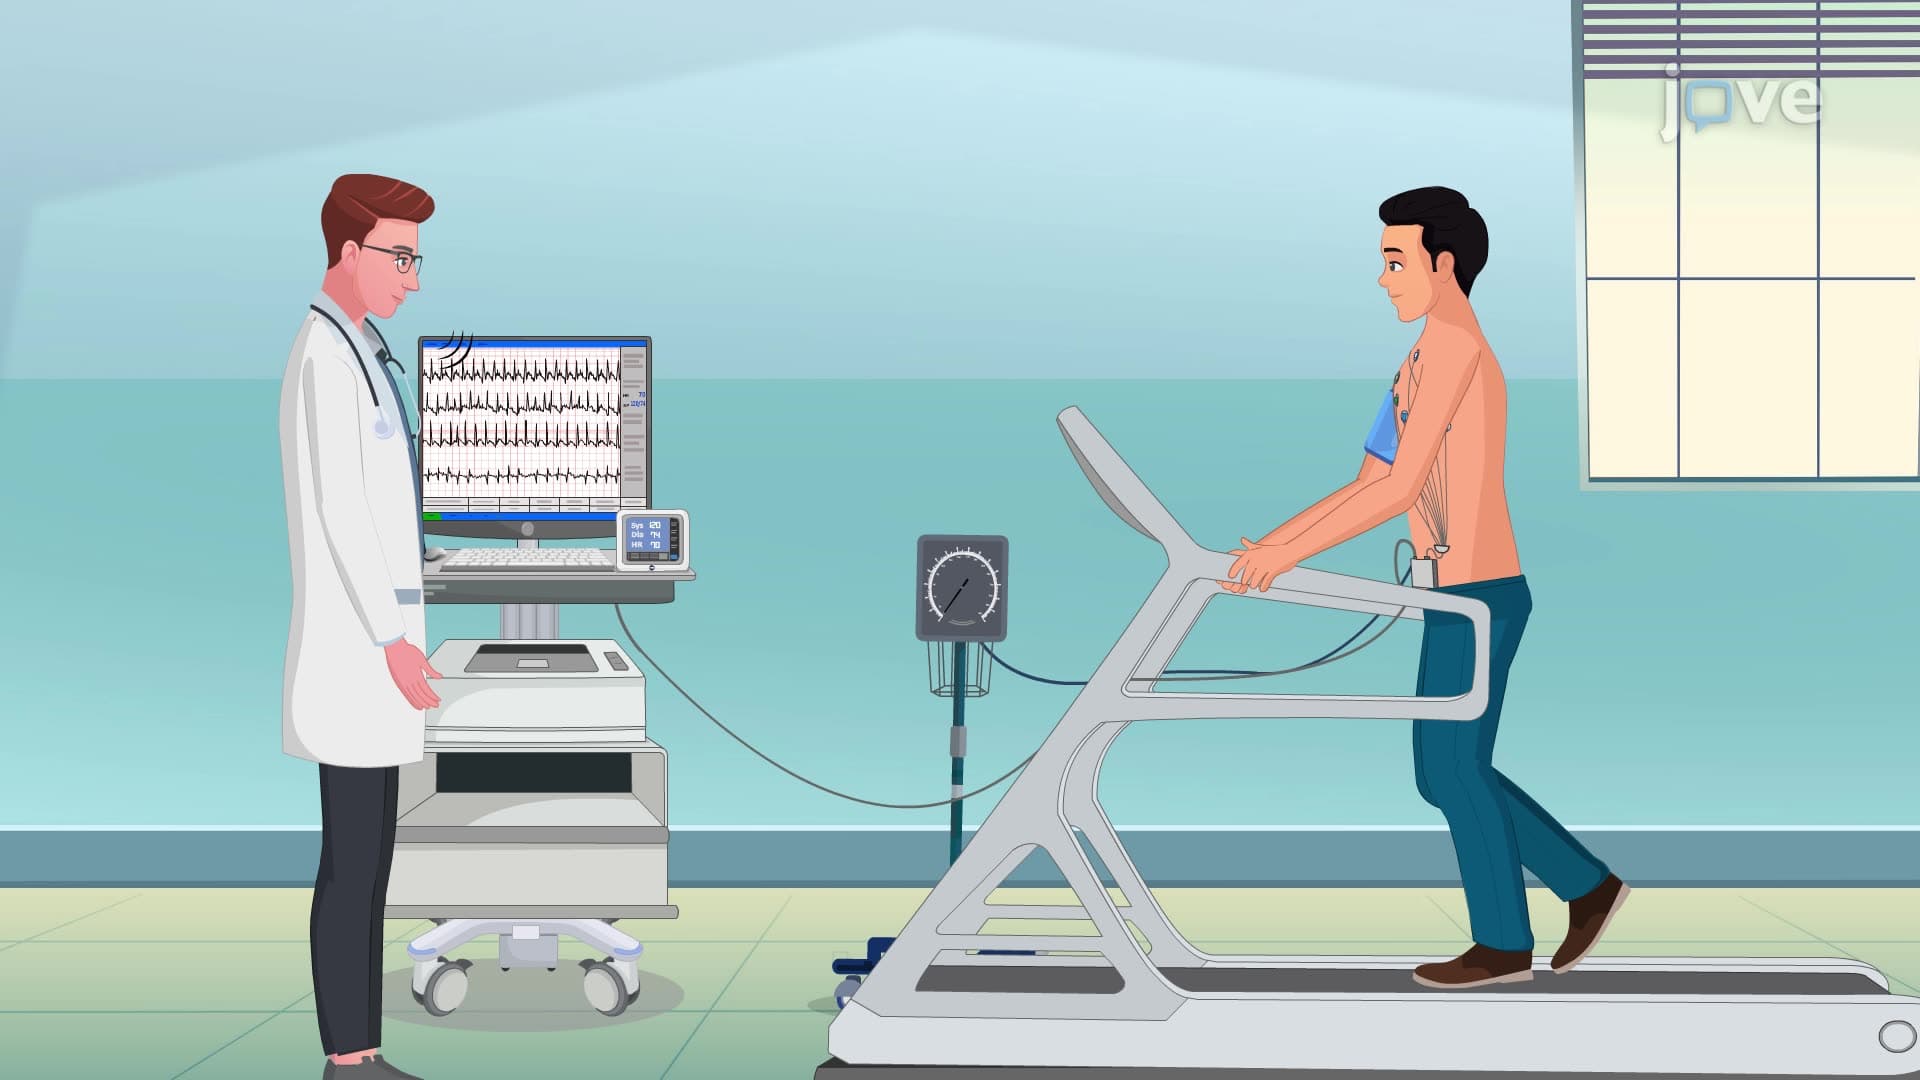
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:30
Introduction Cardiac Emergencies
 01:27
Coronary Artery Disease V: Interprofessional Care