Related Experiment Video
Updated: Feb 27, 2026
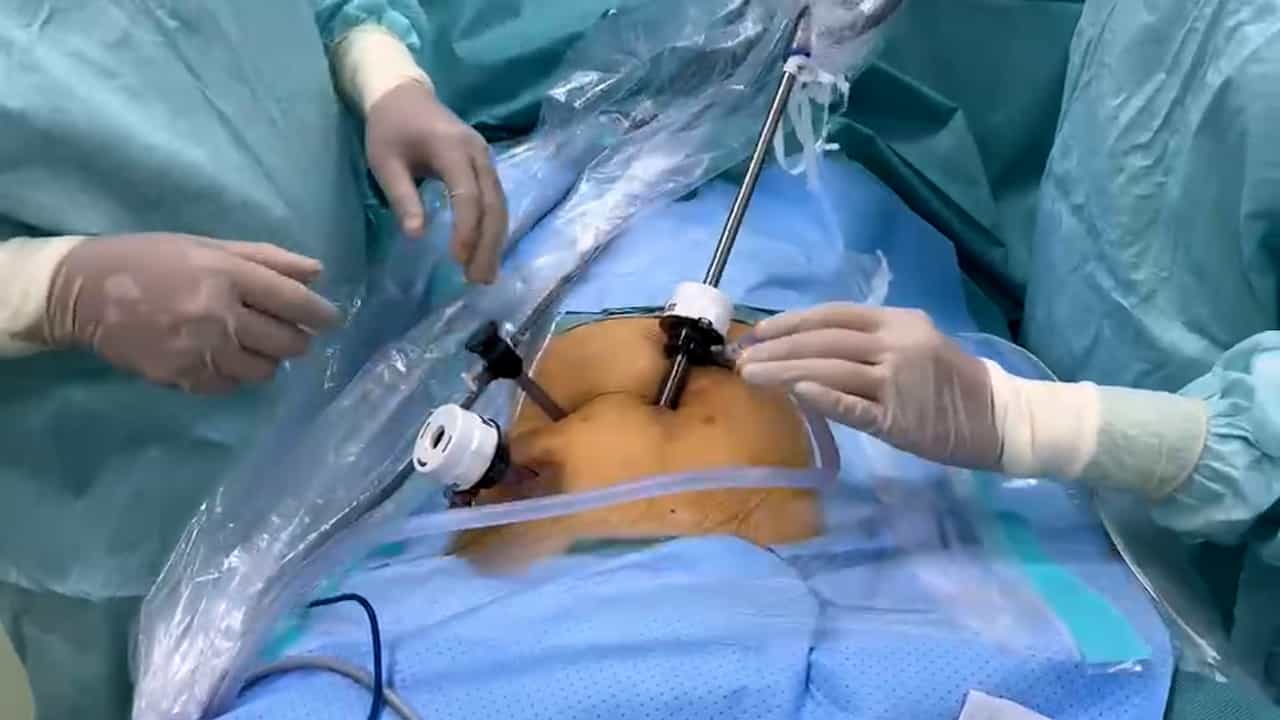
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
[A retrospective controlled clinical study of single-incision plus one port laparoscopic surgery for sigmoid colon
1Department of General Surgery, Nanfang Hospital, Southern Medical University, Guangzhou 510515, China.

Abstract:
Objective: To evaluate the short-term and oncologic outcomes of single-incision plus one port laparoscopic surgery (SILS+ 1) for sigmoid colon and upper rectal cancer. Methods: The clinic data of 46 patients with sigmoid colon and upper rectal cancer underwent SILS+ 1 at Department of General Surgery, Nanfang Hospital, Southern Medical University from September 2013 to September 2014 were retrospectively reviewed (SILS+ 1 group). After generating 1∶1 ration propensity scores given the covariates of age, gender, body mass index, American Society of Anesthesiologists score, surgeons, tumor location, the distance of tumor from anal, tumor diameter, and pathologic TNM stage, 46 patients with sigmoid colon and upper rectal cancer underwent conventional laparoscopic surgery (CLS) in the same time were matched as CLS group. The baseline characteristics and short-term outcomes were compared using t test, χ(2) test or Wilcoxon signed ranks test. Kaplan-Meier survival curves and Log-rank tests demonstrated the distribution of disease free survival. Results: The two study groups were well balanced with respect to the baseline characteristics of the propensity score derivation model. As compared to the CLS group, patients in SILS+ 1 group had a smaller incision ((6.9±1.1) cm vs. (8.4±1.2) cm, t=6.502, P=0.000), less estimated blood loss (20(11) ml vs. 50(30) ml, Z=2.414, P=0.016), shorter intracorporeal operating time ((67.0±25.8) minutes vs. (75.5±27.7) minutes, t=2.062, P=0.042) and significantly faster recovery course including shorter time to first ambulation ((46.7±20.3) hours vs. (78.6±28.0) hours, t=6.255, P=0.000), shorter time to first oral diet ((64.7±28.8) hours vs. (77.1±30.0) hours, t=2.026, P=0.047), shorter time of postoperative hospital stay ((7.8±2.2) days vs. (6.5±2.2) days, t=2.680, P=0.009), and lower postoperative visual analogue scale scores (F=4.721, P=0.032). No significant difference was observed in total operating time, postoperative morbidity, first time to flatus and defecation, analgesic use, number of retrieved lymph nodes and resection margin. During the median follow-up period of 33 months (ranging from 7 to 39 months) , there was no significant difference between the two groups in terms of 3-year disease-free survival (SILS+ 1: 91.3%, CLS: 93.4%, P=1.000). The recurrence rates of SILS+ 1 group and CLS groups were 8.7% (4/46) and 6.5% (3/46), respectively. Conclusion: For experienced CLS surgeons, the SILS+ 1 for sigmoid colon and upper rectal cancer would be easiness, safe and efficient alternative.
More Related Videos
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
 07:22
Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
