Related Experiment Video
Updated: Feb 27, 2026


Pretargeted Radioimmunotherapy Based on the Inverse Electron Demand Diels-Alder Reaction
Published on: January 29, 2019
Dose Titration Algorithm Tuning (DTAT) should supersede 'the' Maximum Tolerated Dose (MTD) in oncology dose-finding
1Precision Methodologies, LLC, Seattle, USA.

Abstract:
Background. Absent adaptive, individualized dose-finding in early-phase oncology trials, subsequent 'confirmatory' Phase III trials risk suboptimal dosing, with resulting loss of statistical power and reduced probability of technical success for the investigational therapy. While progress has been made toward explicitly adaptive dose-finding and quantitative modeling of dose-response relationships, most such work continues to be organized around a concept of 'the' maximum tolerated dose (MTD). The purpose of this paper is to demonstrate concretely how the aim of early-phase trials might be conceived, not as 'dose-finding', but as dose titration algorithm (DTA)-finding. Methods. A Phase I dosing study is simulated, for a notional cytotoxic chemotherapy drug, with neutropenia constituting the critical dose-limiting toxicity. The drug's population pharmacokinetics and myelosuppression dynamics are simulated using published parameter estimates for docetaxel. The amenability of this model to linearization is explored empirically. The properties of a simple DTA targeting neutrophil nadir of 500 cells/mm 3 using a Newton-Raphson heuristic are explored through simulation in 25 simulated study subjects. Results. Individual-level myelosuppression dynamics in the simulation model approximately linearize under simple transformations of neutrophil concentration and drug dose. The simulated dose titration exhibits largely satisfactory convergence, with great variance in individualized optimal dosing. Some titration courses exhibit overshooting. Conclusions. The large inter-individual variability in simulated optimal dosing underscores the need to replace 'the' MTD with an individualized concept of MTD i . To illustrate this principle, the simplest possible DTA capable of realizing such a concept is demonstrated. Qualitative phenomena observed in this demonstration support discussion of the notion of tuning such algorithms. Although here illustrated specifically in relation to cytotoxic chemotherapy, the DTAT principle appears similarly applicable to Phase I studies of cancer immunotherapy and molecularly targeted agents.
Insights
This study proposes replacing the maximum tolerated dose (MTD) with individualized dose titration algorithms (DTAs) in early-phase oncology trials. Simulations show DTAs achieve better dose individualization, improving cancer therapy development.
Area of Science:
- Pharmacology and Toxicology
- Clinical Trial Design
- Oncology Drug Development
Background:
- Current early-phase oncology trials often lack adaptive, individualized dose-finding, risking suboptimal dosing in later phases.
- The traditional focus on a single maximum tolerated dose (MTD) may not adequately address inter-individual variability.
- There is a need for advanced methodologies to optimize dose selection in early clinical development.
Purpose of the Study:
- To demonstrate that early-phase trials should aim for dose titration algorithm (DTA) finding, not just dose-finding.
- To propose and evaluate a novel DTA for individualized dose optimization in oncology.
- To highlight the importance of individualized dosing concepts over a single MTD.
Main Methods:
- Simulated a Phase I dosing study for a cytotoxic chemotherapy agent, using docetaxel pharmacokinetics and myelosuppression dynamics.
- Investigated the linearization of population pharmacokinetics and myelosuppression under dose and neutrophil concentration transformations.
- Employed a simple DTA with a Newton-Raphson heuristic to target a specific neutrophil nadir in simulated subjects.
Main Results:
- Simulated myelosuppression dynamics showed approximate linearization with dose and neutrophil concentration transformations.
- The developed DTA demonstrated largely satisfactory convergence for dose titration across simulated subjects.
- Significant inter-individual variability in optimal dosing was observed, with some instances of overshooting.
Conclusions:
- The substantial inter-individual variability necessitates a shift from a single MTD to an individualized MTD (MTDi).
- A simple DTA can effectively realize the concept of individualized MTD, improving dose selection.
- The DTA principle is applicable beyond cytotoxic chemotherapy to other oncology agents like immunotherapies and targeted therapies.
More Related Videos
 07:57
Positron Emission Tomography-based Dose Painting Radiation Therapy in a Glioblastoma Rat Model using the Small Animal Radiation Research Platform
Published on: March 24, 2022
 08:34
Proton Therapy Delivery and Its Clinical Application in Select Solid Tumor Malignancies
Published on: February 6, 2019
Related Concept Videos
 01:21
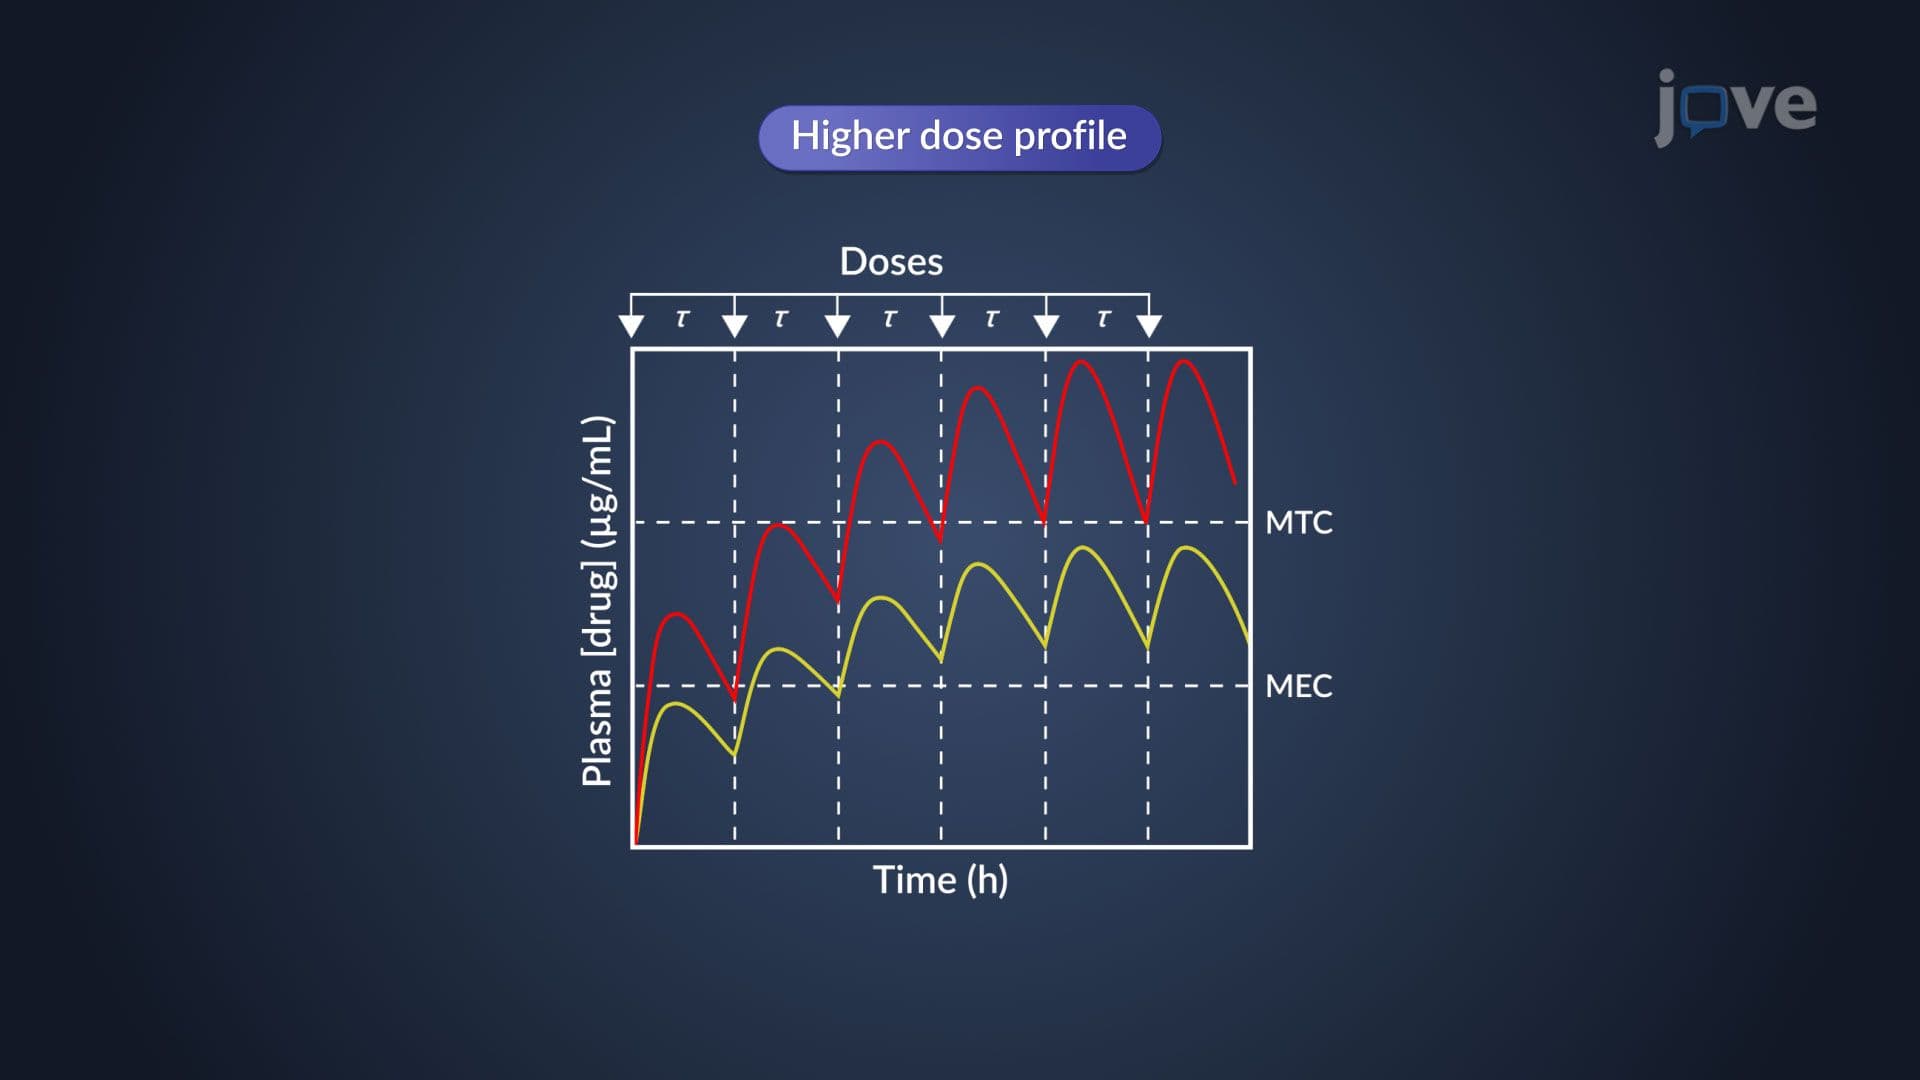
Dose Size and Dosing Frequency: Determination Methods
 01:21
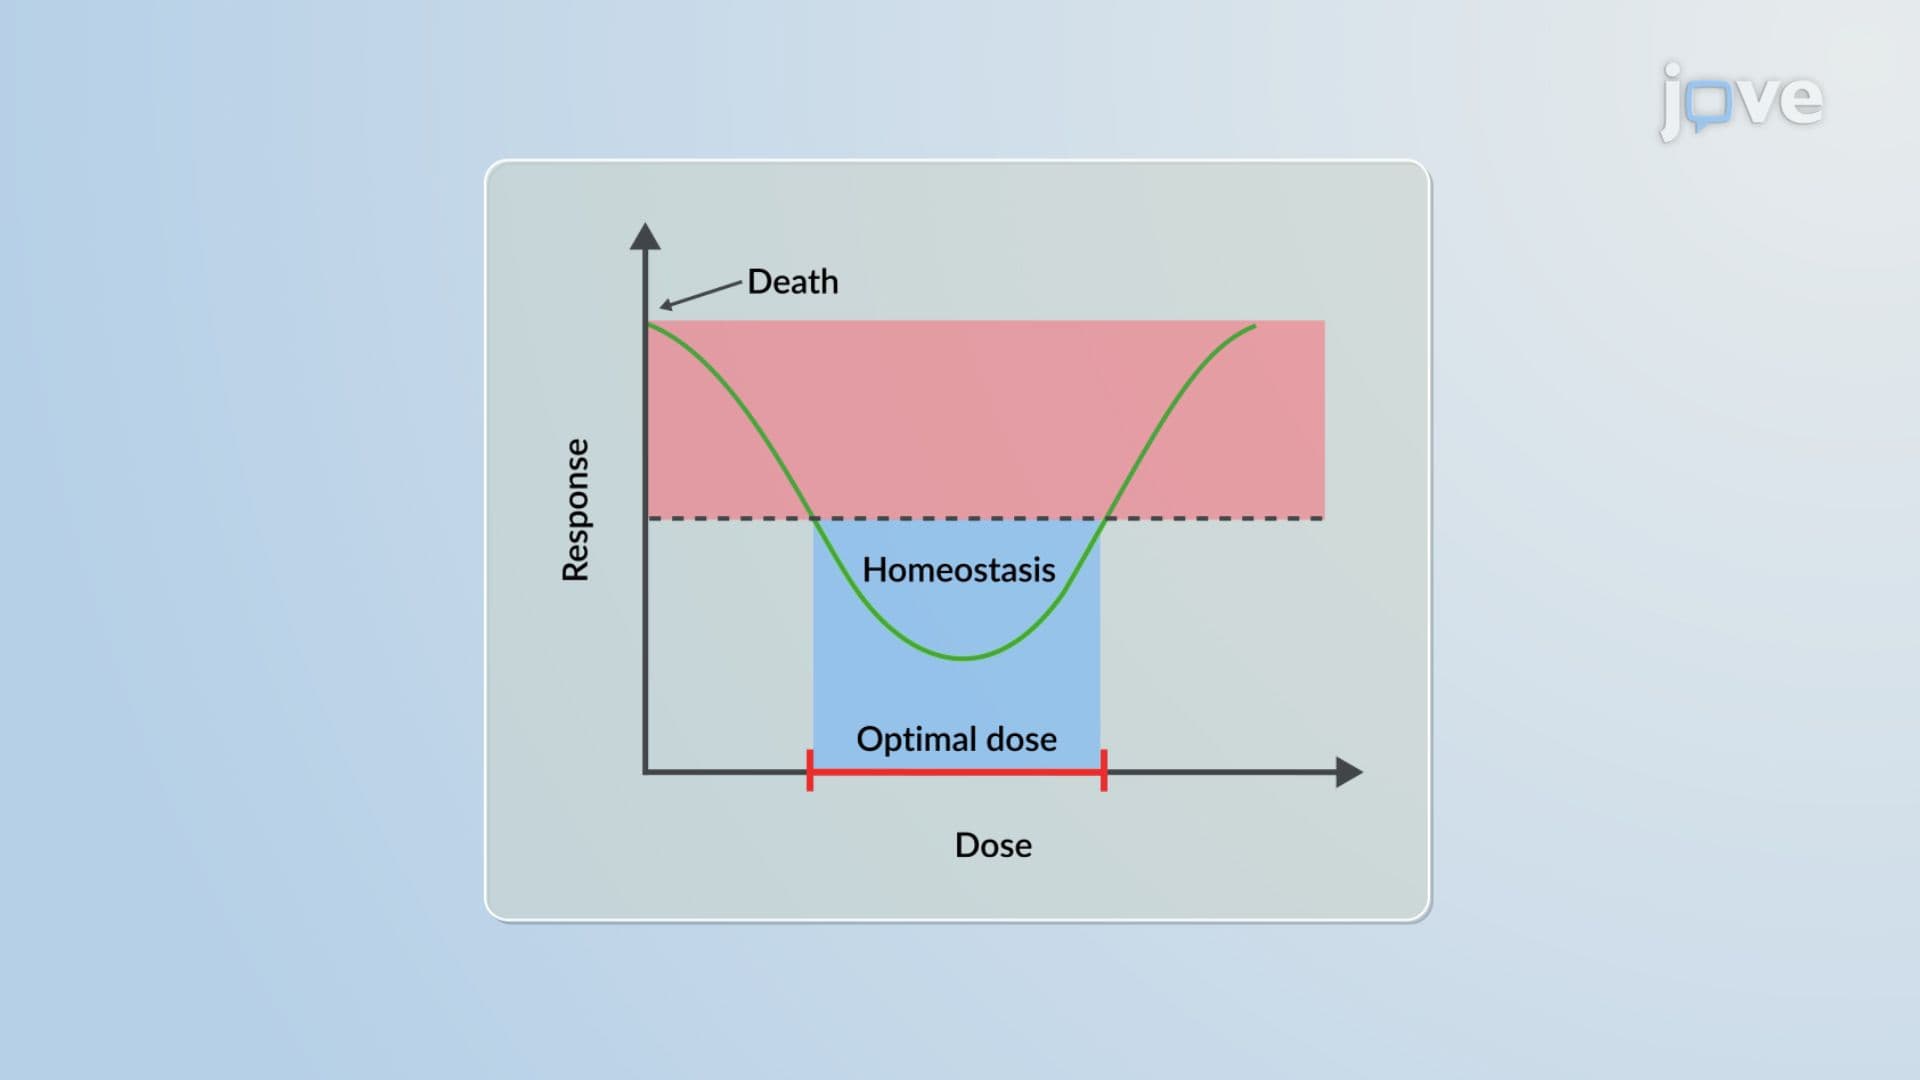
Dose Response Curve: Conventional Versus Nonmonotonic
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:15
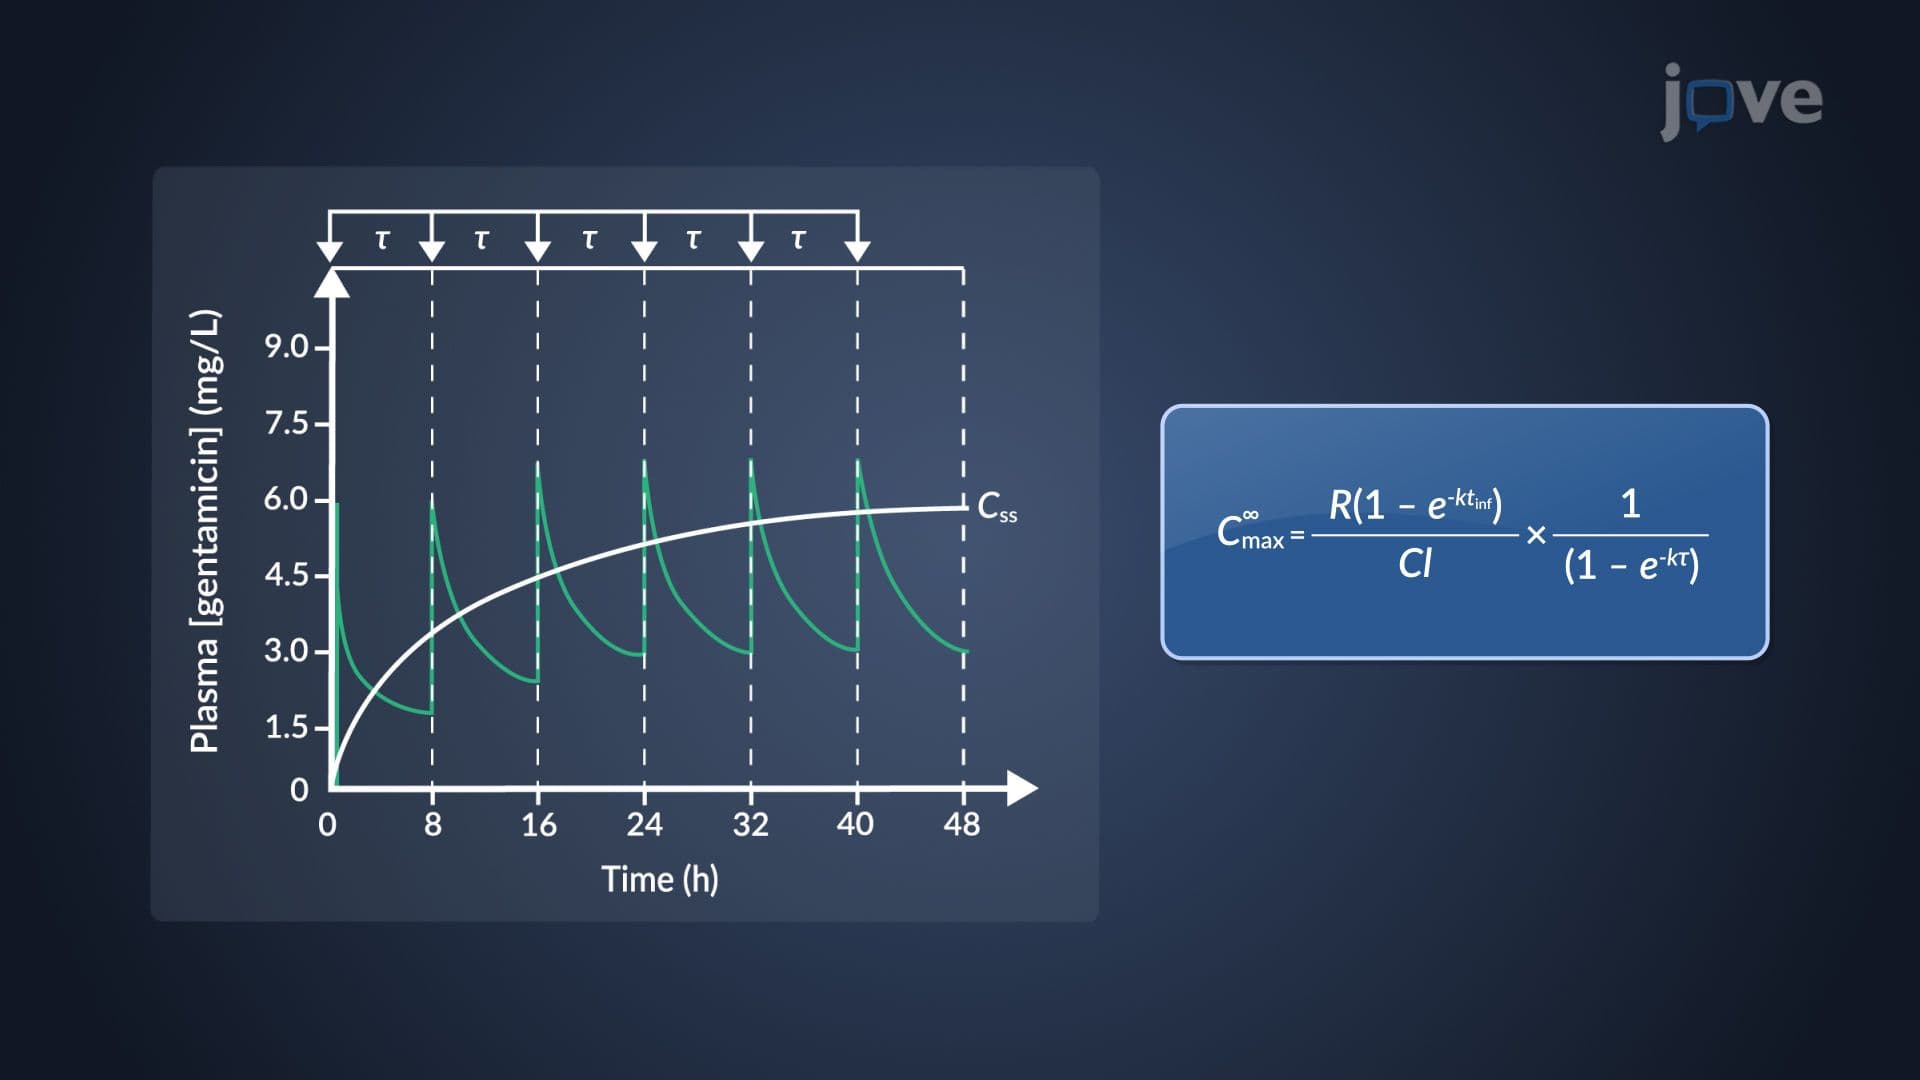
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:28
Dosage Regimens: Designs and Approaches