Related Experiment Video
Updated: Feb 27, 2026


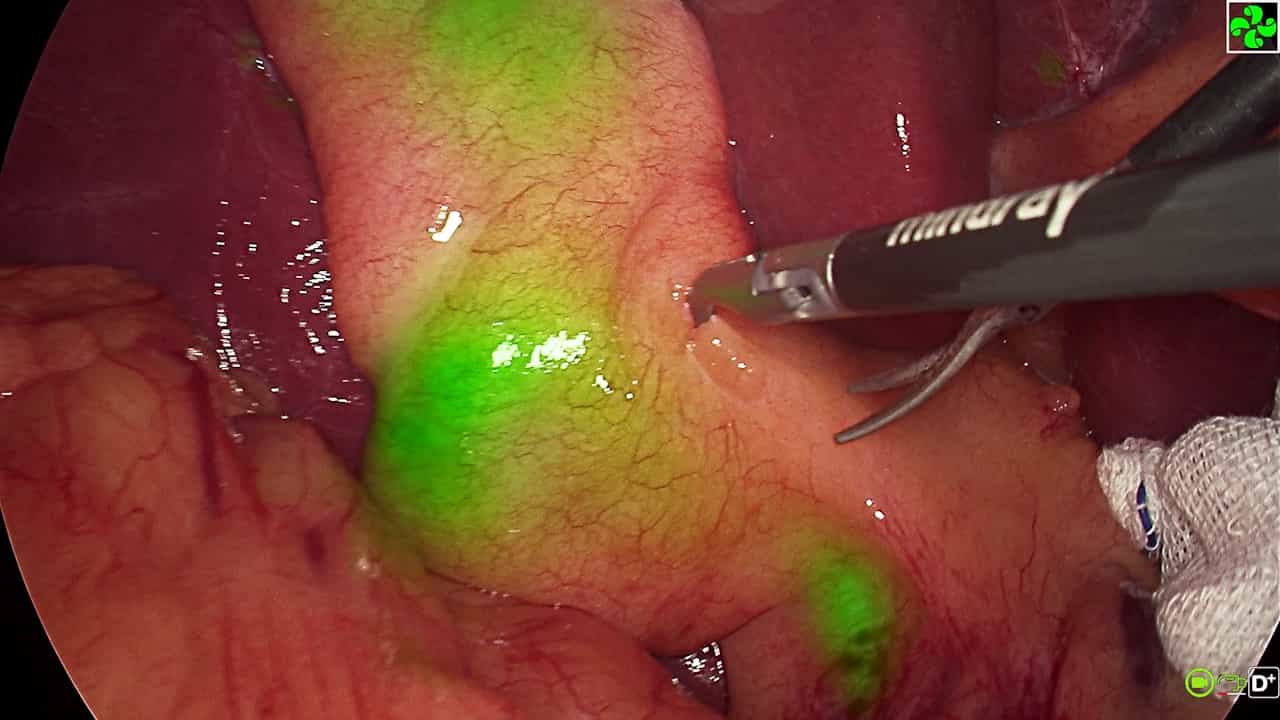
Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Crohn's Strictures-Moving Away from the Knife
Emily Stenke1, Billy Bourke1,2, Ulla Knaus1
1School of Medicine, Conway Institute, University College Dublin, Dublin, Ireland.

Insights
Crohn's disease strictures, a common complication, involve inflammation and fibrosis. Research focuses on targeting TGFβ1 signaling for potential antifibrotic therapies in inflammatory bowel disease.
Area of Science:
- Gastroenterology
- Immunology
- Pathology
Background:
- Crohn's disease (CD) incidence is rising, especially in children.
- Fibrotic strictures are a frequent complication of CD, causing obstruction.
- Current treatments lack antifibrotic options for CD strictures.
Purpose of the Study:
- To review the pathophysiology of fibrotic strictures in Crohn's disease.
- To explore the role of TGFβ signaling in CD fibrosis.
- To highlight the potential for antifibrotic therapies.
Main Methods:
- Histological examination of Crohn's strictures.
- Review of molecular signaling pathways involved in fibrosis.
- Analysis of current research on TGFβ1 downstream targets.
Main Results:
- Crohn's strictures exhibit thickened muscle layers and submucosa with collagen deposition.
- Activated myofibroblasts contribute to extracellular matrix accumulation.
- Transforming growth factor-β (TGFβ) signaling drives myofibroblast differentiation and matrix deposition.
Conclusions:
- Understanding TGFβ1 signaling is crucial for developing antifibrotic treatments.
- Targeting TGFβ1 downstream pathways offers a promising avenue for future CD antifibrotic therapy.
- Antifibrotic therapies could significantly improve outcomes for Crohn's disease patients with strictures.
Abstract:
Crohn's disease (CD) is a lifelong inflammatory bowel disease with a rapidly rising incidence in the pediatric population. A common complication of CD is the development of fibrotic strictures, which may be present at initial diagnosis or develop many years later. Clinical presentation depends on stricture location and degree of obstruction, and strictures frequently contain a mixture of inflammatory and fibrotic tissue. Histological examination of Crohn's strictures shows thickening of the muscular layers and the submucosa, where increased collagen deposition by activated myofibroblasts is concentrated around islands of smooth muscle cells and at the superficial margin of the muscularis propria. No antifibrotic therapies for Crohn's strictures exist. Profibrotic transforming growth factor-β (TGFβ)/bone morphogenetic protein signaling stimulates myofibroblast differentiation and extracellular matrix deposition. Understanding and targeting TGFβ1 downstream signaling is the main focus of current research, raising the possibility of specific antifibrotic therapy in CD becoming available in the future.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Aneurysm III: Interprofessional Care
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...