Related Experiment Video
Updated: Feb 27, 2026
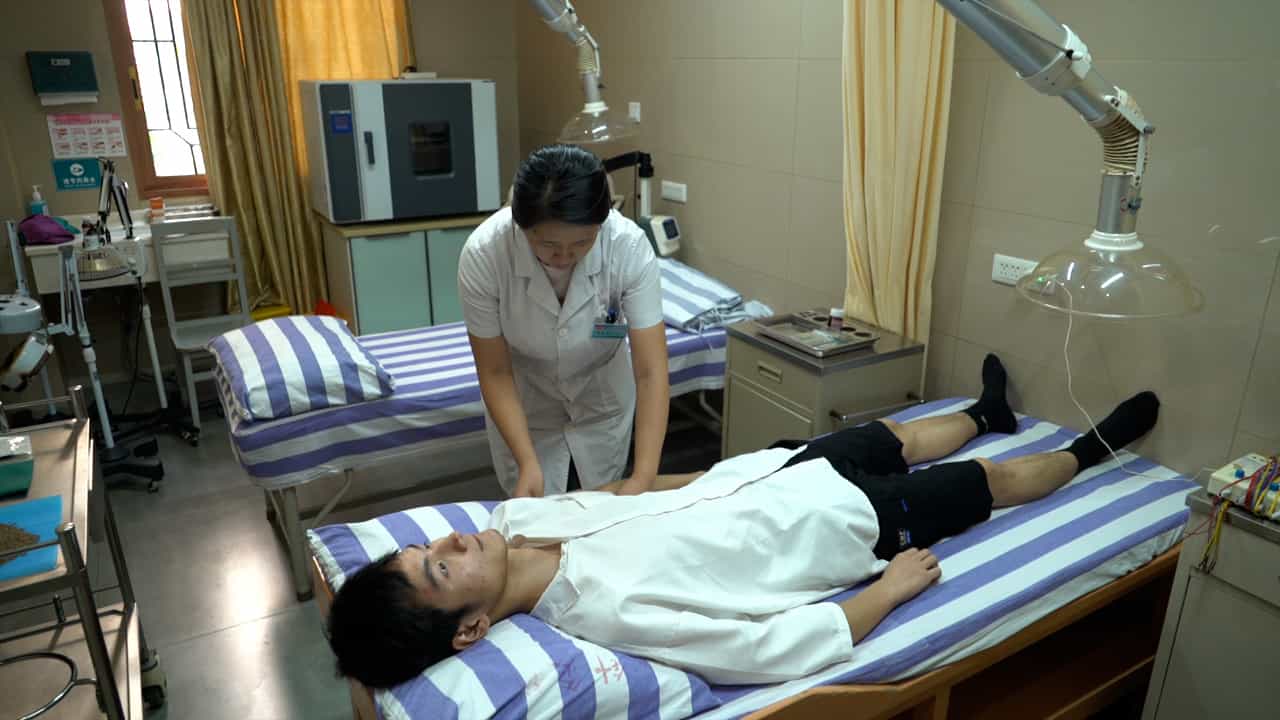

Electroacupuncture Combined with Chinese Medicine Ironing Therapy for Functional Constipation
Published on: July 5, 2024
Pros and Cons While Looking Through an Asian Window on the Rome IV Criteria for Irritable Bowel Syndrome: Pros
1Department of Gastroenterology, Sanjay Gandhi Postgraduate Institute of Medical Sciences, Lucknow, India.

A decade after Rome III, in 2016, Rome IV criteria were published. There are major differences between Rome IV and the earlier iteration, some of which are in line with Asian viewpoints. The clinical applicability of the Rome IV criteria of irritable bowel syndrome (IBS) in Asian perspective is reviewed here. Instead of considering functional gastrointestinal disorders (FGIDs) to be largely psychogenic, Rome IV suggested the importance of the gut over brain ("disorders of gut-brain interaction" not "brain-gut interaction"). The word "functional" is underplayed. Multi-dimensional clinical profile attempts to recognize micro-organic nature, like slow colon transit and fecal evacuation disorders in constipation and dietary intolerance including that of lactose and fructose, bile acid malabsorption, non-celiac wheat sensitivity, small intestinal bacterial overgrowth, and gastrointestinal infection in diarrhea. Overlap between different FGIDs has been recognized as Rome IV suggests these to be a spectrum rather than discrete disorders. Bloating, common in Asia, received attention, though less. Sub-typing of IBS may be more clinician-friendly now as the patient-reported stool form may be used than a diary. However, a few issues, peculiar to Asia, need consideration; Rome IV, like Rome III, suggests that Bristol type I-II stool to denote constipation though Asian experts include type III as well. Work-up for physiological factors should be given greater importance. Language issue is important. Bloating, common in IBS, should be listed in the criteria. Threshold values for symptoms in Rome IV criteria are based on Western data. Post-infectious malabsorption (tropical sprue) should be excluded to diagnose post-infectious IBS, particularly in Asia.
A decade after Rome III, in 2016, Rome IV criteria were published. There are major differences between Rome IV and the earlier iteration, some of which are in line with Asian viewpoints. The clinical applicability of the Rome IV criteria of irritable bowel syndrome (IBS) in Asian perspective is reviewed here. Instead of considering functional gastrointestinal disorders (FGIDs) to be largely psychogenic, Rome IV suggested the importance of the gut over brain ("disorders of gut-brain interaction" not "brain-gut interaction"). The word "functional" is underplayed. Multi-dimensional clinical profile attempts to recognize micro-organic nature, like slow colon transit and fecal evacuation disorders in constipation and dietary intolerance including that of lactose and fructose, bile acid malabsorption, non-celiac wheat sensitivity, small intestinal bacterial overgrowth, and gastrointestinal infection in diarrhea. Overlap between different FGIDs has been recognized as Rome IV suggests these to be a spectrum rather than discrete disorders. Bloating, common in Asia, received attention, though less. Sub-typing of IBS may be more clinician-friendly now as the patient-reported stool form may be used than a diary. However, a few issues, peculiar to Asia, need consideration; Rome IV, like Rome III, suggests that Bristol type I-II stool to denote constipation though Asian experts include type III as well. Work-up for physiological factors should be given greater importance. Language issue is important. Bloating, common in IBS, should be listed in the criteria. Threshold values for symptoms in Rome IV criteria are based on Western data. Post-infectious malabsorption (tropical sprue) should be excluded to diagnose post-infectious IBS, particularly in Asia.
More Related Videos


Related Concept Videos
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:17
Irritable Bowel Syndrome I: Introduction
IBS is a chronic condition that can persist over a long period or recur frequently.
The pathogenesis of IBS involves a complex interplay of the following factors:
Altered...
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...
 01:21
Drugs for Treatment of Constipation-Predominant IBS