Related Experiment Video
Updated: Feb 27, 2026


HPLC-based Assay to Monitor Extracellular Nucleotide/Nucleoside Metabolism in Human Chronic Lymphocytic Leukemia Cells
Published on: July 20, 2016
A3 Adenosine Receptors as Modulators of Inflammation: From Medicinal Chemistry to Therapy
Kenneth A Jacobson1, Stefania Merighi2, Katia Varani2
1Molecular Recognition Section, Laboratory of Bioorganic Chemistry, National Institute of Diabetes and Digestive and Kidney Diseases, National Institutes of Health, Bethesda, MD, 20892.

Abstract:
The A3 adenosine receptor (A3 AR) subtype is a novel, promising therapeutic target for inflammatory diseases, such as rheumatoid arthritis (RA) and psoriasis, as well as liver cancer. A3 AR is coupled to inhibition of adenylyl cyclase and regulation of mitogen-activated protein kinase (MAPK) pathways, leading to modulation of transcription. Furthermore, A3 AR affects functions of almost all immune cells and the proliferation of cancer cells. Numerous A3 AR agonists, partial agonists, antagonists, and allosteric modulators have been reported, and their structure-activity relationships (SARs) have been studied culminating in the development of potent and selective molecules with drug-like characteristics. The efficacy of nucleoside agonists may be suppressed to produce antagonists, by structural modification of the ribose moiety. Diverse classes of heterocycles have been discovered as selective A3 AR blockers, although with large species differences. Thus, as a result of intense basic research efforts, the outlook for development of A3 AR modulators for human therapeutics is encouraging. Two prototypical selective agonists, N6-(3-Iodobenzyl)adenosine-5'-N-methyluronamide (IB-MECA; CF101) and 2-chloro-N6-(3-iodobenzyl)-adenosine-5'-N-methyluronamide (Cl-IB-MECA; CF102), have progressed to advanced clinical trials. They were found safe and well tolerated in all preclinical and human clinical studies and showed promising results, particularly in psoriasis and RA, where the A3 AR is both a promising therapeutic target and a biologically predictive marker, suggesting a personalized medicine approach. Targeting the A3 AR may pave the way for safe and efficacious treatments for patient populations affected by inflammatory diseases, cancer, and other conditions.

Related Concept Videos
 01:31
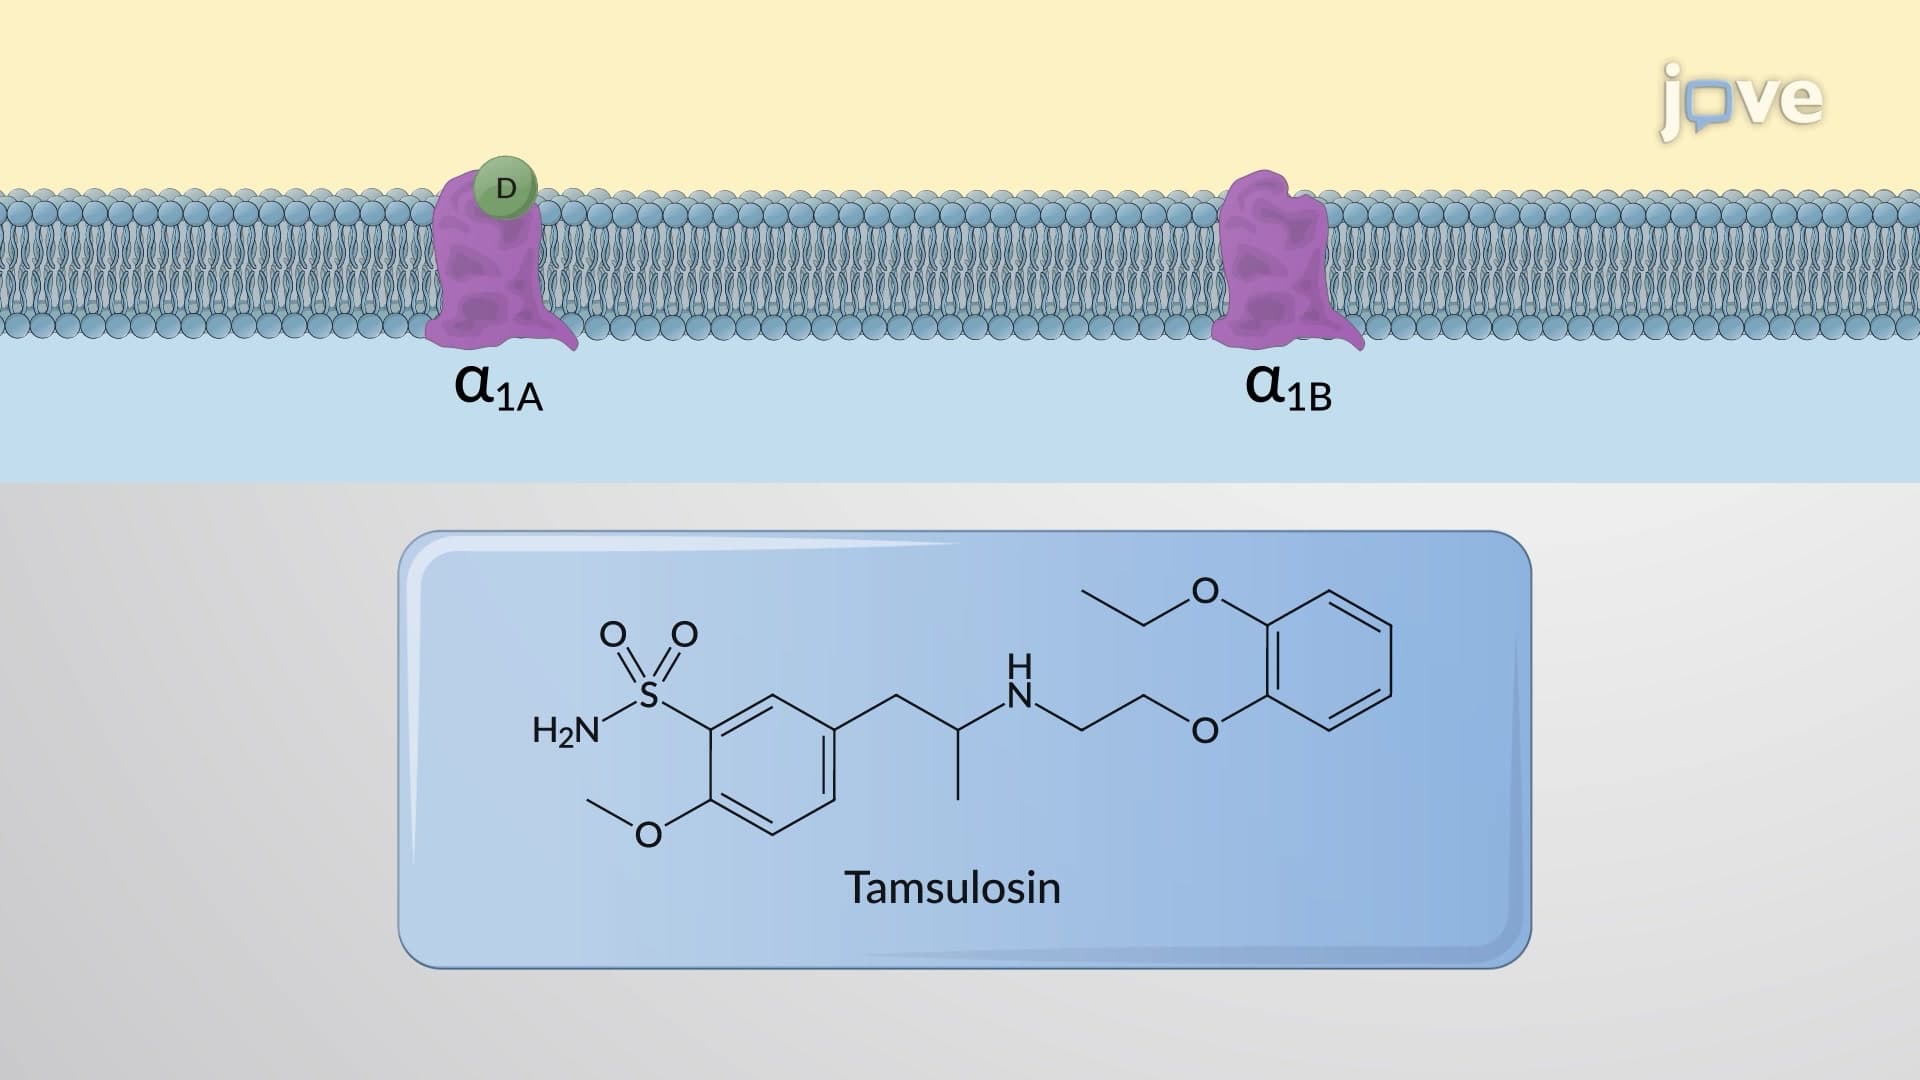
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:17
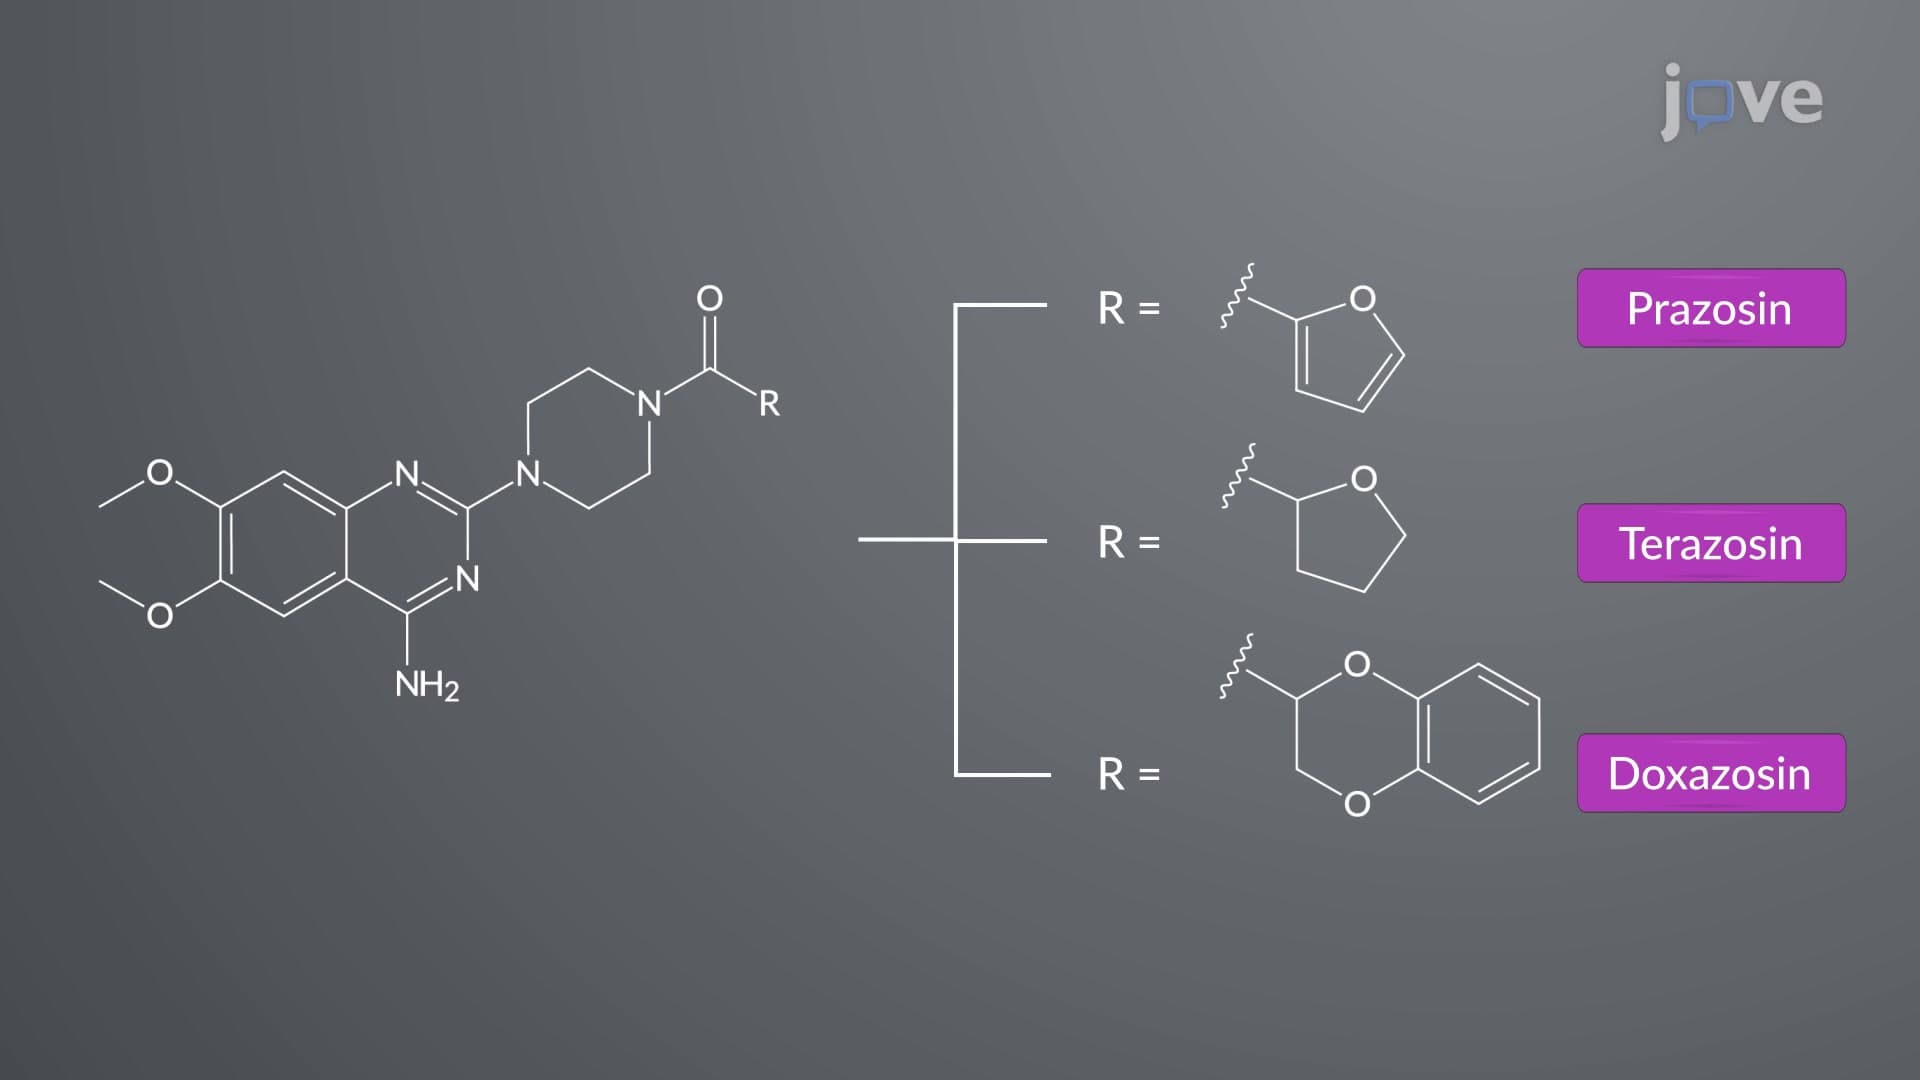
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline...
 01:16
Adrenergic Agonists: Chemistry and Structure-Activity Relationship
Aromatic ring substitutions: Substituting the aromatic ring with –OH groups at positions 3 and 4 yields catecholamines (e.g., epinephrine), which have a high affinity for adrenoceptors. Hydrogen bonding between –OH groups and receptors enhances adrenergic activity.
Separation of...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors,...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...