Related Experiment Video
Updated: Feb 27, 2026


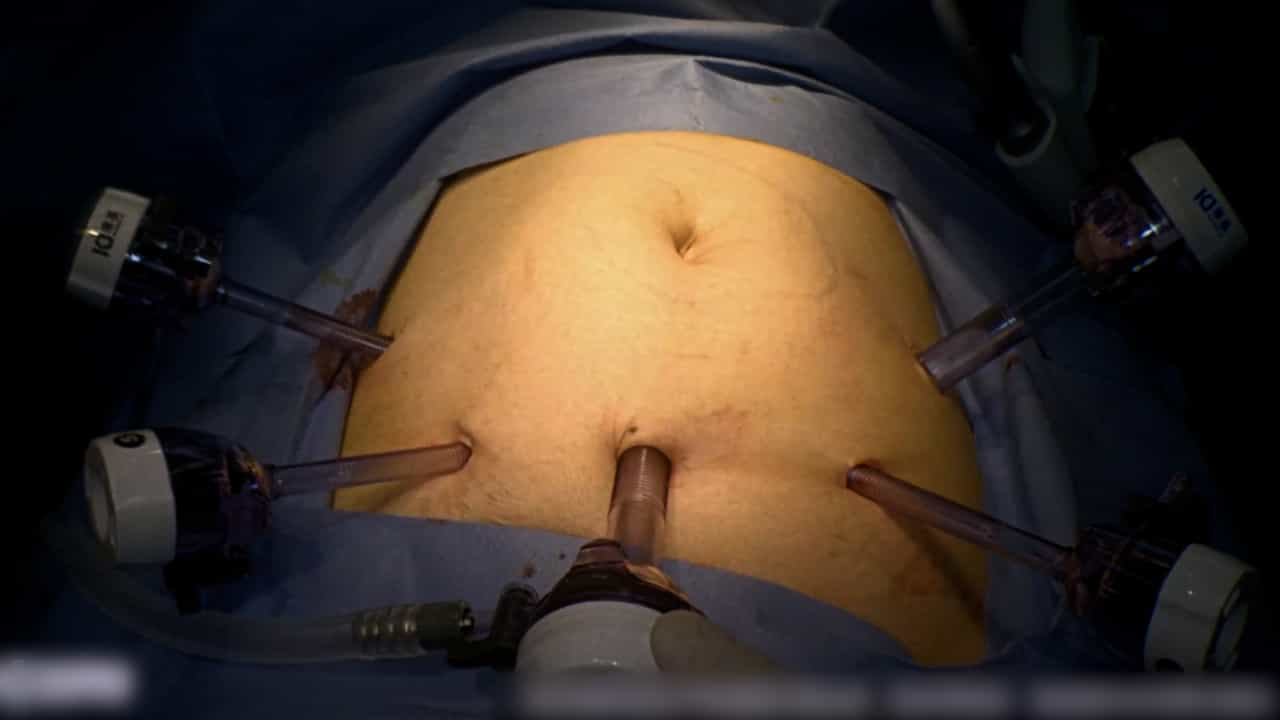
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
Subtotal Colectomy for Colon Cancer Reduces the Need for Subsequent Surgery in Lynch Syndrome
Laura Renkonen-Sinisalo1, Toni T Seppälä, Heikki J Järvinen
11 Department of Gastrointestinal Surgery, Helsinki University Hospital, University of Helsinki, Helsinki, Finland 2 Research Programs Unit, Genome-Scale Biology, University of Helsinki, Helsinki, Finland 3 Department of Education and Science, Central Finland Health Care District, Jyväskylä Finland and University of Eastern Finland, Finland.

Background:
The risk of metachronous colorectal cancer is high after surgical resection for first colon cancer in Lynch syndrome.
Objective:
This study aimed to examine whether extended surgery decreases the risk of subsequent colorectal cancer and improves long-term survival.
Design:
This was a retrospective study.
Setting:
Data were collected from a nationwide registry.
Patients:
Two hundred forty-two Lynch syndrome pathogenic variant carriers who underwent surgery for a first colon cancer from 1984 to 2009 were included.
Interventions:
Patients underwent standard segmental colectomy (n = 144) or extended colectomy (n = 98) for colon cancer. Patients were followed a median of 14.6 up to 25 years.
Main Outcome Measures:
Risk of subsequent colorectal cancer in either group, overall and disease-specific survival, and operative mortality were the primary outcomes measured.
Results:
Subtotal colectomy decreased the risk of subsequent colorectal cancer (HR, 0.20; 95% CI, 0.08-0.52; p = 0.001), compared with segmental resection. Subsequent colorectal cancer decreased in MLH1 carriers. The MSH2 carriers showed no statistical difference, possibly because of their small number. Disease-specific and overall survival within 25 years did not differ between the standard and extended surgeries (82.7% vs 87.2%, p = 0.76 and 47.2% vs 41.4%, p = 0.83). The cumulative risk of subsequent colorectal cancer was 20% in 10 years and 47% within 25 years after standard resection and 4% and 9% after extended surgery. The cumulative risk of metachronous colorectal cancer was 7% within 25 years after subtotal colectomy with ileosigmoidal anastomosis. One patient died of postoperative septicemia within 30 days after segmental colectomy.
Limitations:
Data on surgical procedures were primarily collected retrospectively.
Conclusions:
Lynch syndrome pathogenic variant carriers may undergo subtotal colectomy to manage first colon cancer and avoid repetitive abdominal surgery and to reduce the remaining bowel to facilitate easier endoscopic surveillance. It provides no survival benefit, compared with segmental colon resection. See Video Abstract at http://links.lww.com/DCR/A319.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...