Related Experiment Video
Updated: Feb 27, 2026


Modified Octopus Technique for Thoracoabdominal Aortic Aneurysm
Published on: August 1, 2025
Central cannulation strategy for extent I thoracoabdominal aneurysm repair of chronic type B aortic dissection
Reilly D Hobbs1, Tyler J Wallen1, Caroline M Komlo1
1Department of Cardiovascular Surgery, Hospital of the University of Pennsylvania, Philadelphia, Pennsylvania.

Insights
Central aortic cannulation for thoracoabdominal aortic aneurysm repair is a safe alternative to peripheral femoral cannulation. This approach offers comparable early and midterm outcomes, making it a viable option for patients with compromised femoral vessels.
Area of Science:
- Cardiovascular Surgery
- Thoracic Surgery
- Aortic Surgery
Background:
- Thoracoabdominal aortic aneurysms (TAAA) with chronic type B dissection present complex surgical challenges.
- Traditional cardiopulmonary bypass (CPB) cannulation strategies often involve peripheral femoral vessels.
- Evaluating alternative cannulation sites is crucial for improving patient outcomes.
Purpose of the Study:
- To compare the safety and efficacy of central aortic cannulation versus peripheral femoral cannulation for extent I TAAA repair in patients with chronic type B dissection.
Main Methods:
- Retrospective review of patients undergoing extent I TAAA repair from 2002-2011.
- Group I: Central aortic cannulation via left thoracotomy (n=28).
- Group II: Peripheral femoral cannulation (n=31).
- Both groups underwent deep hypothermic circulatory arrest.
Main Results:
- Preoperative aortic dimensions were similar between groups.
- Central cannulation (Group I) had significantly longer CPB times (240±37 min vs 174±68 min).
- Early and midterm outcomes including mortality, stroke, paraplegia, reoperation for bleeding, tracheostomy rates, and length of stay were similar between groups.
- 5-year actuarial survival was 84.6% for Group I and 77.6% for Group II (p=0.52).
Conclusions:
- Central true lumen cannulation is an acceptable and safe alternative for extent I TAAA repair in chronic type B dissection.
- This technique offers equivalent early and midterm outcomes compared to standard femoral cannulation.
- It provides a valuable alternative for patients with diseased femoral vessels.
Introduction:
We evaluated the safety profile of a central cardiopulmonary bypass (CPB) cannulation strategy for repair of extent I thoracoabdominal aortic aneurysms (TAAA) with chronic type B dissection in comparison to traditional peripheral CPB cannulation strategies.
Methods:
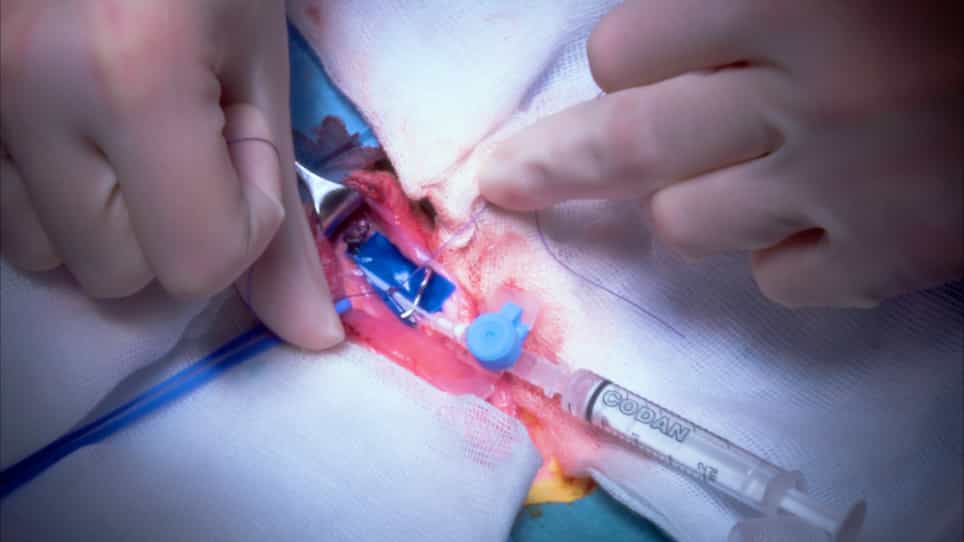
Patients undergoing extent I TAAA repair for chronic type B dissection from 2002 to 2011 were retrospectively reviewed. Patients were grouped by their CPB cannulation strategy. Patients in Group I underwent central aortic cannulation (n = 28) through a left thoracotomy incision. The true lumen of the descending thoracic aorta was cannulated using an echocardiogram-guided Seldinger wire technique. The right atrium was directly accessed for venous drainage. In Group II (n = 31), arterial and venous cannulation of the femoral vessels was achieved using a left-sided groin incision. All patients underwent deep hypothermic circulatory arrest for proximal aortic reconstruction.
Results:
Preoperative aortic dimensions (6.5 ± 0.79 cm in Group I vs 7.0 ± 1.15 cm in Group II p = 0.8) were similar between groups. CPB time (240 ± 37 min in Group I vs 174 ± 68 min in Group II p < 0.01) was significantly higher in the central cannulation group whereas circulatory arrest times (43 ± 5 min Group I vs 37 ± 7 min in Group II p = 0.1) were similar between the two groups. In-hospital 30-day mortality (N = 0, 0% in Group I; N = 2, 6.5% in Group II), stroke (N = 1, 3.5% in Group I; N = 0, 0% in Group II), paraplegia (N = 1, 3.5% in Group I; N = 1, 3.2% in Group II), reoperation for bleeding (N = 1, 3.5% in Group I; N = 1, 3.2% Group II), tracheostomy rate (N = 2, 7% in Group I; N = 3, 9.7% Group II), and mean length of stay (19 days in Group I vs 17 days in Group II) were similar (p > 0.05). Median follow-up was 3.6 ± 2.0 in Group I and 5.6 ± 2.6 years in Group II. Actuarial survival at 5 years was 84.6 % for Group I and 77.6% for Group II (p = 0.52).
Conclusions:
Central true lumen cannulation through a left thoracotomy incision for repair of extent I TAAA with chronic type B dissection is an acceptable approach with equivalent early and midterm outcomes compared to more standard femoral cannulation techniques. It may provide a safe alternative cannulation site for patients with diseased femoral vessels.

Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management