Related Experiment Video
Updated: Feb 26, 2026
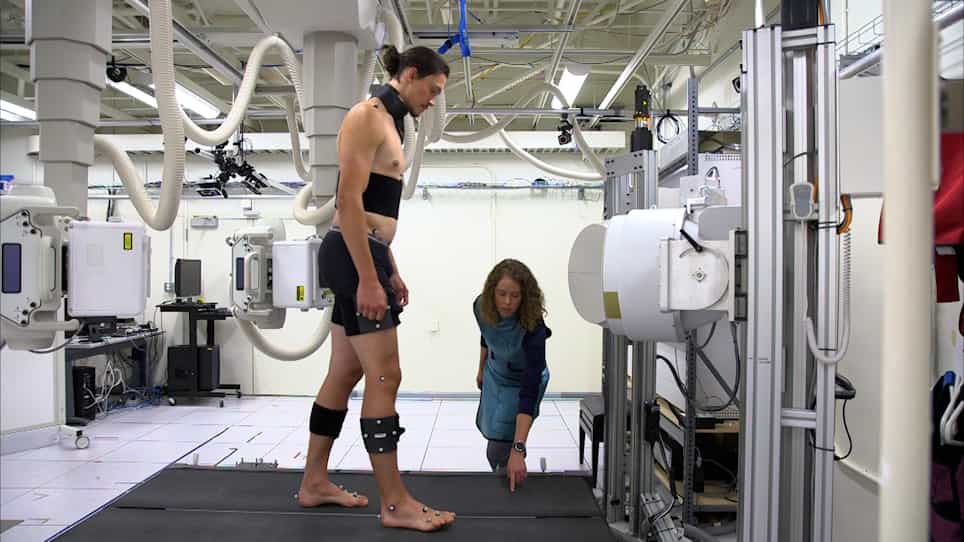
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Range of Hip Joint Motion Is Correlated With MRI-Verified Cam Deformity in Adolescent Elite Skiers
Cecilia Agnvall1, Anna Swärd Aminoff2, Carl Todd3
1Sportsmedicine Åre and Åre Ski High School, Åre, Sweden.

Background:
Radiologically verified cam-type femoroacetabular impingement (FAI) has been shown to correlate with reduced internal rotation, reduced passive hip flexion, and a positive anterior impingement test.
Purpose:
To validate how a clinical examination of the hip joint correlates with magnetic resonance imaging (MRI)-verified cam deformity in adolescents.
Study Design:
Cross-sectional study; Level of evidence, 3.
Methods:
The sample group consisted of 102 adolescents with the mean age 17.7 ± 1.4 years. The hip joints were examined using MRI for measurements of the presence of cam (α-angle ≥55°) and clinically for range of motion (ROM) in both supine and sitting positions. The participants were divided into a cam and a noncam group based on the results of the MRI examination. Passive hip flexion, internal rotation, anterior impingement, and the FABER (flexion, abduction, and external rotation) test were used to test both hips in the supine position. With the participant sitting, the internal/external rotation of the hip joint was measured in 3 different positions of the pelvis (neutral, maximum anteversion, and retroversion) and lumbar spine (neutral, maximum extension, and flexion).
Results:
Differences were found between the cam and noncam groups in terms of the anterior impingement test (right, P = .010; left, P = .006), passive supine hip flexion (right: mean, 5°; cam, 117°; noncam, 122° [P = .05]; and left: mean, 8.5°; cam, 116°; noncam, 124.5° [P = .001]), supine internal rotation (right: mean, 4.9°; cam, 24°; noncam, 29° [P = .022]; and left: mean, 4.8°; cam, 26°; noncam, 31° [P = .028]), sitting internal rotation with the pelvis and lumbar spine in neutral (right: mean, 7.95°; cam, 29°; noncam, 37° [P = .001]; and left: mean, 6.5°; cam, 31.5°; noncam, 38° [P = .006]), maximum anteversion of the pelvis and extension of the lumbar spine (right: mean, 5.2°; cam, 20°; noncam, 25° [P = .004]; and left: mean, 5.85°; cam, 20.5; noncam, 26.4° [P = .004]), and maximum retroversion of the pelvis and flexion of the spine (right: mean, 8.4°; cam, 32.5°; noncam, 41° [P = .001]; and left: mean, 6.2°; cam, 36°; noncam, 42.3° [P = .012]). The cam group had reduced ROM compared with the noncam group in all clinical ROM measures.
Conclusion:
The presence of cam deformity on MRI correlates with reduced internal rotation in the supine and sitting positions, passive supine hip flexion, and the impingement test in adolescents.

Related Concept Videos
 01:10
Ankle Joint
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:16
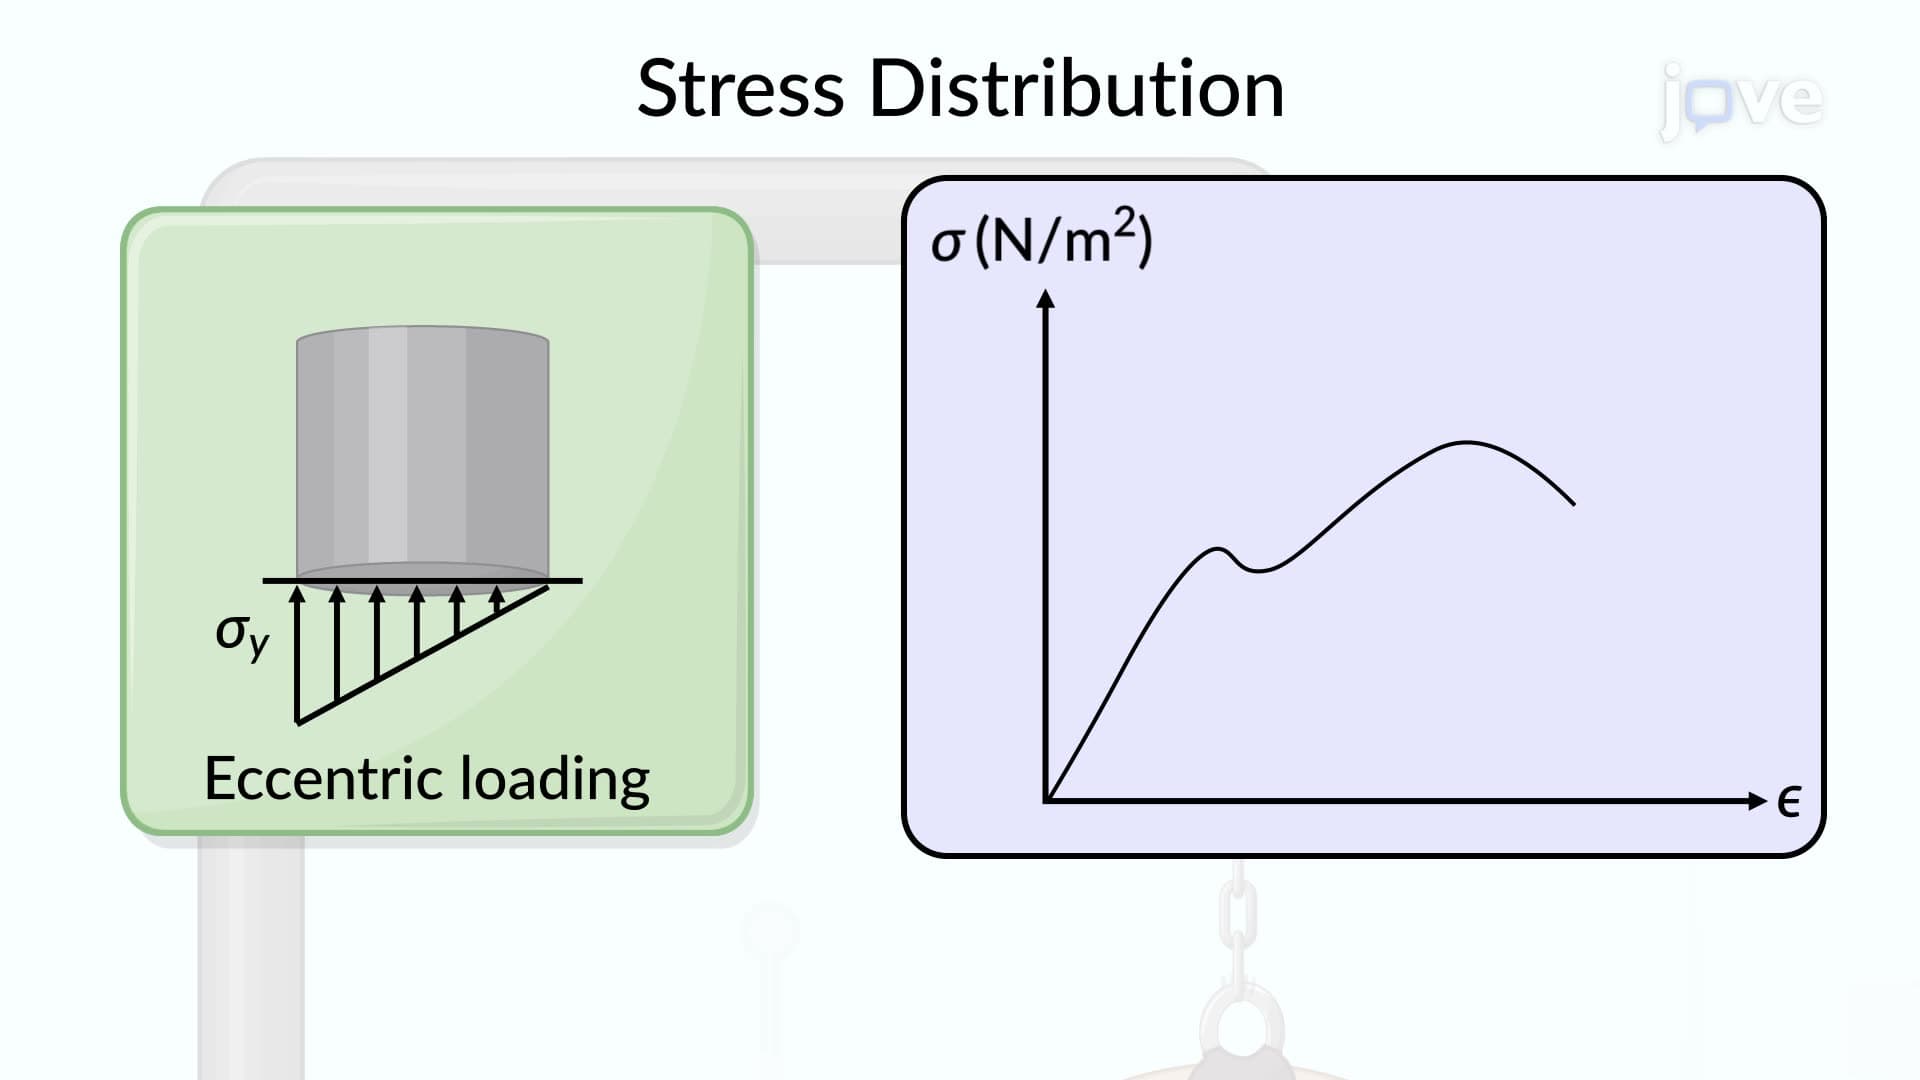
Eccentric Axial Loading in a Plane of Symmetry
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:07
Development of the Limb Synovial Joints
The mesenchymal stem cells differentiate into chondrocytes that form the hyaline cartilage, and later the cartilaginous model of the bone. This model further transforms into a bone. This process is known as endochondral ossification.
During development, the limbs...
 00:51
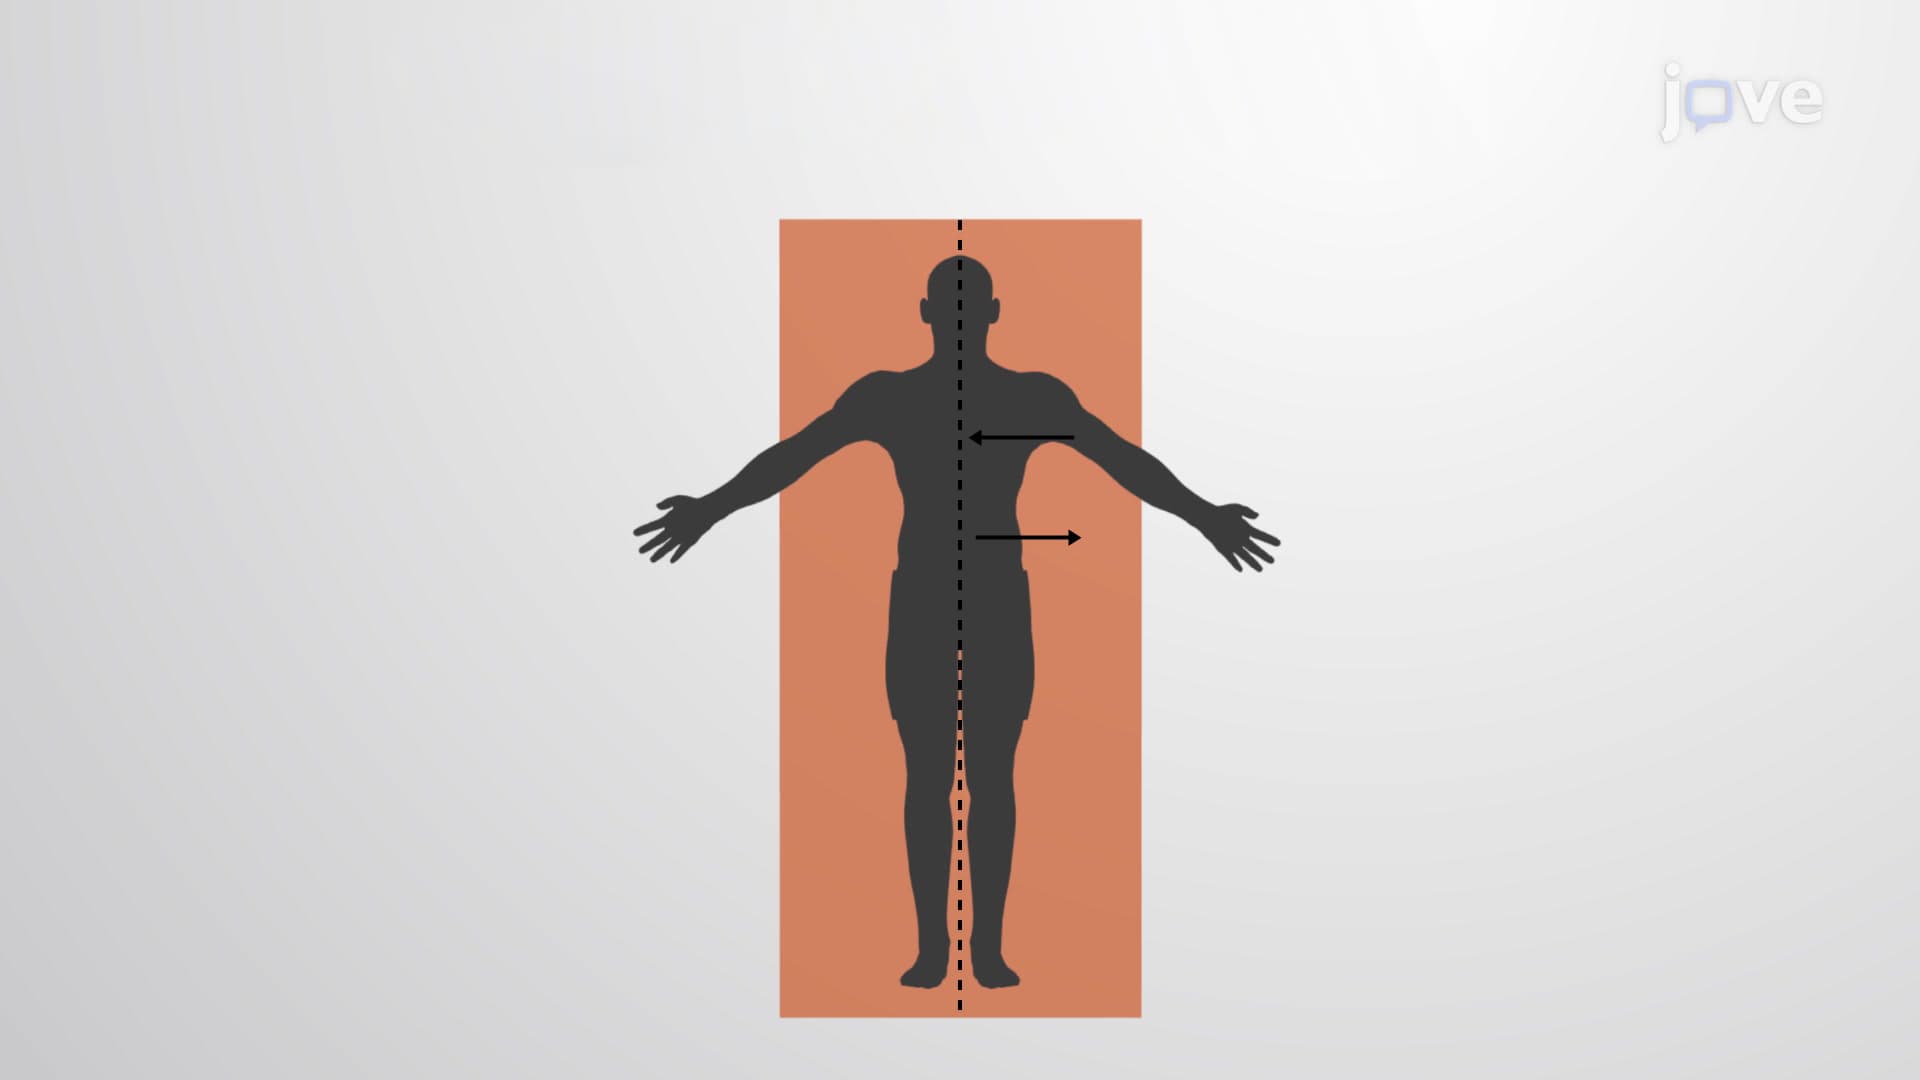
Anatomical Movements
Here are some common anatomical movements:
Flexion and extension motions are in the sagittal (anterior–posterior) plane of motion. These movements take place at the shoulder, hip, elbow, knee, wrist,...