Related Experiment Video
Updated: Feb 26, 2026
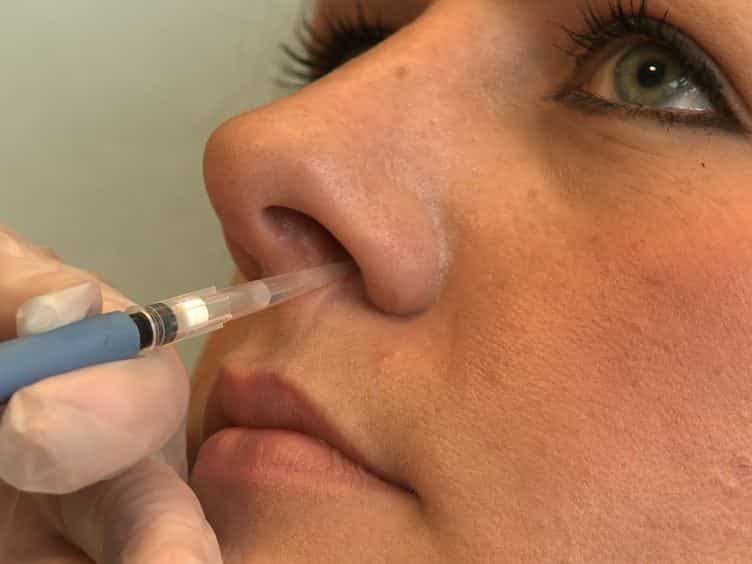

Experimental Human Pneumococcal Carriage
Published on: February 15, 2013
Carrier priming to improve pneumococcal disease control and reduce the international program's cost in children
Mohamed Tashani1,2,3, Harunor Rashid1,2,3,4, Kim Mulholland5,6
1National Centre for Immunisation Research and Surveillance (NCIRS), The Children's Hospital at Westmead, Sydney, NSW Australia.

Insights
Sequential administration of diphtheria-toxoid-containing vaccines (DTP) before pneumococcal conjugate vaccine (PCV) may enhance PCV immunogenicity. This carrier priming phenomenon could improve vaccine effectiveness and reduce costs in developing nations.
Area of Science:
- Immunology
- Vaccinology
- Public Health
Background:
- Pneumococcal conjugate vaccines (PCV) may interact with diphtheria toxin-like antigen vaccines (e.g., DTP).
- This interaction stems from the similarity between diphtheria toxoid and the carrier protein (CRM197) in PCV.
Discussion:
- Sequential administration, specifically DTP before PCV, can induce "carrier priming."
- Carrier priming enhances the immunogenicity of PCV due to antigen similarity.
Key Insights:
- Carrier priming offers a strategy to boost PCV immunogenicity.
- This phenomenon can potentially reduce the number of PCV doses needed.
- Enhanced immunogenicity can lead to more cost-effective immunization programs.
Outlook:
- Implementing carrier priming in immunization schedules could benefit developing countries.
- Vulnerable populations may experience improved vaccine responses.
- Further research can optimize sequential vaccination strategies for global health.
Abstract:
Pneumococcal conjugate vaccine (PCV) has the potential to interact with other vaccines containing diphtheria toxin-like antigens (such as those found in the DTP vaccine) upon sequential administration. This is attributed to the similarity of the diphtheria toxoid antigen to the carrier protein used to make PCV, (known as cross reactive material [CRM]) to diphtheria toxin 197 or CRM197. The interaction could lead to enhanced immunogenicity of PCV as a result of a phenomenon called carrier priming, whereby DTP is given some weeks before the first dose of PCV. This phenomenon could be implemented in the immunisation schedule in developing countries and among vulnerable populations to enhance the immunogenicity of PCV, reduce the number of doses required, and produce a more cost-effective immunisation program in developing countries.
More Related Videos

Related Concept Videos
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 01:29
Drug Dosing: Infants and Children
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...