Related Experiment Video
Updated: Feb 26, 2026
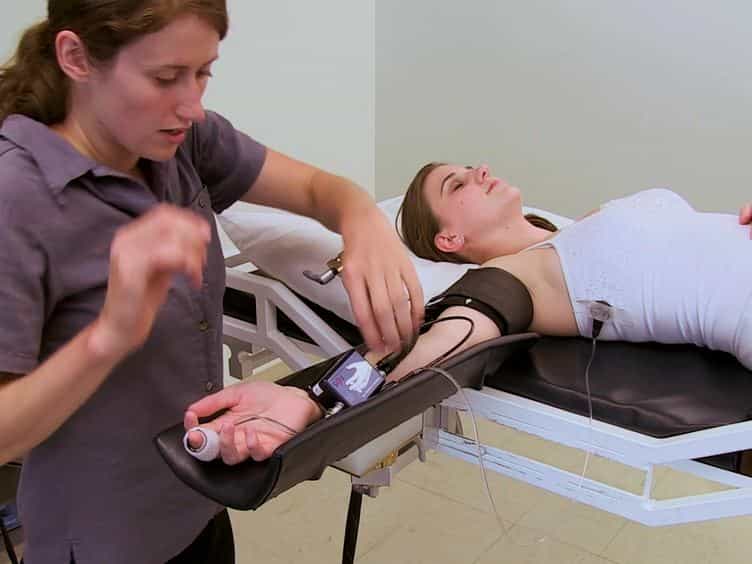

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Management of Supine Hypertension Complicating Neurogenic Orthostatic Hypotension
Jacquie Baker1,2, Kurt Kimpinski3,4,5
1School of Kinesiology, Western University, London, ON, Canada.

Abstract:
Neurogenic orthostatic hypotension (NOH) can be present in a number of disorders, including synucleinopathies, autoimmune disorders, and various genetic disorders. All are characterized by defective norepinephrine release from sympathetic terminals upon standing, resulting in impaired vasoconstriction. NOH is defined as a drop in systolic blood pressure ≥20 mmHg or diastolic blood pressure ≥10 mmHg, or both, within 3 minutes of standing or head up-tilt at a minimum of 60°. However, approximately 50% of patients have associated supine hypertension, which greatly complicates treatment. Supine hypertension not only is a common side effect of many anti-hypotensive agents but is also present in untreated patients, suggesting it is, in part, innate to the pathophysiology of autonomic dysfunction. Pathological mechanisms differ depending on the underlying autonomic disorder. In central neurodegenerative disorders, residual post-ganglionic sympathetic activity is likely the primary mechanism, whereas plasma angiotensin, aldosterone, and inappropriate mineralocorticoid receptor activity may contribute in peripheral autonomic lesions. Baroreflex failure/loss of baroreflex buffering is common to both. More work is required. Clinically, there is much dispute regarding the treatment of supine hypertension when there is a risk of exacerbating orthostatic hypotension. However, given the similar levels of end-organ damage (i.e., heart attack and stroke) seen with transient hypertension, it seems clear that treatment is important. Current therapies for both NOH and supine hypertension include a combination of pharmacological and conservative measures. However, in addition to the current standard of care, protocols may consider 24-h blood pressure monitoring and potential future examination of the peripheral post-ganglionic sympathetic nerves in order to apply individualized adjunct therapies. Finally, no anti-hypertensive agents are currently approved for use in this patient population, and development of novel therapies should focus on short-acting agents, selective to the supine position, that act primarily at night when hypertension is most severe/prolonged.
Related Concept Videos
 01:23
Hypertension V: Nursing Management
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:18
Neural Regulation of Blood Pressure
Baroreceptor Reflex
Baroreceptors, located in the carotid sinuses and aortic arch, detect changes in blood pressure. When blood pressure rises, these stretch-sensitive receptors...
 01:23
Antihypertensive Drugs: Vasodilators
 01:30
Heart Failure V: Medical Management