Related Experiment Video
Updated: Feb 26, 2026

Measuring Ascending Aortic Stiffness In Vivo in Mice Using Ultrasound
Published on: December 2, 2014
Temporal relationship between instantaneous pressure gradients and peak-to-peak systolic ejection gradient in
Brian A Boe1, Mark D Norris2, Jeffrey D Zampi2
1Nationwide Children's Hospital, The Heart Center, Columbus, Ohio, USA.

Insights
For congenital aortic stenosis, instantaneous pressure gradient (IPG) measured mid-ejection (50%-55%) best estimates peak-to-peak systolic ejection gradient (PPSG). This finding improves noninvasive assessment accuracy for this condition.
Area of Science:
- Cardiology
- Medical Imaging
- Hemodynamics
Background:
- Noninvasive echocardiography of instantaneous pressure gradient (IPG) has limited correlation with cardiac catheterization-derived peak-to-peak systolic ejection gradient (PPSG) in congenital aortic stenosis.
- The discrepancy arises from inherent differences and variable relationships dependent on stenosis severity.
Purpose of the Study:
- To identify the specific time point during cardiac ejection where IPG most accurately correlates with PPSG in patients with congenital aortic stenosis.
- To improve the noninvasive estimation of PPSG using echocardiographic IPG measurements.
Main Methods:
- Retrospective review of hemodynamic data from cardiac catheterizations in 22 patients with congenital valvar aortic stenosis over 5 years.
- Standardization of the cardiac cycle using percentage of total left ventricular ejection time (ET).
- Comparison of IPG at 5% ET intervals with PPSG using linear regression and Bland-Altman analysis.
Main Results:
- The peak-to-peak systolic ejection gradient (PPSG) was 46.5 ± 12.6 mm Hg.
- Midsystolic IPG (at 50% ET) showed the strongest correlation with PPSG (R² = 0.88).
- IPG at 55% ET demonstrated the closest correlation to unity with PPSG (PPSG = 0.997(IPG55%) - 1.17).
Conclusions:
- Maximum and mean IPG measurements are suboptimal for estimating PPSG in congenital aortic stenosis.
- IPG measured at 50%-55% of ejection time provides a more accurate correlation with PPSG.
- This finding may enable more precise noninvasive assessment of PPSG using echocardiography.
Objective:
We sought to identify a time during cardiac ejection when the instantaneous pressure gradient (IPG) correlated best, and near unity, with peak-to-peak systolic ejection gradient (PPSG) in patients with congenital aortic stenosis. Noninvasive echocardiographic measurement of IPG has limited correlation with cardiac catheterization measured PPSG across the spectrum of disease severity of congenital aortic stenosis. A major contributor is the observation that these measures are inherently different with a variable relationship dependent on the degree of stenosis.
Design:
Hemodynamic data from cardiac catheterizations utilizing simultaneous pressure measurements from the left ventricle (LV) and ascending aorta (AAo) in patients with congenital valvar aortic stenosis was retrospectively reviewed over the past 5 years. The cardiac cycle was standardized for all patients using the percentage of total LV ejection time (ET). Instantaneous gradient at 5% intervals of ET were compared to PPSG using linear regression and Bland-Altman analysis.
Results:
A total of 22 patients underwent catheterization at a median age of 13.7 years (interquartile range [IQR] 10.3-18.0) and median weight of 51.1 kg (IQR 34.2-71.6). The PPSG was 46.5 ± 12.6 mm Hg (mean ± SD) and correlated suboptimally with the maximum and mean IPG. The midsystolic IPG (occurring at 50% of ET) had the strongest correlation with the PPSG ( PPSG = 0.97(IPG50%)-1.12, R2 = 0.88), while the IPG at 55% of ET was closest to unity ( PPSG = 0.997(IPG55%)-1.17, R2 = 0.87).
Conclusions:
The commonly measured maximum and mean IPG are suboptimal estimates of the PPSG in congenital aortic stenosis. Using catheter-based data, IPG at 50%-55% of ejection correlates well with PPSG. This may allow for a more accurate estimation of PPSG via noninvasive assessment of IPG.
More Related Videos
 04:48
Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
 06:51
Author Spotlight: Development of a Minimally Invasive Large-Animal Model for Reliable and Reproducible Cardiovascular Research
Published on: October 20, 2023
Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:20
Mitral Regurgitation I: Introduction
 01:25
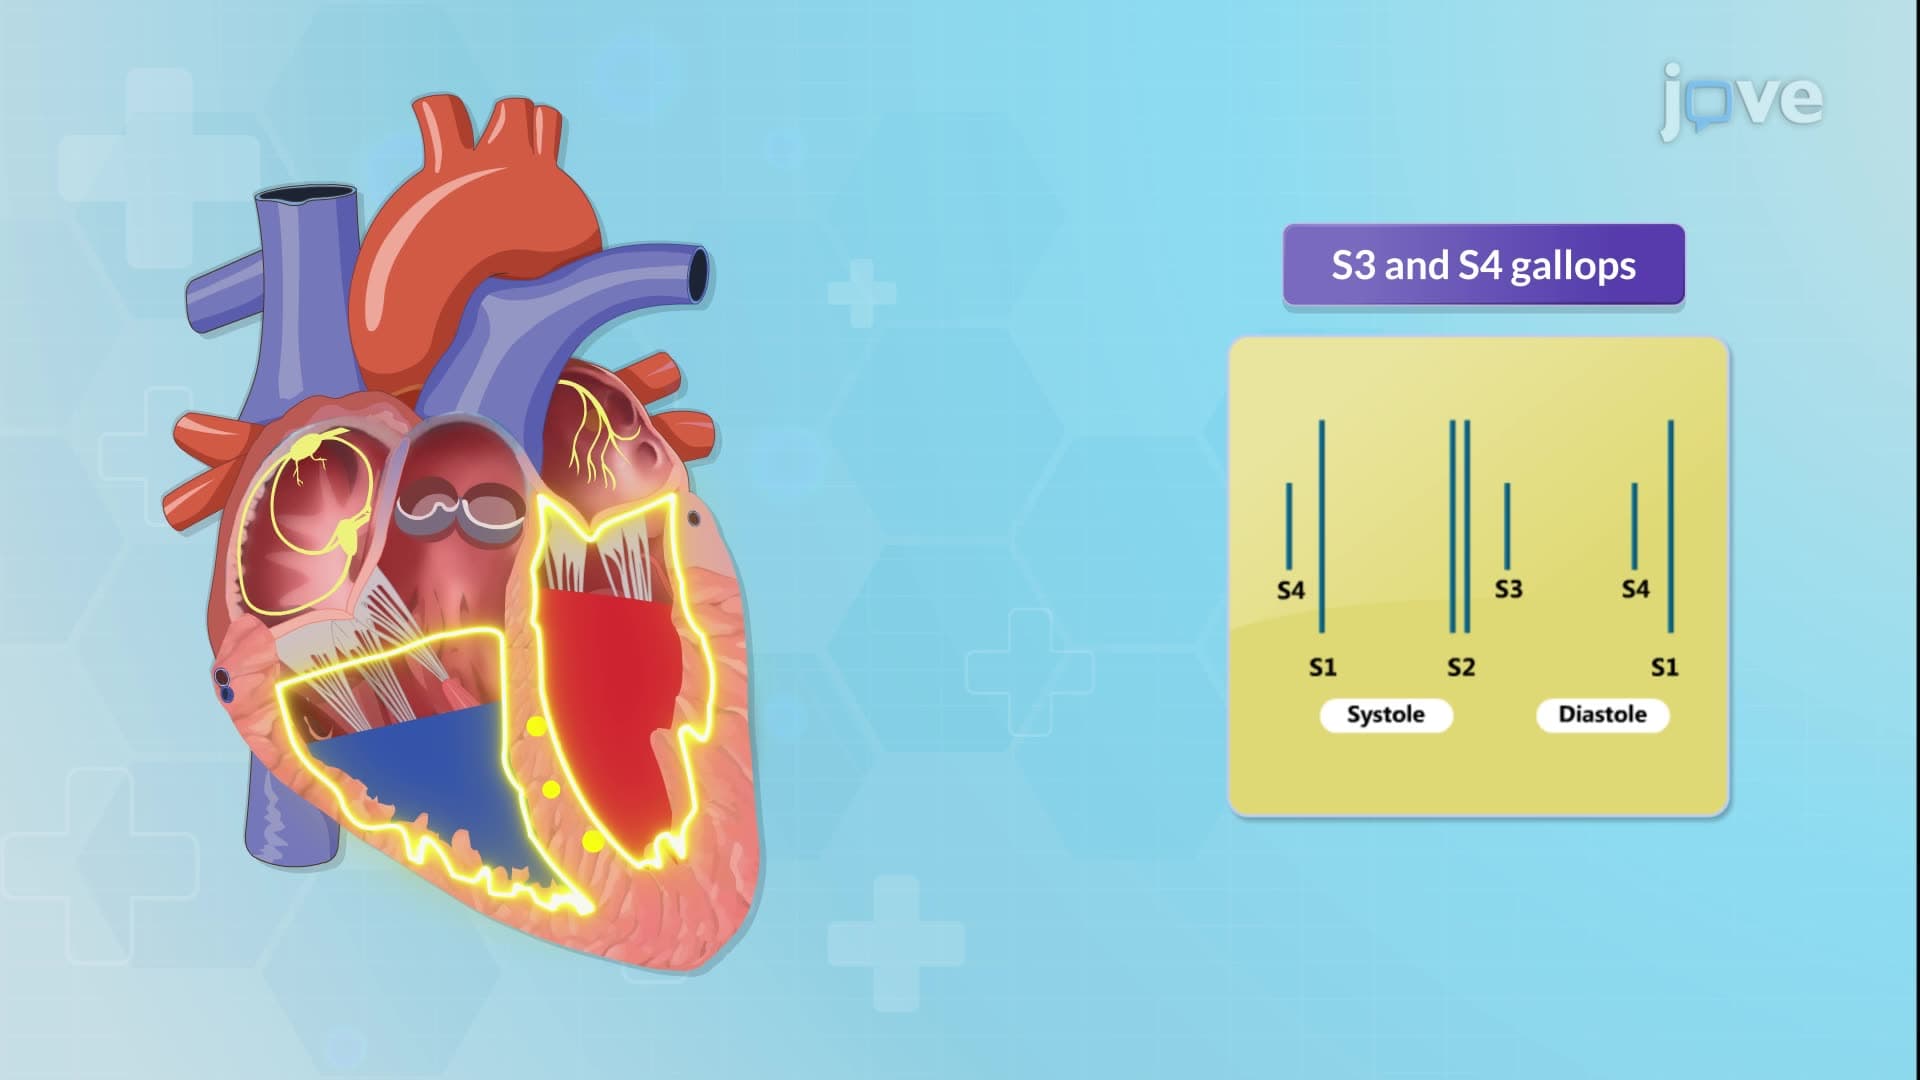
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops: