Related Experiment Video
Updated: Feb 26, 2026
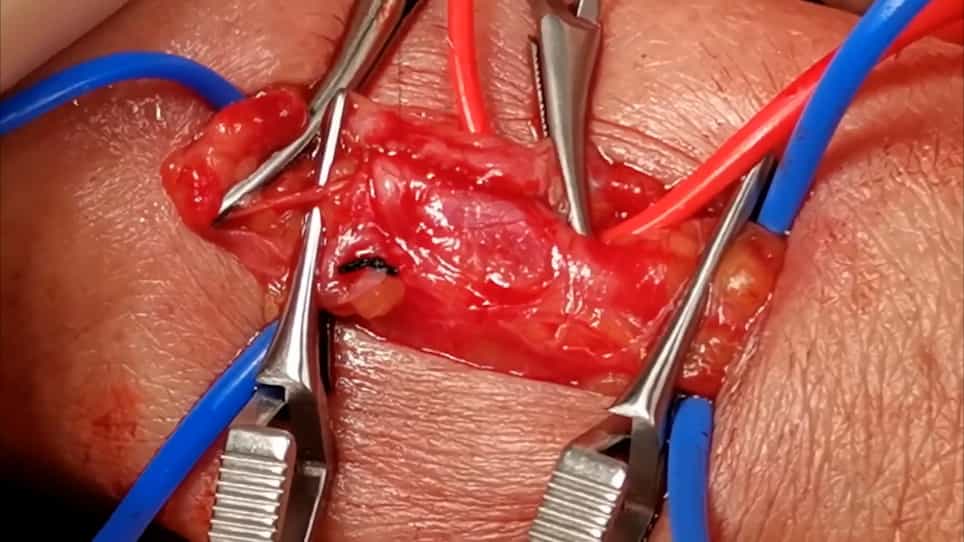
Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Brachial vein transposition is a promising ultimate upper limb autologous arteriovenous angioaccess despite its many
Lamisse Karam1, Marek Rawa2, Richard Shoenfeld3
1Vascular Surgery Department, Notre Dame de Secours Hospital, Byblos, Lebanon.

Objective:
The objective of this study was to retrospectively evaluate the possibility of using the brachial veins despite their deep location, small caliber, and thin wall.
Methods:
There were 64 patients without superficial veins who were eligible for two-stage brachial vein transposition (BrVT); 54 patients were on hemodialysis, 9 patients had sickle cell disease, and 1 patient had long-term parenteral nutrition. Preoperative imaging was performed with color duplex ultrasound as well as venography for suspected central vein stenosis. A surgical microscope was used to create an end-to-side anastomosis between the brachial vein (medial, if possible) and artery. No minimum vein diameter was required. Postoperative color duplex ultrasound imaging was scheduled at 1 month. Second-stage superficialization was performed 2 to 3 months later with tunnelization and a new arteriovenous anastomosis.
Results:
For the 64 patients, cumulative primary patency rates (± standard deviation [SD]) at 1 year, 2 years, 3 years, and 4 years were 50% (±7%), 42% (±7%), 37% (±8%), and 27% (±11%), respectively. Primary assisted patency rates (±SD) at 1 year, 2 years, 3 years, and 4 years were 60% (±6%), 51% (±7%), 45% (±7%), and 37% (±9%), respectively. Secondary patency rates (±SD) at 1 year, 2 years, 3 years, and 4 years were 60% (±6%), 53% (±7%), 53% (±7%), and 45% (±8%), respectively. Early complications included thrombosis, nonmaturation, and upper arm edema. At the second stage (n = 50), four patients presented with unexplained major fibrosis extending cephalad from the first surgical site and preventing any dissection of the vein. Four patients had more usual complications (one nonmaturation, two occlusions of the brachial vein at the previous arteriovenous graft-vein anastomosis), and two were lost to follow-up. Vein transposition in a subcutaneous tunnel was technically unfeasible in eight patients. Of the 64 patients, 40 (62%) had a functional BrVT that was cannulated for effective dialysis after a median interval of 72 days (15-420 days) from the first stage. Mean cumulative secondary patency rates (from first cannulation) at 1 year, 2 years, and 3 years were 91% ± 5%, 72% ± 8%, and 62% ± 10%, respectively. Overall, 13 patients were lost to follow-up. Secondary complications were low flow and central vein occlusion. Long-term complications were related to stenosis and thrombosis, aneurysms, and puncture site necrosis. Median follow-up from the first stage was 1.62 years (0.02-11.3 years).
Conclusions:
Despite many pitfalls for the surgeon, BrVT offers promising long-term patency.

Related Concept Videos
 01:17
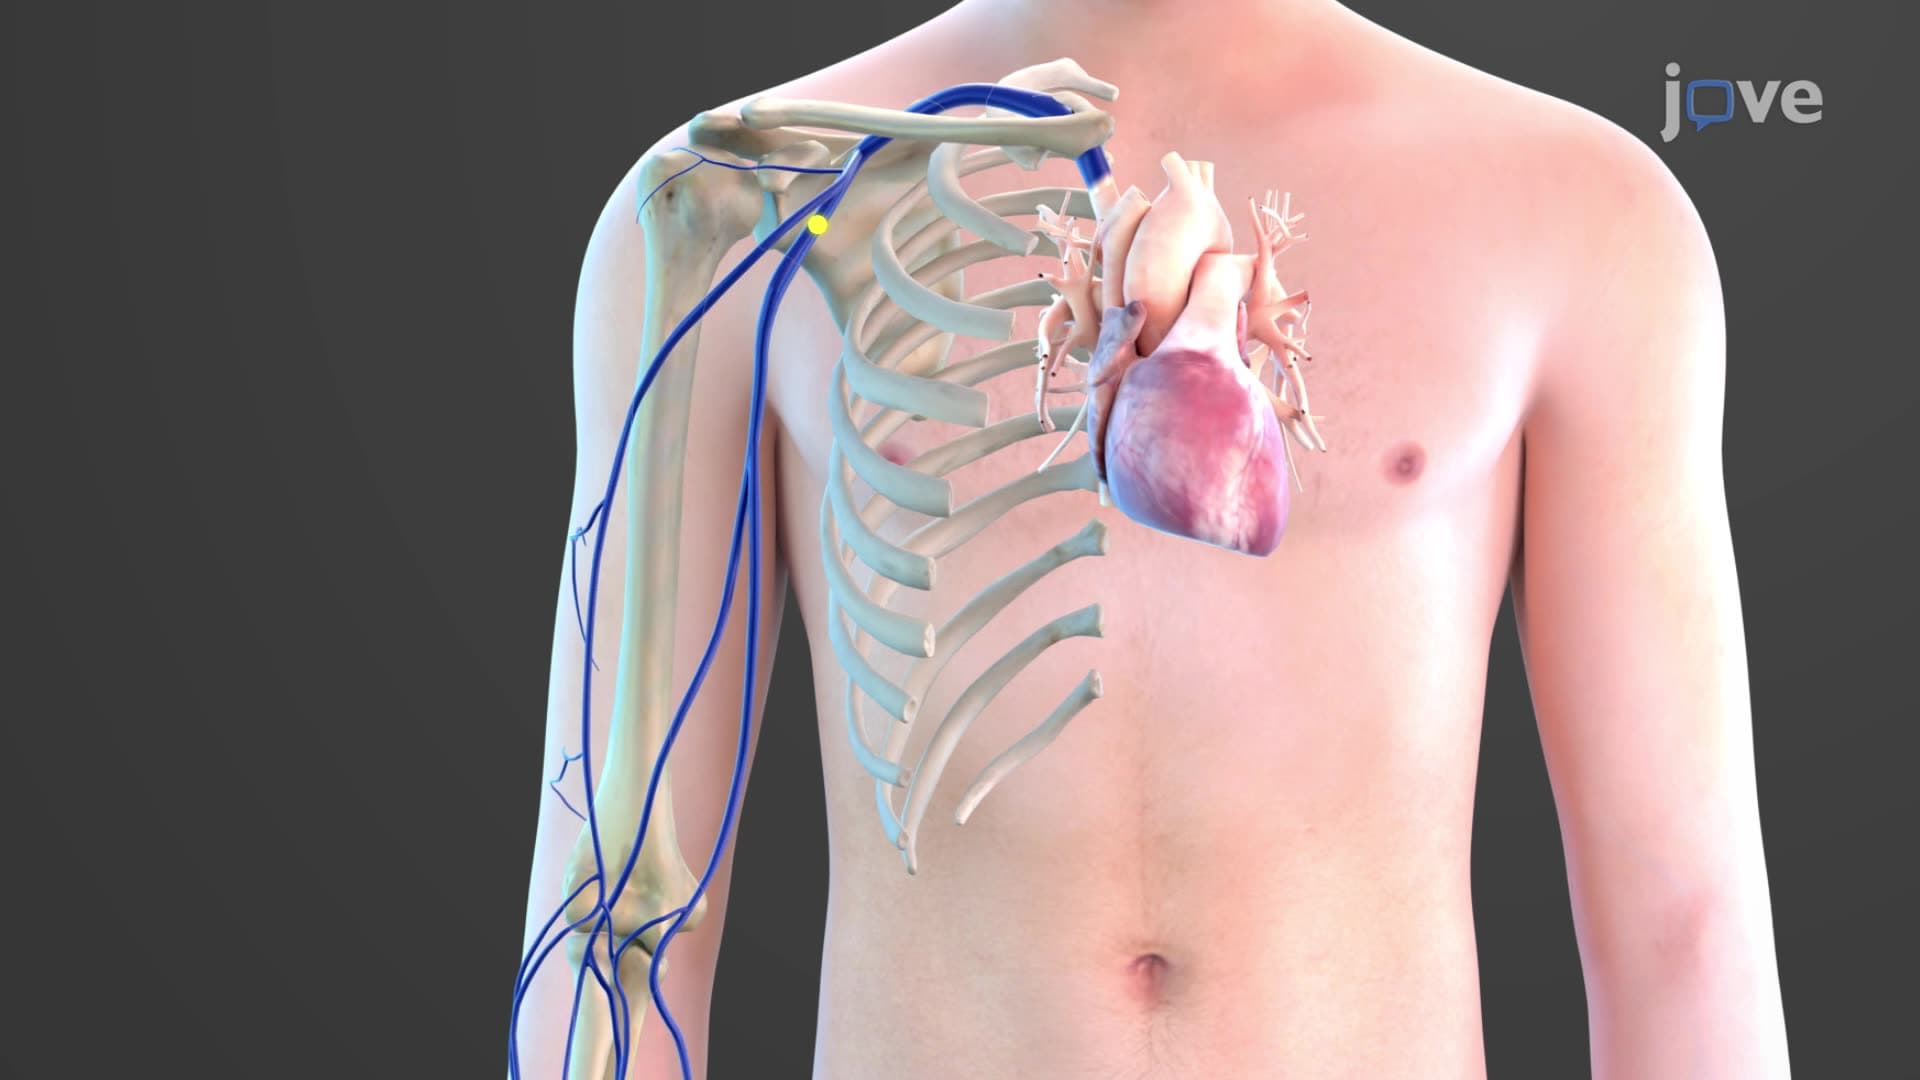
Veins of Upper Limbs
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...
 01:25
Hemodialysis I: Introduction
 01:12
Arteries of the Upper Limbs
 01:19
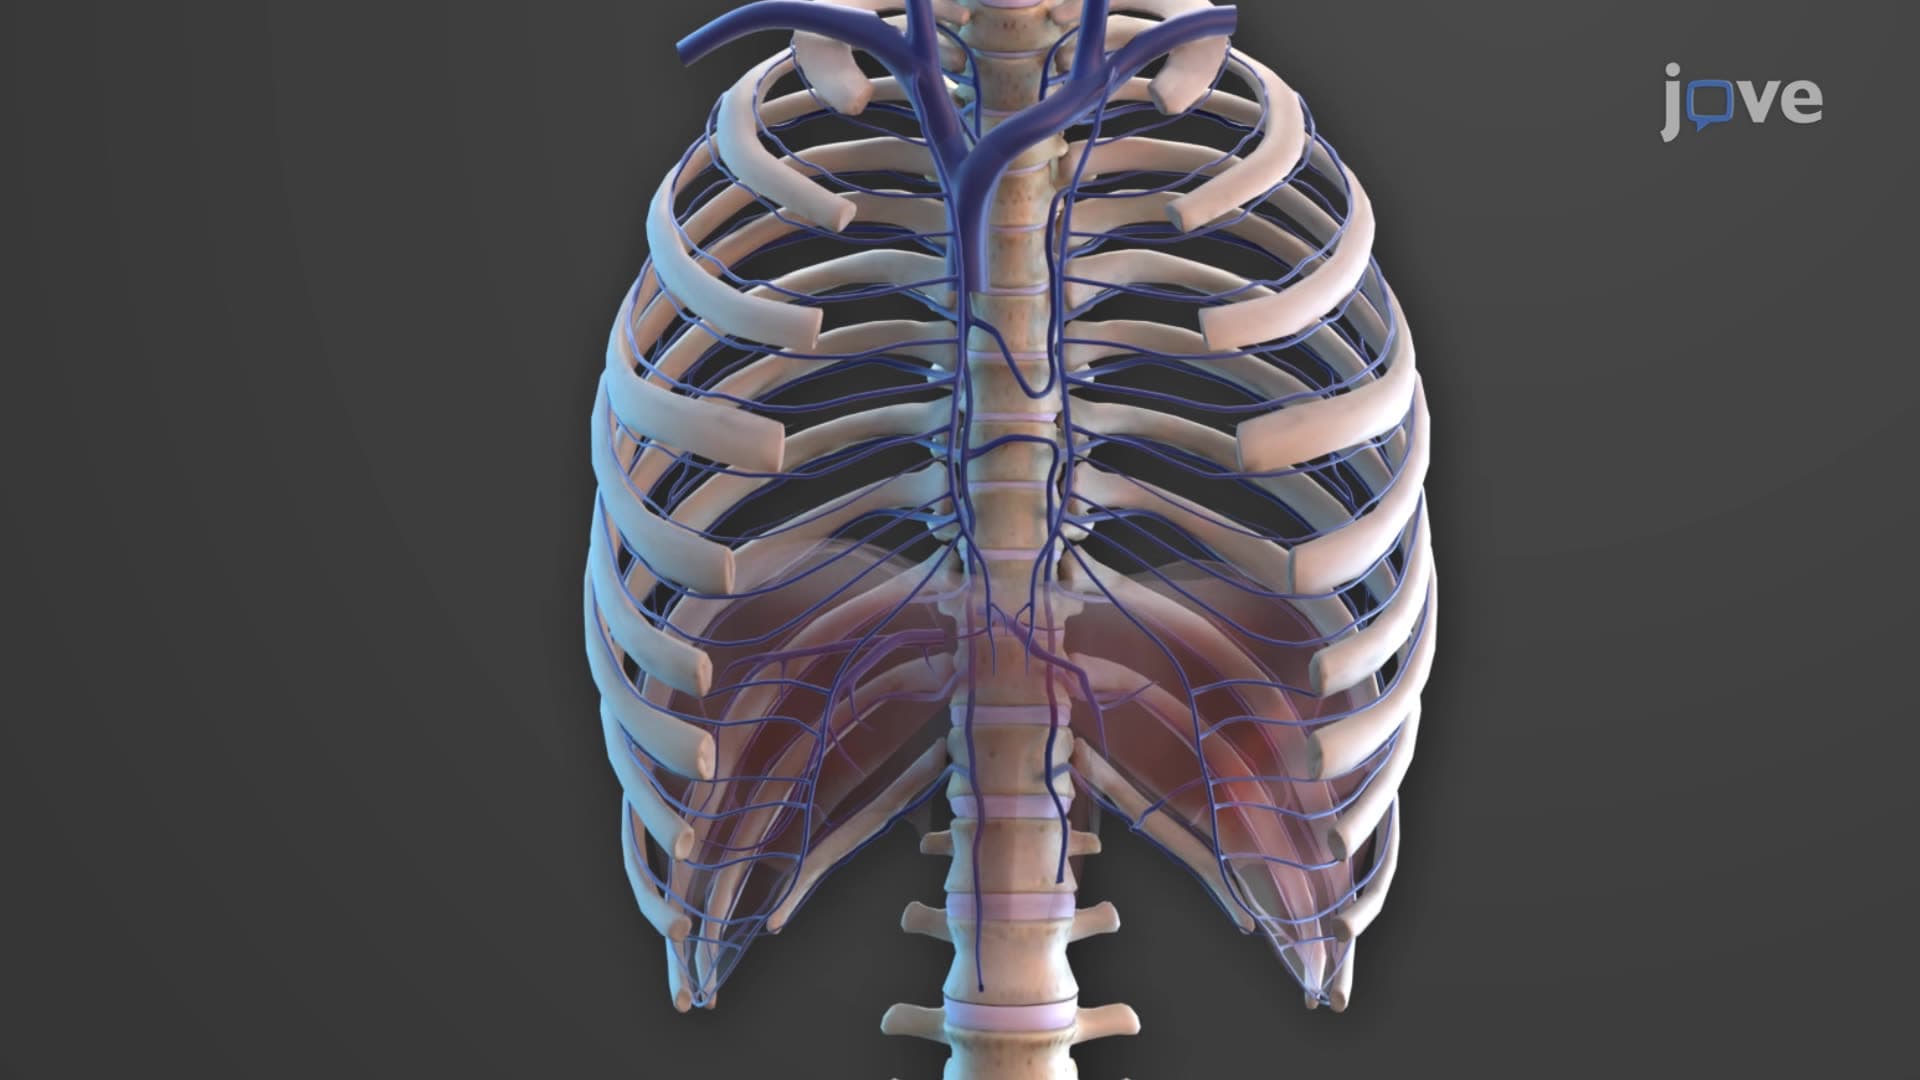
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...