Related Experiment Video
Updated: Sep 2, 2026
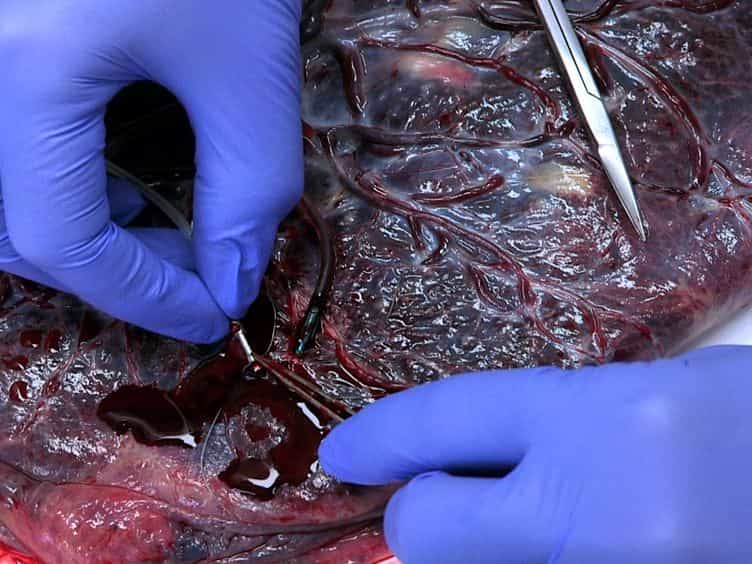

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013

The response of mother and fetus/neonate to drugs administered to the pregnant woman is determined largely by drug disposition and elimination within and between mother and fetus. Physiological changes occurring in pregnancy may result in reduced plasma protein binding, an increase in the apparent volume of distribution, and more rapid metabolic and renal clearance of certain drugs than are usually found in non-pregnant women. The consequences are relevant for the peak concentration of drug achieved after a single dose, the half-life of the drug, and the drug concentration to which the fetus is exposed via the placenta. Drugs whose dosage may need to be altered in pregnancy include most anticonvulsants, lithium, digoxin, certain beta-blockers, ampicillin and cefuroxime; for drugs which have not been specifically investigated, no generalizations are possible. Very few drugs given in pregnancy fail to cross the placenta and, as a rule, drug molecules not bound to plasma protein diffuse along a concentration gradient to establish and maintain an equilibrium. Because movement of drug molecules is bidirectional, the placenta is the main portal of exit from, as well as entry to, the fetus. The pharmacological response of the fetus to drugs which it receives depends mainly on the unbound concentration of drug in fetal blood--unwanted effects seldom occur if the maternal dose is correct; exceptions include tetracycline, antithyroid drugs, coumarin anticoagulants, aspirin, indomethacin and cerebral depressant drugs (opiates, barbiturates and phenothiazines). The total (bound plus unbound) drug concentration on the fetal side of the placenta is usually lower than on the maternal side except where differences in blood pH and/or protein binding lead to 'trapping' of drug in the fetus; the latter phenomenon may prove hazardous after birth because of the neonate's limited capacity to eliminate drugs by metabolism and excretion.
The response of mother and fetus/neonate to drugs administered to the pregnant woman is determined largely by drug disposition and elimination within and between mother and fetus. Physiological changes occurring in pregnancy may result in reduced plasma protein binding, an increase in the apparent volume of distribution, and more rapid metabolic and renal clearance of certain drugs than are usually found in non-pregnant women. The consequences are relevant for the peak concentration of drug achieved after a single dose, the half-life of the drug, and the drug concentration to which the fetus is exposed via the placenta. Drugs whose dosage may need to be altered in pregnancy include most anticonvulsants, lithium, digoxin, certain beta-blockers, ampicillin and cefuroxime; for drugs which have not been specifically investigated, no generalizations are possible. Very few drugs given in pregnancy fail to cross the placenta and, as a rule, drug molecules not bound to plasma protein diffuse along a concentration gradient to establish and maintain an equilibrium. Because movement of drug molecules is bidirectional, the placenta is the main portal of exit from, as well as entry to, the fetus. The pharmacological response of the fetus to drugs which it receives depends mainly on the unbound concentration of drug in fetal blood--unwanted effects seldom occur if the maternal dose is correct; exceptions include tetracycline, antithyroid drugs, coumarin anticoagulants, aspirin, indomethacin and cerebral depressant drugs (opiates, barbiturates and phenothiazines). The total (bound plus unbound) drug concentration on the fetal side of the placenta is usually lower than on the maternal side except where differences in blood pH and/or protein binding lead to 'trapping' of drug in the fetus; the latter phenomenon may prove hazardous after birth because of the neonate's limited capacity to eliminate drugs by metabolism and excretion.
More Related Videos
 09:04
Comprehensive Evaluation of the Effectiveness and Safety of Placenta-Targeted Drug Delivery Using Three Complementary Methods
Published on: September 10, 2018
 05:13
Preclinical Model of Prenatal Delta-9-Tetrahydrocannabinol Exposure to Assess Its Impact on Neurodevelopmental Outcomes
Published on: February 28, 2025
Related Concept Videos
 01:25
Drug Regulation
 01:21
Factors Affecting Drug Response: Overview
 01:07
Teratogenicity
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by anesthetizing...
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...
 01:18
Drug Elimination: Overview
Excretion refers to removing a drug from the body, either in its unchanged form or as its metabolites. Nonvolatile and polar drugs are primarily excreted through the kidneys, with other pathways including bile, sweat, saliva, and milk. Volatile drugs such as anesthetic gases are excreted via the...