Related Experiment Video
Updated: Feb 25, 2026
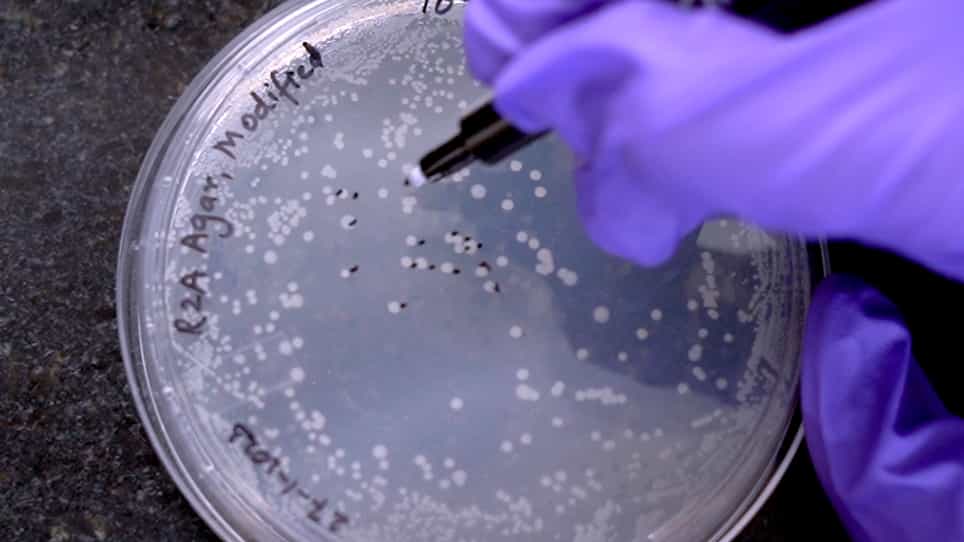
Isolation and Identification of Waterborne Antibiotic-Resistant Bacteria and Molecular Characterization of their Antibiotic Resistance Genes
Published on: March 3, 2023
The association between infection control interventions and carbapenem-resistant Enterobacteriaceae incidence in an
K Hussein1, G Rabino2, O Eluk2
1Infectious Diseases Institute, Rambam Health Care Campus, Haifa, Israel; Rappaport Faculty of Medicine, Technion-Israel Institute of Technology, Haifa, Israel.

Background:
Israel experienced a national outbreak of carbapenem-resistant Enterobacteriaceae (CRE) starting in 2006.
Aim:
To assess the association between infection control (IC) interventions implemented in a referral hospital in Israel and CRE incidence.
Methods:
Retrospective quasi-experimental study of prospectively collected data. CRE incidence, defined as the number of patients newly acquiring CRE in surveillance or clinical samples per 100,000 hospital-days, was plotted quarterly between 2005 and 2016. IC interventions were applied at different time-points throughout this period. Data were collected on IC staffing, number of rectal surveillance cultures, and carbapenem consumption. Autocorrelated segmented linear regression analysis was used to assess the time-points at which a significant change in the CRE incidence trend occurred, and the association between the timing of IC intervention implementation and observed CRE trends was assessed. Trends between time-points were expressed as quarterly percent change (QPC) with 95% confidence intervals (CIs).
Findings:
Between 2005 and 2008, CRE incidence increased significantly (QPC: 19.7%; CI: 11.5-28.4), reaching a peak of 186.6 new acquisitions per 100,000 hospital-days. From mid-2011 until the end of follow-up, there was a significantly decreasing incidence trend (QPC: -4.5; CI: -6.4 to -2.5). Cohorting of patients, screening of contacts and high-risk patients on admission were insufficient to control the epidemic. Improved hand hygiene compliance, cohorting with dedicated nursing staff, addition of regular screening in high-risk departments, and carbapenem restriction were required. Decreasing CRE incidence was observed with an infectious diseases/IC staffing of 1.2-1.5 per 100 beds and 20,000-36,000 yearly CRE surveillance samples.
Conclusion:
A multi-faceted hospital-wide intervention programme is required to control CRE in hospital settings.


Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:20
Infection
The chain begins with pathogens: bacteria, viruses, fungi, prions, or parasites such as protozoa helminths. These can be present on the skin as transient or resident flora, or they can be acquired from the environment. Identifying and treating the type of infection and...
 01:25
Endocarditis I: Introduction
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:17
Transmission-based Precautions I: Contact, Enteric, and Droplets
Contact Precautions:
Contact precautions are the measures taken to prevent the transmission of infectious agents, especially epidemiologically important microorganisms such as MRSA or influenza, primarily transmitted through direct or indirect contact with an...