Related Experiment Video
Updated: Feb 25, 2026
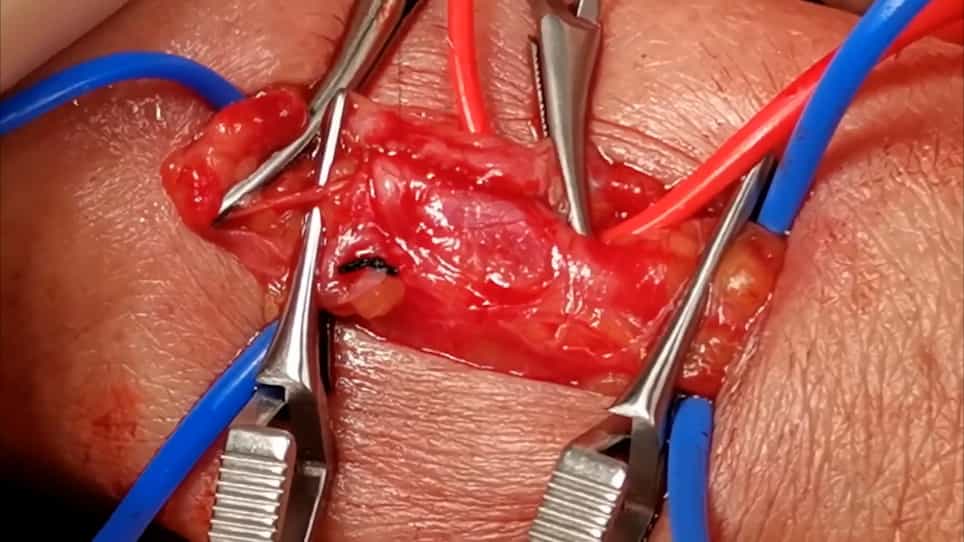
Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Outcomes of three types of native arteriovenous fistula in a single center
Emiliano Chisci1, Linda M Harris2, Francesco Menici3
1Department of Surgery, Vascular and Endovascular Surgery Unit, "San Giovanni di Dio" Hospital, Florence - Italy.

Insights
Distal arteriovenous fistulas (AVF) demonstrate superior one-year functional patency for hemodialysis access. If distal AVF is not feasible, middle-arm AVF is preferred over proximal AVF to ensure successful long-term hemodialysis.
Area of Science:
- Vascular Surgery
- Nephrology
- Dialysis Access
Background:
- Native arteriovenous fistulas (AVF) are crucial for hemodialysis access.
- Different AVF types (distal, middle-arm, proximal) have varying outcomes.
- Optimizing AVF selection impacts patient survival and quality of life.
Purpose of the Study:
- To compare the surgical outcomes of three native AVF types: distal (radial-cephalic), middle-arm (radial-cephalic), and proximal (brachial-cephalic).
- To evaluate patency rates, complication frequencies, and reintervention needs for each AVF type.
- To establish guidelines for AVF selection in hemodialysis patients.
Main Methods:
- Retrospective review of 317 hemodialysis patients from 2006-2014.
- Analysis of surgical outcomes for distal, middle-arm, and proximal AVF creation.
- Preoperative duplex vein mapping utilized for optimal vein and site selection.
Main Results:
- Distal AVF (D-AVF) showed higher one-year primary functional patency (80.5%) compared to middle-arm (MA-AVF, 75.8%) and proximal (P-AVF, 61.5%).
- P-AVF had a higher incidence of steal syndrome (3.8%).
- Reintervention for maturation was needed in 17% of D-AVF, 23% of MA-AVF, and 24% of P-AVF cases.
Conclusions:
- Distal AVF remains the gold standard for hemodialysis access due to superior patency.
- Middle-arm AVF is a viable alternative if distal AVF is not possible.
- Proximal AVF should be considered only after evaluating distal and middle-arm options.
Objective:
To study the outcomes of three different types of native arteriovenous fistula (AVF), the distal (D: radial-cephalic), middle-arm (MA: radial-cephalic) and proximal (P: brachial-cephalic) AVF access creation for hemodialysis patients in a single center.
Methods:
An 8-year retrospective review, from 2006 to 2014, was conducted at a single institution in which the surgical outcomes for three different types of native AVF creation were reviewed. Preoperative duplex vein mapping was obtained in all patients to choose the best vein and site for access.
Results:
There were 317 patients identified with 41 D-AVFs, 120 MA-AVFs and 156 P-AVFs. Younger patients with a lower Charlson's Index were more frequent in the D-AVF group (p = 0.02). Mean operating room time was 15 minutes longer for the MA-AVF group than the two others (p = 0.018). Early failure (thrombosis at 30-day), one-year patency, one-year primary AVF functional patency for the D-AVF, MA-AVF, and P-AVF groups were 2.4% (n = 1), 8% (n = 1), 3.8% (n = 6), (p = 0.14); 97.6% (n = 39), 99% (n = 117), 89% (n = 129), (p<0.001); 80.5% (n = 33), 75.8% (n = 91), and 61.5% (n = 96) (p<0.001), respectively. Reintervention for fistula maturation was required in 17% (n = 7), 23% (n = 28), and 24% (n = 38) (p<0.01). The one-year venipuncture hematoma and steal syndrome occurrences were 9.7% (n = 4), 6.7% (n = 8), 3.8% (n = 6) (p = 0.06); and 0%, 0% and 3.8% (n = 6) (p = 0.04), respectively. In case of failure of either MA-AVF or D-AVF, a P-AVF was always feasible as a second native AVF hemodialysis access.
Conclusions:
D-AVF is still the gold-standard access for hemodialysis. If D-AVF is not possible, MA-AVF should be always investigated before committing to a P-AVF.


Related Concept Videos
 01:25
Hemodialysis I: Introduction
 01:26
Aneurysm III: Interprofessional Care